

Performance of the HEART Score in pre-hospital settings for suspected non-ST-elevation acute coronary syndrome: The
Jaouad Azzahhafi1, Dean R P P Chan Pin Yin2, Mirjam Epping3
1Department of Cardiology, St. Antonius Hospital, Nieuwegein, The Netherlands. jaouad.azzahhafi@gmail.com.

Insights
The pre-hospital HEART score can help rule out major adverse cardiac events (MACE) in patients with chest pain. However, moderate agreement between pre-hospital and in-hospital scores suggests a need for improved training and diagnostic tools.
Area of Science:
- Cardiology
- Emergency Medicine
- Clinical Diagnostics
Background:
- The HEART score (History, ECG, Age, Risk Factors, Troponin) is utilized for risk stratification of chest pain patients.
- It categorizes individuals into low or high risk for major adverse cardiac events (MACE).
- Accurate risk assessment is crucial for timely and appropriate patient management.
Purpose of the Study:
- To evaluate the diagnostic performance of the pre-hospital HEART score.
- To assess the interobserver agreement between pre-hospital and in-hospital HEART scores.
- To determine the utility of the pre-hospital HEART score in ruling out myocardial infarction (MI) and MACE.
Main Methods:
- A prospective, multicentre study involving 383 patients with suspected non-ST-elevation acute coronary syndrome.
- Analysis of 331 patients with both pre-hospital and in-hospital HEART scores.
- Pre-hospital scores by ambulance personnel (point-of-care troponin); in-hospital scores by emergency physicians (ESC 0/1-hour high-sensitivity troponin algorithm).
Main Results:
- Among 331 patients, 26% were low-risk (pre-hospital HEART ≤ 3), with 4.7% experiencing index-admission NSTEMI.
- Patients with HEART score > 3 had a 12.1% MACE rate.
- Moderate interobserver agreement (ICC, 0.653) between pre- and in-hospital scores; lowest concordance in history and ECG. Pre-hospital HEART score showed 95.33% negative predictive value and 91.7% sensitivity for 30-day MACE.
Conclusions:
- Pre- and in-hospital HEART scores demonstrated moderate agreement.
- The 4.7% MACE rate in the pre-hospital low-risk group highlights the need for enhanced training in history and ECG assessment.
- Improved use of high-sensitivity troponin assays is recommended for better risk stratification.
Background:
The HEART (history, ECG, age, risk factors, and troponin) score is used to stratify patients with chest pain into low- or higher-risk for major adverse cardiac events (MACE). We assessed the diagnostic performance and interobserver agreement of the pre-hospital HEART score for ruling out myocardial infarction (MI) and MACE.
Methods:
This prospective, multicentre study included 383 patients with suspected non-ST-elevation acute coronary syndrome. Patients with both a pre-hospital and in-hospital HEART scores were analysed (n = 331). Prehospital HEART scores (based on point-of-care troponin) were assessed by ambulance personnel, and in-hospital HEART scores (based on the European Society of Cardiology 0/1-hour high-sensitivity troponin algorithm) were assessed by emergency physicians blinded to the pre-hospital scores. Endpoints were interobserver agreement (intraclass correlation coefficient, ICC) and diagnostic performance for ruling out MI and MACE at 30 days.
Results:
Among the 331 patients (mean age: 65 years, 48% women), 26% were classified as low risk (pre-hospital HEART ≤ 3) of whom 4.7% had an index-admission NSTEMI. Of the patients with HEART score > 3, 12.1% experienced MACE. Interobserver agreement between the pre- and in-hospital HEART scores was moderate (ICC, 0.653), with the lowest concordance for history and ECG. The pre-hospital HEART score yielded a negative predictive value of 95.33% and a sensitivity of 91.7% for MACE at 30 days.
Conclusion:
Pre- and in-hospital HEART scores showed moderate agreement. The 30-day MACE rate (4.7%) in the pre-hospital low-risk group indicates that improved training in history and ECG assessment, and use of high-sensitivity assays are required.
More Related Videos


Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:30
Acute Coronary Syndrome I: Introduction
 01:26
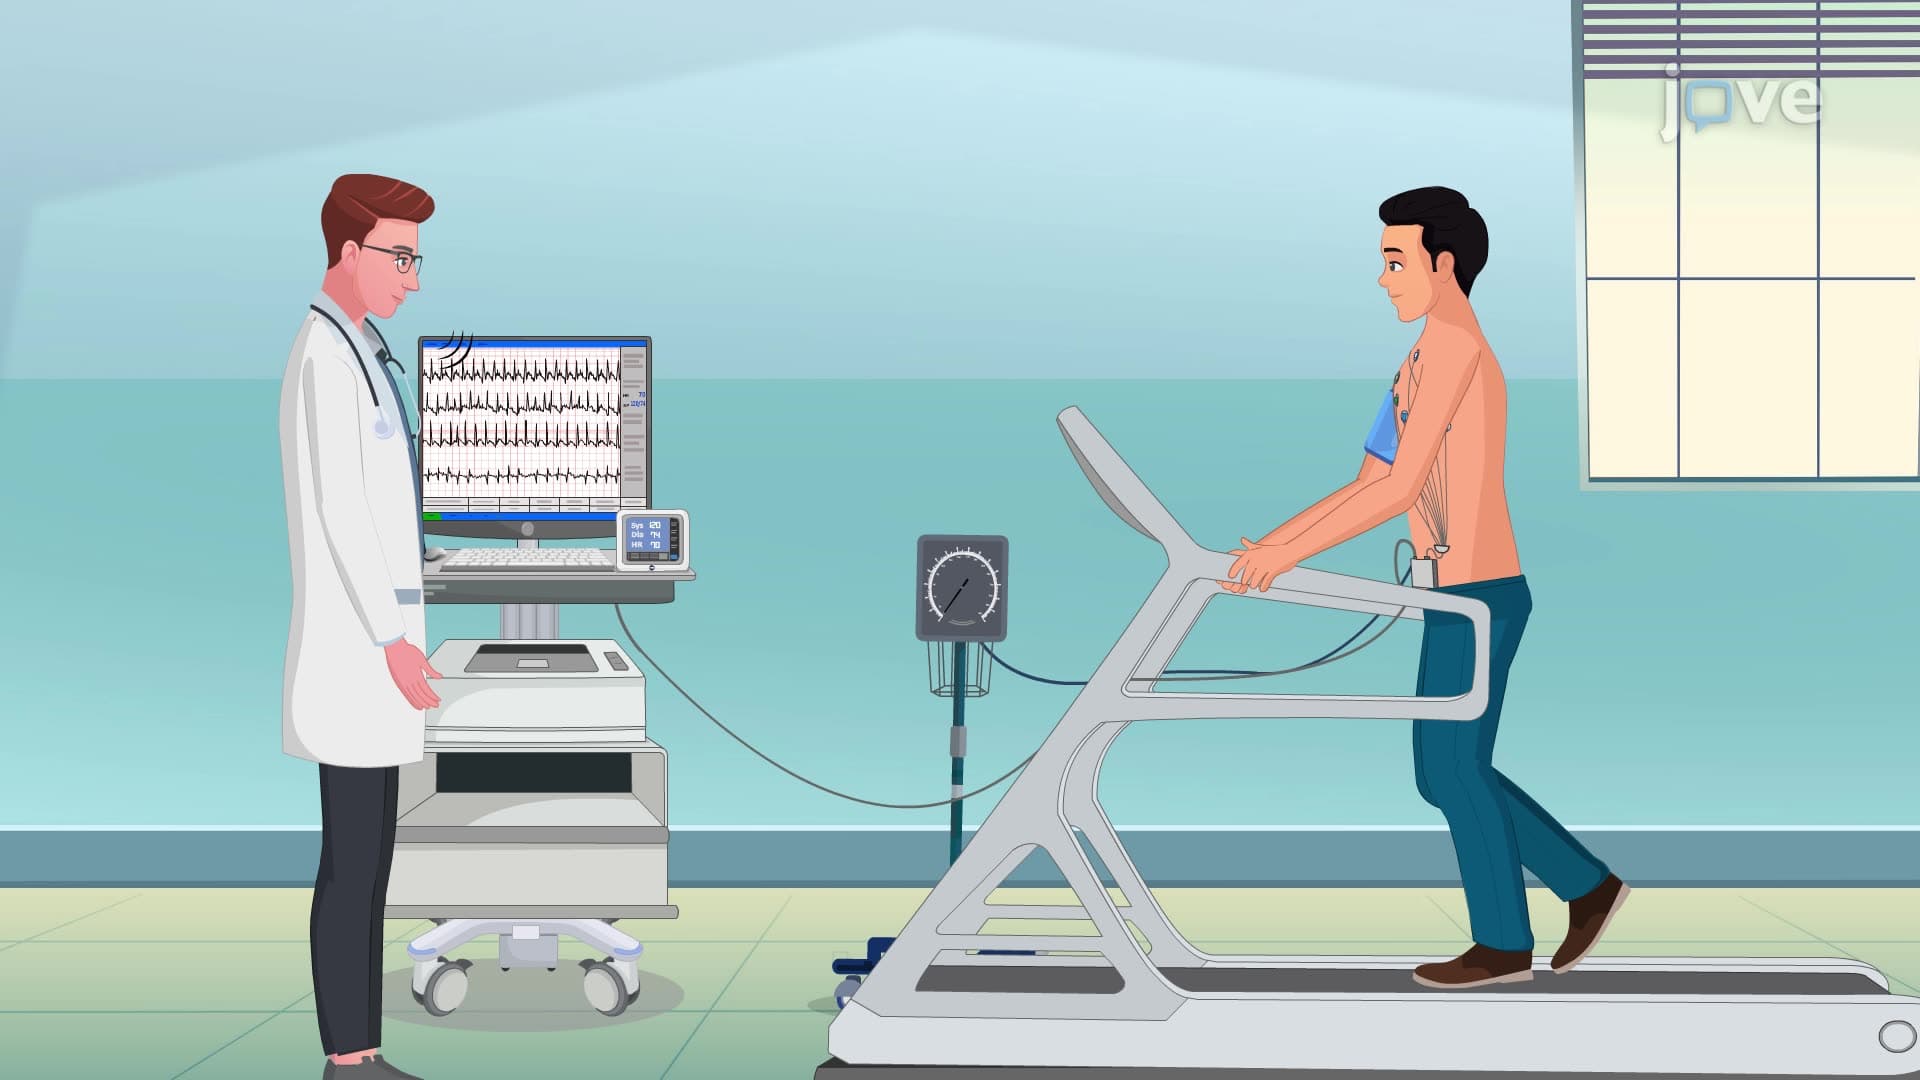
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:30
Introduction Cardiac Emergencies