Related Experiment Video
Updated: Apr 16, 2026
Laparoscopic Left Hemihepatectomy Combined with Caudate Lobe Resection
Published on: April 11, 2025
Laparoscopic right caudate lobectomy combined with right posterior lobectomy for hepatocellular carcinoma after
Lu Yang1, Xu Bao1, Dongyang Li1
1Department of Hepatobiliary Surgery, Liver Cancer Prevention and Treatment Research Center, Tianjin Medical University Cancer Institute & Hospital, National Clinical Research Center for Cancer, Tianjin's Clinical Research Center for Cancer, Tianjin Key Laboratory of Digestive Cancer, Key Laboratory of Cancer Prevention and Therapy, Tianjin, China.

Background:
Tumors located at the Caudate lobe are challenging due to proximity to major vessels, increasing recurrence risk and surgical difficulty. Neoadjuvant therapy has been explored for hepatocellular carcinoma (HCC) patients with higher risk of recurrence.
Methods:
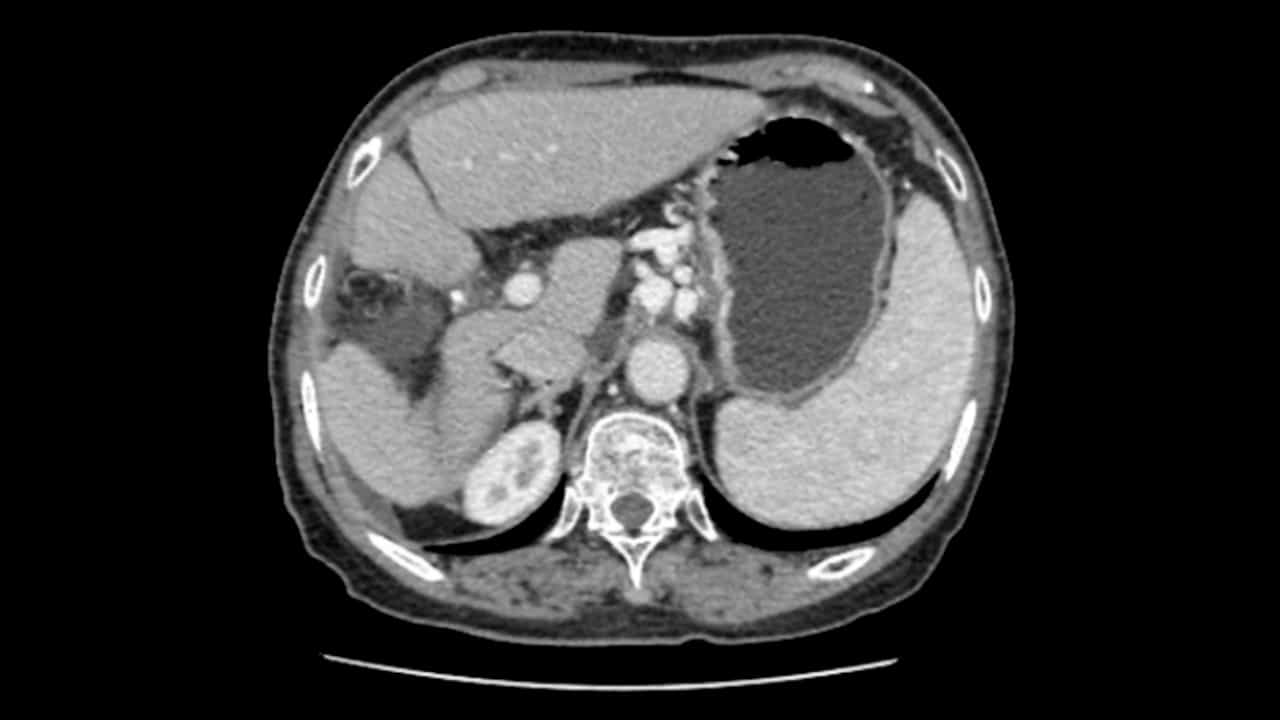
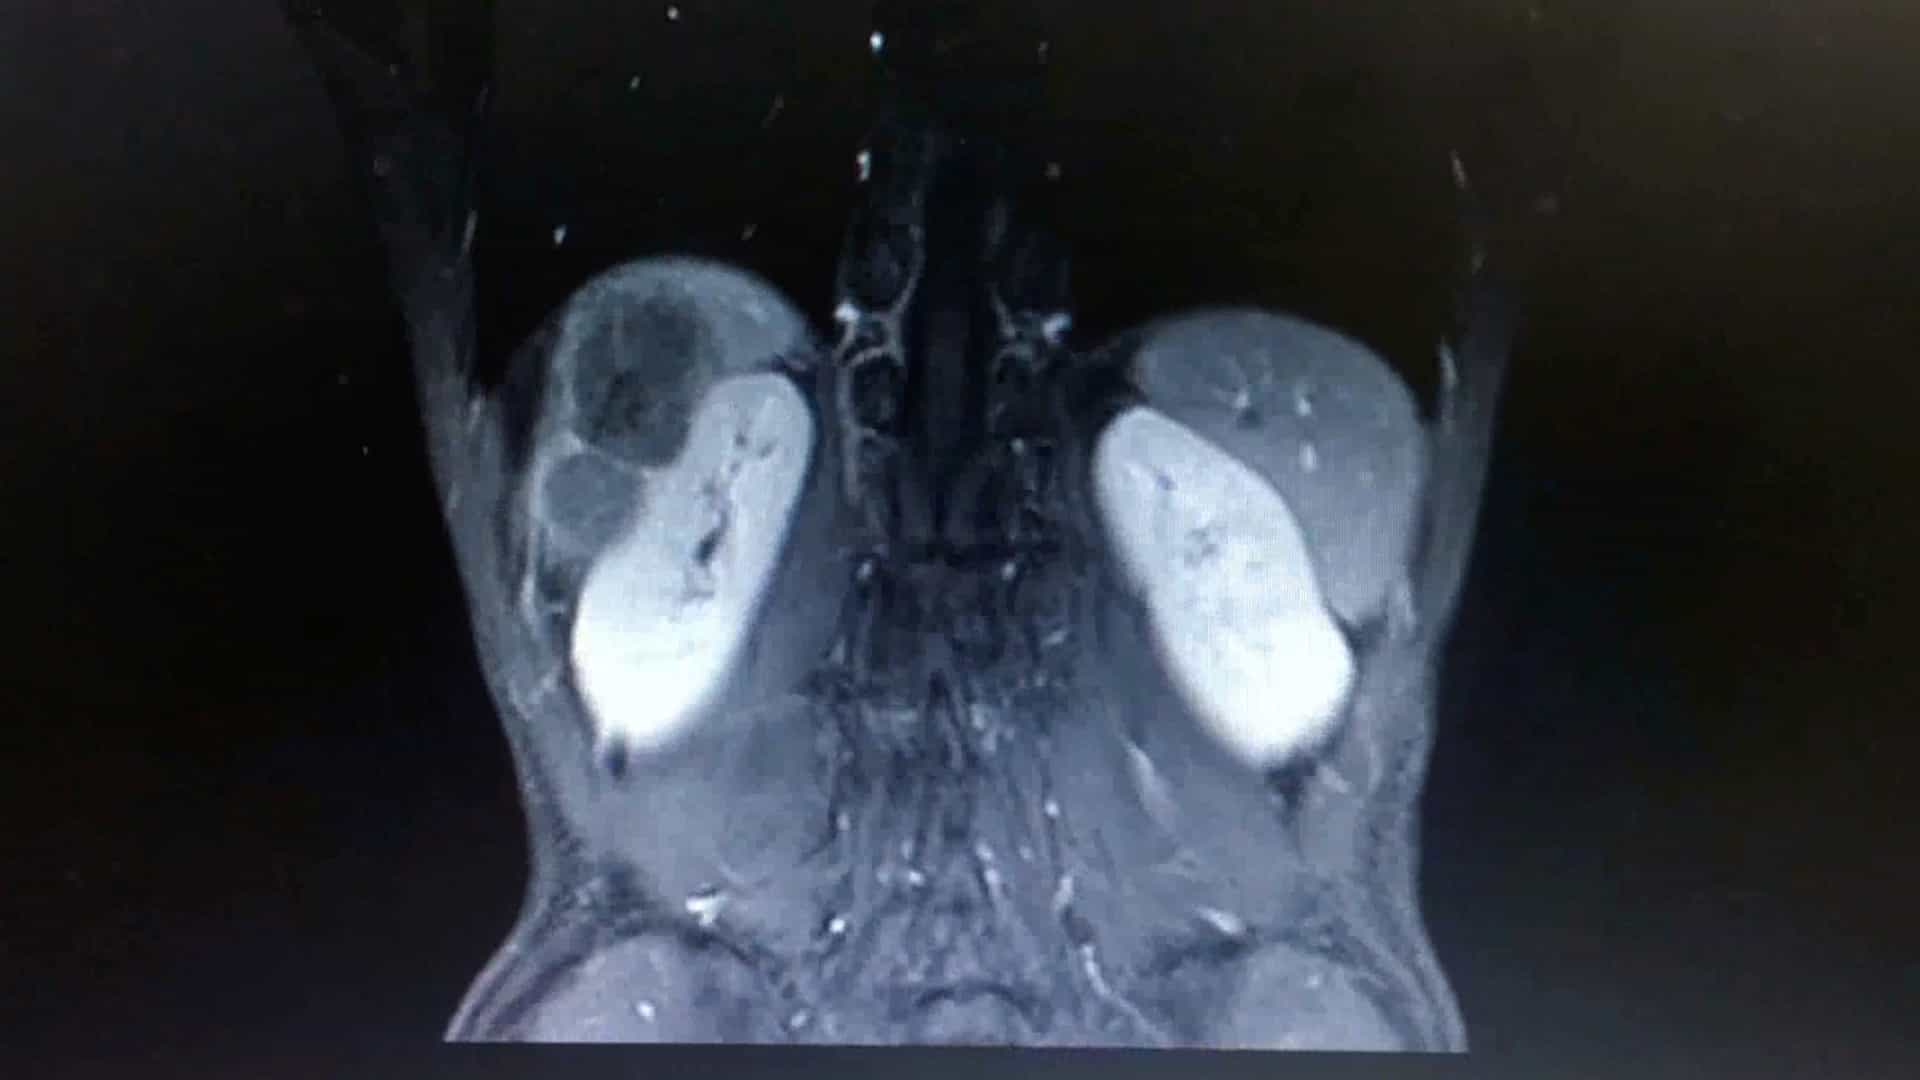
A 53-year-old female patient was admitted with hepatic mass detected during routine physical examination. PIVKA-II was 2143 mAU/ml and alpha-fetoprotein (AFP) was 8553 ng/ml. Contrast-enhanced magnetic resonance imaging demonstrated two discrete lesions, with tumor-related compression of the right hepatic vein and close anatomical proximity to the right portal vein trunk and posterior branch.
Results:
Due to multiple tumors and proximity to major blood vessels with narrow margins, multidisciplinary consultation determined that neoadjuvant therapy was decided. Patient received donafenib continuously, three sessions of sintilimab and hepatic arterial infusion chemotherapy (HAIC), which resulted in marked tumor regression. Laparoscopic resection was performed. Pathological examination confirmed a diagnosis of HCC with low-grade differentiation and a major pathological response (MPR) with necrotic tumor area exceeding 70%. No evidence of recurrence was detected at the six-month's follow-up.
Conclusion:
Our findings demonstrate that laparoscopic caudate lobectomy after neoadjuvant therapy is a feasible approach for managing resectable HCC with high risk of recurrence located in the caudate lobe.