Related Experiment Video
Updated: Oct 25, 2026
Robotic Enucleation of an Intra-Pancreatic Insulinoma in the Pancreatic Head
Published on: January 3, 2020
Robotic-assisted transduodenal ampullectomy for a neuroendocrine tumour: A step-by-step surgical video
Gianluca Rompianesi1, Giuseppe Kito Fusai1
1Hepato-Bilio-Pancreatic Surgery Unit, The Wellington Hospital, HCA Healthcare, London, UK.

Background:
When endoscopic resection of ampullary neuroendocrine tumors (NETs) is not feasible due to tumour size or location, transduodenal ampullectomy can offer a parenchymal-sparing alternative to a formal pancreaticoduodenectomy (Whipple procedure) [1,2]. We present a robotic-assisted transduodenal ampullectomy (RATA) in a 71-year-old male with an incidental 14 mm ampullary NET found during routine screening. Preoperative 68Ga-DOTATATE PET-CT demonstrated intense somatostatin-receptor avidity (SUVmax 66.8) and absent FDG uptake. The MDT recommended surgical excision due to size and Ki-67 4%.
Methods:
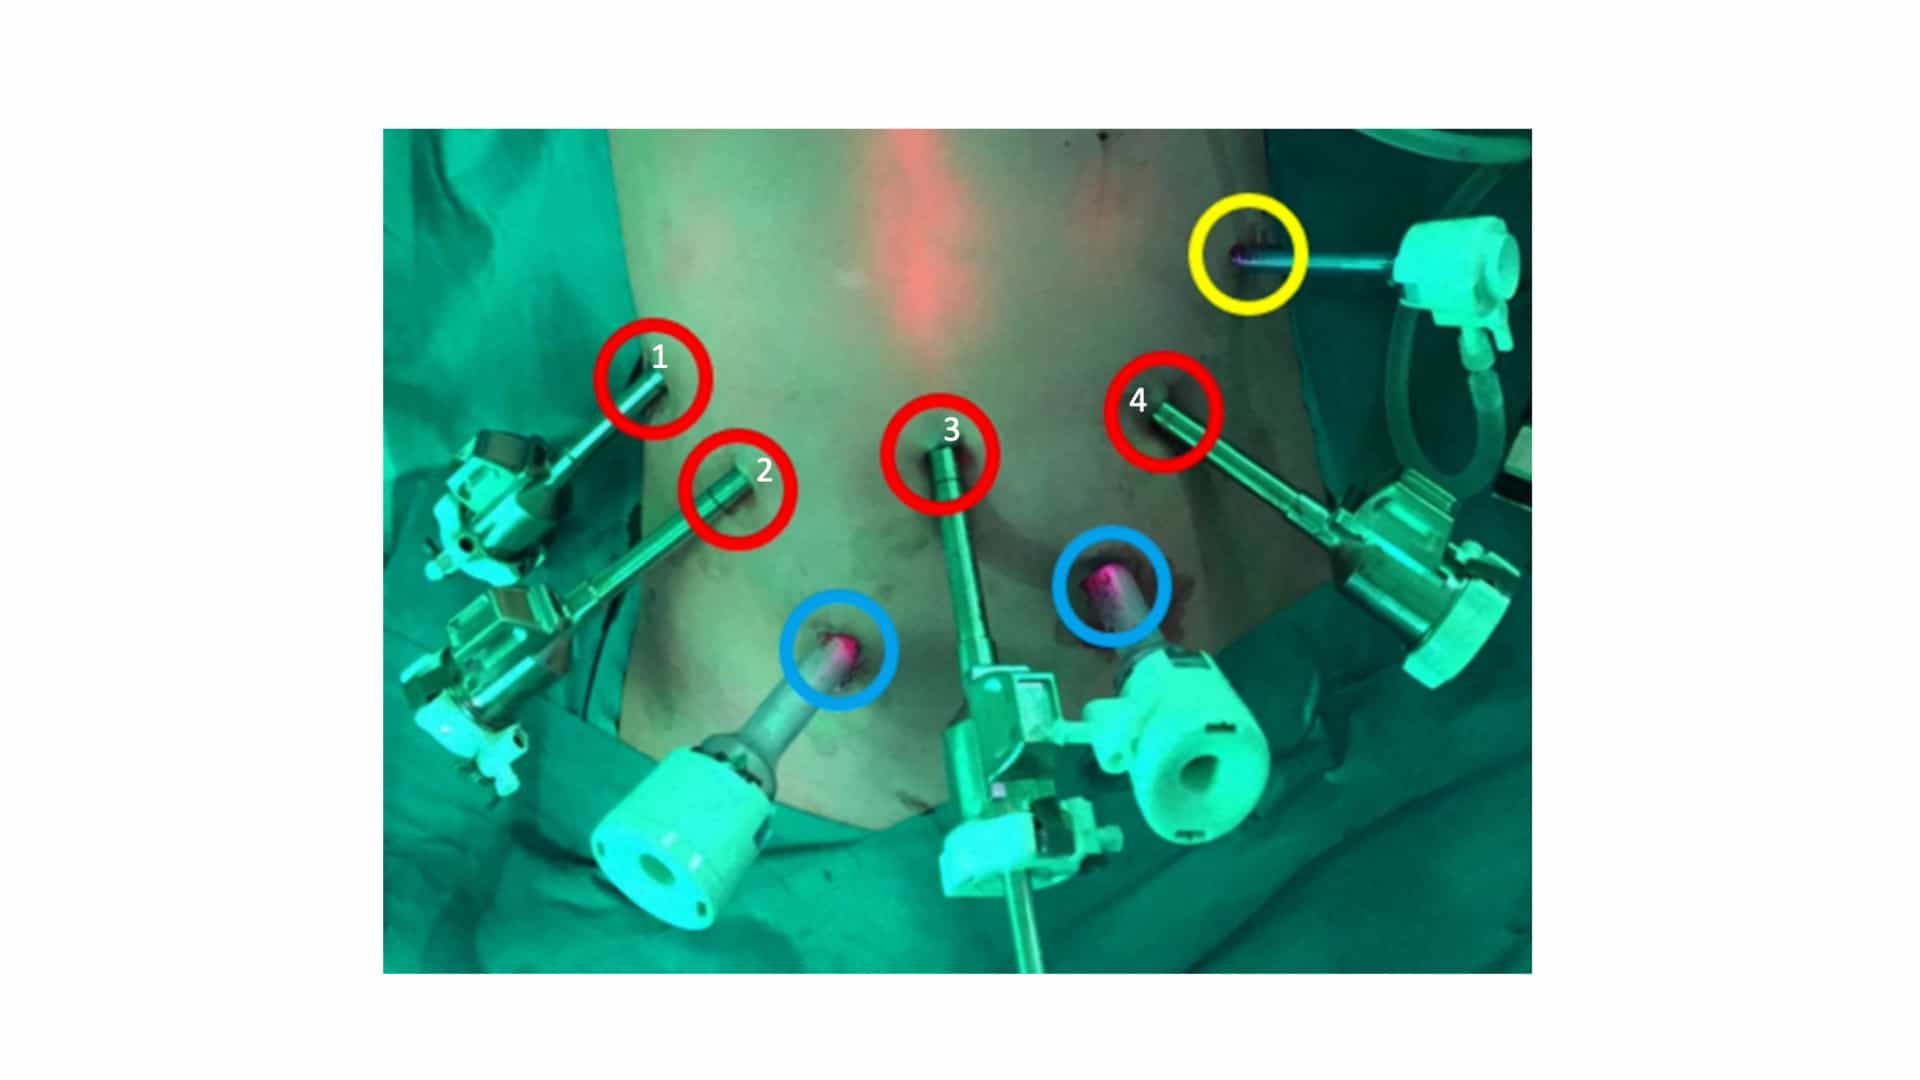
Following right colonic flexure mobilisation and a Kocher maneuver, the cystic duct was isolated and cannulated with a 4 Fr catheter to guide biliary identification. After a longitudinal duodenotomy, the ampullary lesion was visualized. Submucosal saline-adrenaline was injected in the submucosal plane. Diathermy scissors were used to perform a circumferential mucosal and muscularis dissection. Biliary and pancreatic ducts were sharply divided and reconstructed using interrupted 5/0 polydioxanone sutures between the pancreatobiliary ducts and the duodenal mucosa after positioning a 6 Fr catheter in the pancreatic duct. The duodenotomy was closed in two layers using a 4/0 absorbable barbed suture, and a methylene blue leak test through the nasogastric tube confirmed duodenal integrity.
Results:
The procedure was completed successfully with no intraoperative complications. A postoperative contrast-enhanced CT on day 5 demonstrated no collections and no oral contrast extravasation. Oral feeding was gradually reintroduced, the abdominal drain was removed, and the patient was discharged on day 7. Following a brief readmission on day 13 for a pulmonary microembolism successfully treated with medical therapy, the patient recovered fully and remains disease-free 7 months after surgery.
Conclusion:
RATA can represent a safe, feasible, and pancreas-preserving alternative to formal pancreaticoduodenectomy for well-differentiated ampullary NETs in selected patients. The robotic platform enhances three-dimensional visualization and wrist articulation, optimizing the delicate micro-reconstruction of the pancreaticobiliary junction.