Related Experiment Video
Updated: Apr 21, 2026
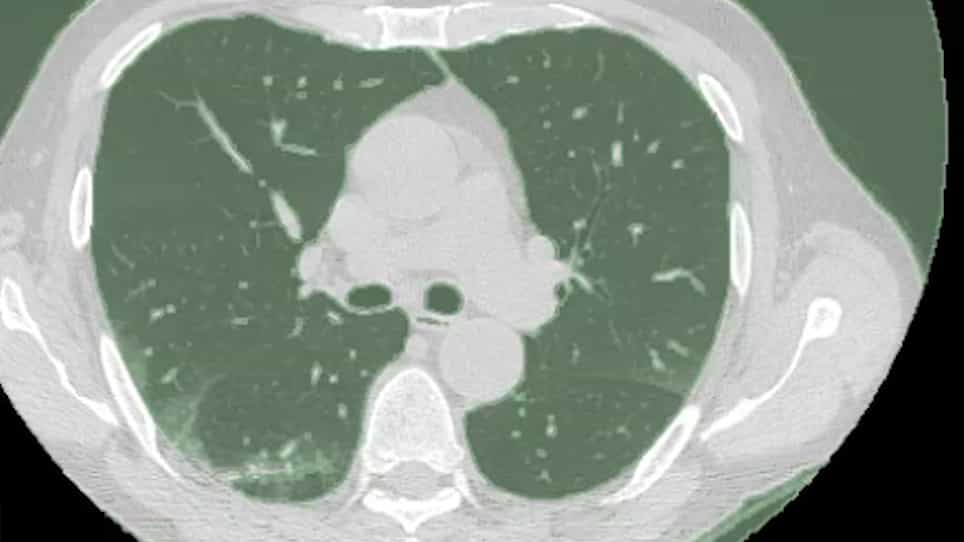

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Implications of Lung Compliance Phenotypes in COVID-19-Induced Acute Respiratory Distress Syndrome
Harish Gidda1, Tsz Hin Ng2, Susan Szpunar3
1Pulmonary and Critical Care Medicine, Henry Ford St. John Hospital, Detroit, USA.

Background:
Early literature suggested a phenomenon where coronavirus disease 19 (COVID-19)-induced acute respiratory distress syndrome (ARDS) presented with high respiratory system compliance (RC) in some patients. Thus, it posed a challenge to conventional ARDS ventilator management strategies.
Research Question:
Are there different phenotypes of lung compliance among mechanically ventilated patients with COVID-19-induced ARDS? Does the RC phenotype impact the clinical outcome? Study design and methods: This was a single-center historical cohort study that included patients who were mechanically ventilated for COVID-19-induced ARDS and who met the Berlin Criteria for ARDS. RC was calculated at intubation, for eight weeks, and at extubation. Data on demographic factors and comorbidities were also collected. Measurements: RC was calculated by tidal volume/pressure. Descriptive statistics, chi-squared test, Student's t-test, and multivariable logistic regression were used to analyze the data. Main results: Compliance groups were derived from the collected data. Most patients (73.6% to 89.4%) had severely reduced (≤40 ml/cmH₂O) static RC, and (10.7% to 26.4%) had RC ≥40 ml/cmH₂O. At week one and at extubation, there was a statistically significant difference in mortality between high versus moderate versus low RC groups: week one: (57.1% versus 66.7% versus 87.7%, respectively, p = 0.02); extubation: (83.3% versus 58.8% versus 87.2%, p = 0.01, respectively). Remdesivir administration, older age, and higher Charlson Comorbidity index scores were associated with increased mortality (4.2 OR 95% CI [1.61, 10.87]), (1.03 OR 95% CI [1.003, 1.07]), and (1.31 OR 95% CI [1.03, 1.67]), respectively. Declining PaO2/FiO2 (P/F) ratios were associated with lower RC.
Interpretation:
COVID-19 ARDS presents a range of RC and different phenotypes, which may require different ventilator strategies. Given the increased mortality at extubation in patients with low RC, it poses the possibility of a bedside prognostication tool. Older age, number of comorbidities, and Remdesivir use were associated with increased mortality. Lastly, declining P/F ratios were associated with lower RC.


Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:30
Acute Respiratory Failure-III
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:25
Chronic Obstructive Pulmonary Disease-III: Symptoms and Complications.
Symptoms of COPD can be classified as primary or systemic. Primary symptoms relate to reduced airflow, while systemic or extrapulmonary symptoms relate to COPD's broader impact on the body.
Primary Symptoms of COPD: