Related Experiment Video
Updated: Apr 28, 2026

Ultrasound-guided Botulinum Toxin-A Injections: A Method of Treating Sialorrhea
Published on: November 9, 2016
Botulinum Toxin Type A Injections in the Bladder Wall-An Effective Treatment for Urinary Incontinence with Low
Francisco Cruz1,2,3, Martin C Michel4,5, Yasuhiko Igawa6
1Department of Urology, Faculty of Medicine, University of Porto, 4200-319 Porto, Portugal.

Abstract:
Botulinum toxin type A (BoNT/A) injection into the bladder wall is a milestone in the treatment of urinary incontinence in patients with neurogenic detrusor overactivity (NDOi) or overactive bladder syndrome (OABi) who are refractory to or unable to tolerate oral or transdermal therapies. However, the efficacy of BoNT/A is hampered by the low long-term adherence of patients to a treatment that requires repeated bladder injections under cystoscopy control. The discontinuation is particularly evident among incontinent patients with spontaneous voluntary voiding, regardless of whether the cause is NDOi or OABi, although clearly more marked among the latter group. In addition to the bother and pain associated with repeated cystoscopies, these patients show low tolerance to the high incidence of urinary tract infections (UTIs) and transient urinary retention, the two most common adverse events. Fewer injection points may render treatments less painful, apparently without reducing efficacy, but will not avoid the need for repeated cystoscopies, and no studies have demonstrated that such modification increases adherence. Eventually, accessing the bladder wall for BoNT/A administration via a transabdominal approach, under real-time ultrasound guidance, may overcome trans-urethral limitations, but the technique's reproducibility remains unknown. An intensive investigation is ongoing to identify aids that facilitate the passage of the large, fragile BoNT/A molecule across the urothelium to reach the bladder nerves without injections. Electromotive Drug Administration (EMDA) of BoNT/A demonstrated efficacy and safety over a 6-year follow-up in NDOi patients at a single center, but the results were not reproduced at other institutions. The application of shock waves to the bladder using shock waves generated by Extracorporeal Shock Wave Lithotripsy (ESWL) machines to tear the urothelium and facilitate the passage of BoNT/A instilled in the bladder is ingenious, but the experience is very limited. Dimethyl sulfoxide, liposomes, and thermal-reversal hydrogel to deliver the toxin failed in pilot trials. BoNT/A in nano-formulations has high heat stability, resistance to pH changes, and to enzymatic degradation. Extended efficacy in dermal and intramuscular pilot applications is promising but needs to be replicated in the bladder.

Related Concept Videos
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:23
Urinary Bladder
In males, the bladder is situated in front of the rectum, while in females, it is positioned anterior to the vagina and uterus. The bladder floor contains an inverted triangular area called the trigone, defined by the two ureteric...
 01:19
Anatomy of the Genitourinary System II: Bladder and Urethra
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:17
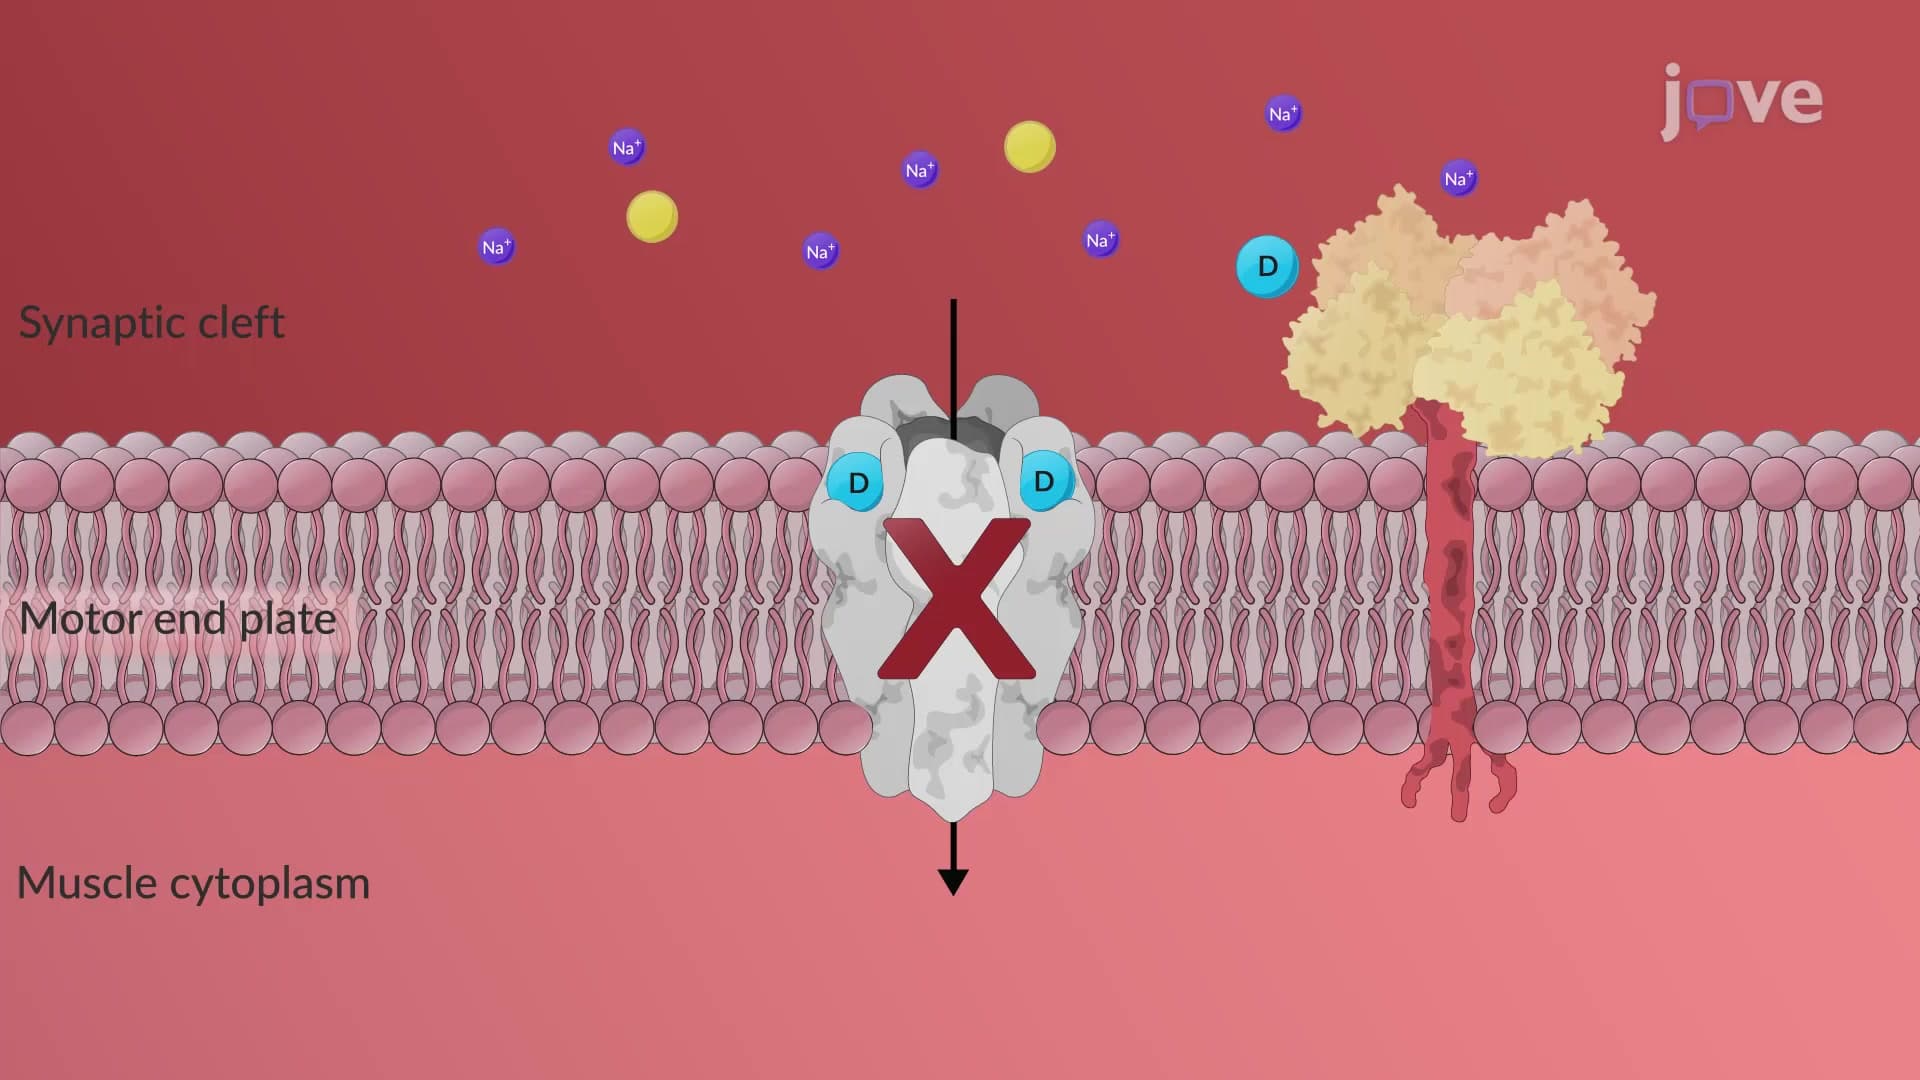
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...