Related Experiment Video
Updated: Jul 7, 2026
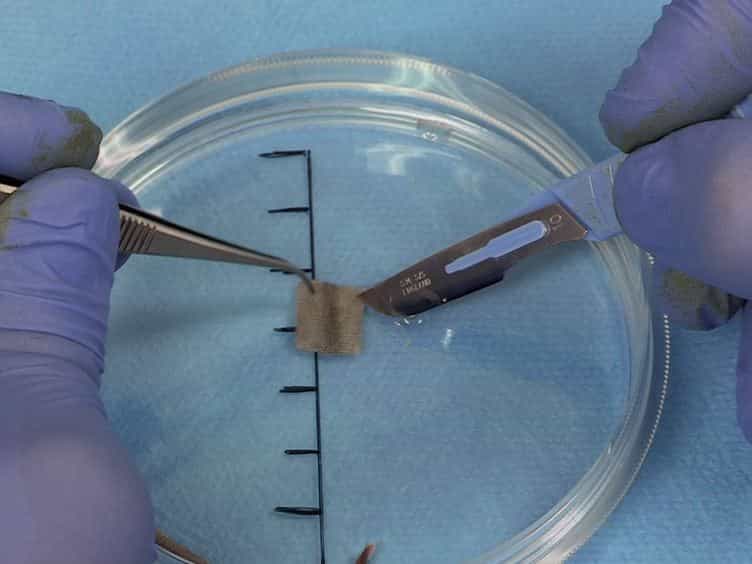
Transplantation of Tail Skin to Study Allogeneic CD4 T Cell Responses in Mice
Published on: July 25, 2014
Follow-up Liver Biopsy as a Tool for Tailoring Immunosuppressive Treatment in Pediatric Liver Transplantation
Jesús Quintero-Bernabeu1,2,3, Maria Teresa Salcedo-Allende1,4, Javier Juamperez-Goñi1,2,3
1Universitat Autònoma de Barcelona, Barcelona, Spain.

Background:
In pediatric liver transplantation (pLT), follow-up liver biopsies (fLBs) frequently reveal subclinical histological abnormalities, despite normal liver function tests. Findings, including inflammation, fibrosis, and immune-mediated changes, suggest overlapping alloimmune and autoimmune mechanisms with potential long-term consequences.
Methods:
We performed a prospective, single-center cohort study at the Vall d'Hebron Barcelona Hospital Campus, including 167 children who underwent 299 liver biopsies (214 protocol, 85 post-immunosuppression modification) from 2018 to 2024. Immunosuppression was adjusted according to a preestablished histology-guided protocol, intensifying therapy in patients with subclinical T cell-mediated rejection (S-TCMR; Banff Rejection Activity Index ≥2) detected in protocol biopsies.
Results:
S-TCMR was identified in 71 of 214 (33.2%) protocol biopsies, with fibrosis (Ishak ≥2) in 38 (53.5%). Following protocol-driven immunosuppressive intensification, 57 of 71 (80.3%) achieved S-TCMR resolution at 12 mo, with 8 of 12 showing further improvement at 24 mo. Fibrosis regressed by ≥1 Ishak stage in 21 of 38 (55.3%). Autoantibody responders showed superior S-TCMR ( P = 0.006) and fibrosis outcomes ( P = 0.05). Donor-specific antibody-positive patients exhibited lower S-TCMR resolution (odds ratio [OR], 3.3; P = 0.1) and a higher risk of persistent fibrosis (OR, 4.8; P = 0.03). Plasma cell-rich S-TCMR (18/71 [25.4%]) strongly correlated with C4d deposition (5-fold increase) and markedly reduced fibrosis regression (OR, 11.0; P < 0.001), indicating resistance to standard immunosuppression.
Conclusions:
Histology-guided, protocol-driven immunosuppression intensification effectively reversed most S-TCMR and fibrosis, underscoring the importance of long-term protocol biopsies for individualized therapy in pLT.


