Related Experiment Video
Updated: Apr 30, 2026


Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Physiological Persistence of Tension Pneumothorax After Minor Diaphragmatic Injury During Laparoscopic Adrenalectomy:
Eun Ji Park1,2, Jeong-Min Hong1,2, Hyeon-Jeong Lee1,2
1Department of Anesthesia and Pain Medicine, Medical Research Institute, Pusan National University Hospital, Busan, South Korea, mri.gov.lk.

Background:
During laparoscopic surgery, tension pneumothorax may persist despite prompt anatomical repair of a diaphragmatic injury, posing a diagnostic and management challenge for anesthesiologists under general anesthesia.
Case:
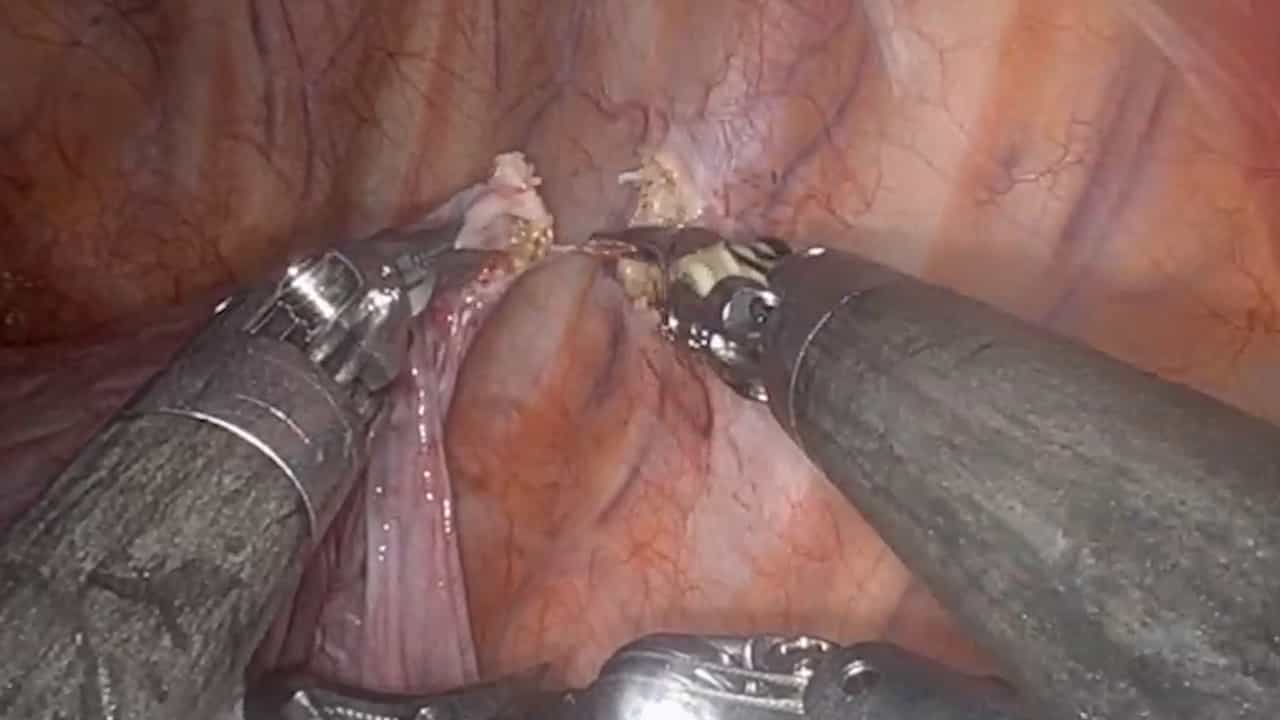
A 68-year-old male undergoing bilateral laparoscopic adrenalectomy using a retroperitoneal approach developed progressive hypoxemia, hypercapnia, elevated peak inspiratory pressure, and hemodynamic instability approximately 4 h after surgical initiation. A minor diaphragmatic injury was identified and immediately repaired after reduction of pneumoretroperitoneum. Despite anatomical correction, respiratory and circulatory instability persisted, requiring high-dose vasopressor support and 100% inspired oxygen until the end of surgery. A radiograph obtained at the conclusion of surgery demonstrated marked mediastinal shift consistent with tension pneumothorax. The pneumothorax resolved spontaneously with supportive ventilation, and the patient recovered without chest tube insertion.
Conclusion:
This case highlights a physiological pitfall rather than a rare complication: even a minor diaphragmatic injury can result in sustained tension physiology despite timely anatomical repair during prolonged laparoscopic surgery. Continuous vigilance for evolving physiological abnormalities and proactive anesthesiologist-led management are essential.

Related Concept Videos
 01:08
Pneumothorax II: Pathophysiology
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:26
Endoscopic Studies II: Thoracocentesis
Description
Excess pleural fluid or air may accumulate in some respiratory disorders in the thoracic cavity. To treat pleural effusion, a physician conducts thoracentesis by carefully piercing the chest wall and entering...
 01:10
Atelectasis II: Pathophysiology
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History: