Related Experiment Video
Updated: May 2, 2026
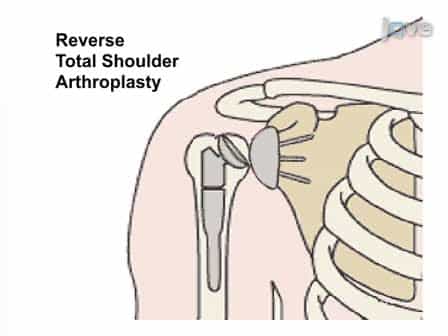

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Teres minor circle and subscapularis lengthening patterns during forward elevation in lateralized reverse total
Erica Lante1,2, William G Blakeney3,4, Stefan Bauer1,4
1Centre de l'épaule, du coude et du membre supérieur, EHC, Morges, Switzerland School of Surgery, University of Western Australia, Perth, Australia.

Background:
Lateralized reverse total shoulder arthroplasty (rTSA) designs aim to restore tension and function of the deltoid and remaining rotator cuff. Although the role of the subscapularis (SSC) is established in the native shoulder and after anatomic total shoulder arthroplasty, its repair after rTSA remains controversial. The teres minor (TM) is considered a principal contributor to external rotation in rTSA, particularly when the infraspinatus (ISP) is insufficient, yet its length-tension behavior across forward elevation has not been characterized.
Methods:
Fifteen preoperative computed tomography scans from patients undergoing rTSA were used to generate three-dimensional shoulder models. rTSA was simulated using 4 lateralized implant configurations differing in glenoid baseplate position and neck-shaft angle (NSA): (1) a Frankle-type configuration with a centrally positioned ("high") glenoid baseplate and a 135° NSA; (2) an inferiorly positioned (flush with the lower border of the glenoid) baseplate with a 135° NSA; (3) an inferiorly positioned baseplate with a 145° NSA; and (4) an inferiorly positioned baseplate with a 155° NSA. Forward elevation from 0° to 120° at 20° abduction and 0° rotation was analyzed. Muscle-tendon length changes were computed for TM, SSC, ISP, and deltoid. Outcomes included biphasic prevalence, circle angle (the forward-elevation angle at which muscle length transitions from shortening to lengthening), and curvature.
Results:
SSC consistently lengthened with forward elevation across all 4 lateralized rTSA designs. All TM curves (60/60, 100%) were biphasic, with early shortening followed by lengthening. The median TM circle angle occurred at 50° [44-56] and curvature was -0.015 (95% confidence interval -0.016 to -0.015). In comparison, ISP was biphasic in 80% (48/60), SSC in 45% (27/60), and deltoid in 38% (23/60). Median circle angles were 77° [71-83] for ISP, 38° [25-52] for SSC, and 33° [23-45] for deltoid. TM exhibited a significantly earlier circle angle than ISP (-26.9°, 95% confidence interval -32.2 to -21.7) and greater curvature than all other muscles. These patterns were preserved across 135°, 145°, and 155° designs.
Conclusion:
This study confirms SSC lengthening during forward elevation across lateralized rTSA designs and describes a novel biphasic length-tension pattern of the TM circle. These findings provide a biomechanical rationale for SSC repair vulnerability and highlight the functional contribution of the TM to external rotation in elevated positions after rTSA.
More Related Videos
 05:25
Knotless Independent Double-Row Repair and Biceps Augmentation for Anterosuperior Rotator Cuff Tears
Published on: January 23, 2026
 07:10
Modified Long Head of Biceps Tendon Rerouting and Fixation as Partial Capsular Reconstruction for Massive Irreparable Rotator Cuff Tears
Published on: March 6, 2026
Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...