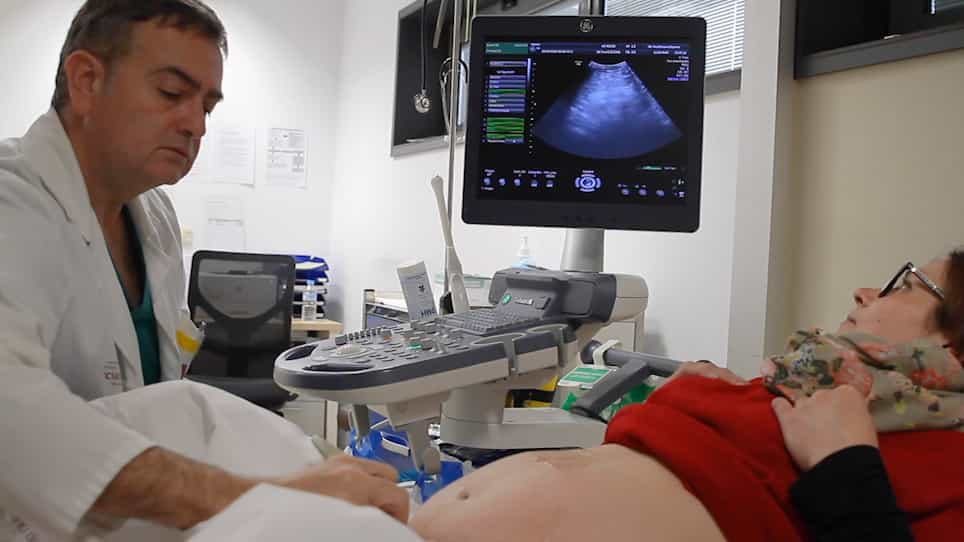
Management of cesarean scar pregnancy: Manual vacuum aspiration VS local and systemic methotrexate - A retrospective study
Related Experiment Video
Updated: May 3, 2026
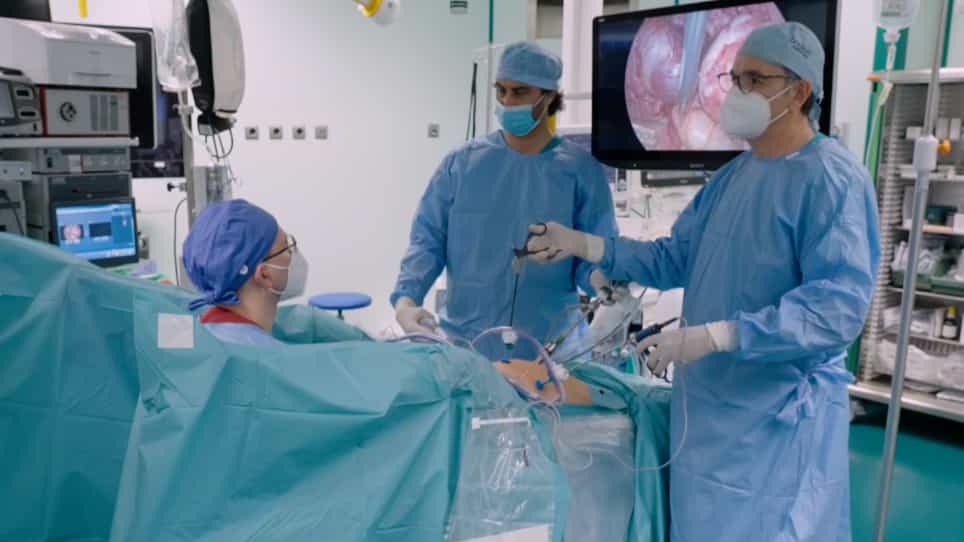
Fertility Sparing Procedure using Carbon Dioxide Fiber Laser Vaporization of Ovarian Endometrioma
Published on: July 6, 2022
Ismet Hortu1, Arif Onur Atay2, Ferruh Acet3
1Department of Obstetrics and Gynecology, Ege University, Izmir, Turkey.

Objective:
To compare treatment strategies for cesarean scar pregnancy (CSP) manual vacuum aspiration (MVA), intracavitary methotrexate (Methotrexate), and intramuscular MTX and identify factors for treatment failure and prolonged course.
Methods:
This retrospective cohort included CSP cases managed at a tertiary center. Initial management was categorized as MVA, intracavitary or intramuscular MTX. Primary failure was the need for rescue treatment. Secondary outcomes were hospital stay and time to β-hCG negativization. Additional analyses examined associations between baseline clinical/ultrasound variables and outcomes.
Results:
Most patients were asymptomatic at presentation. The need for additional treatment differed across initial strategies (p = 0.008), with the lowest failure after MVA. Hospital stay differed significantly (p < 0.001) and was shorter after MVA than MTX-based strategies. Time to β-hCG negativization also differed (p = 0.002) and was shorter after MVA. Intracavitary and intramuscular MTX showed no significant differences in hospital stay or β-hCG negativization (both p > 0.05). After excluding cases requiring rescue therapy, hospital stay remained different (p < 0.001), whereas time to β-hCG negativization no longer differed (p = 0.118). Treatment strategy remained associated with failure after adjustment (p < 0.05). MTX-based management was associated with longer hospitalization and delayed β-hCG negativization (both p < 0.001); residual myometrial thickness ≤3 mm was associated with longer hospitalization (p = 0.026), and gestational sac diameter ≥20 mm with delayed β-hCG negativization (p < 0.001).
Conclusion:
In this cohort, MVA was associated with less frequent escalation and a shorter course than MTX-based strategies, while intracavitary and intramuscular MTX showed similar outcomes. Ultrasound markers of scar integrity and implantation burden were linked to prolonged course and may guide management.