Related Experiment Video
Updated: Oct 26, 2026
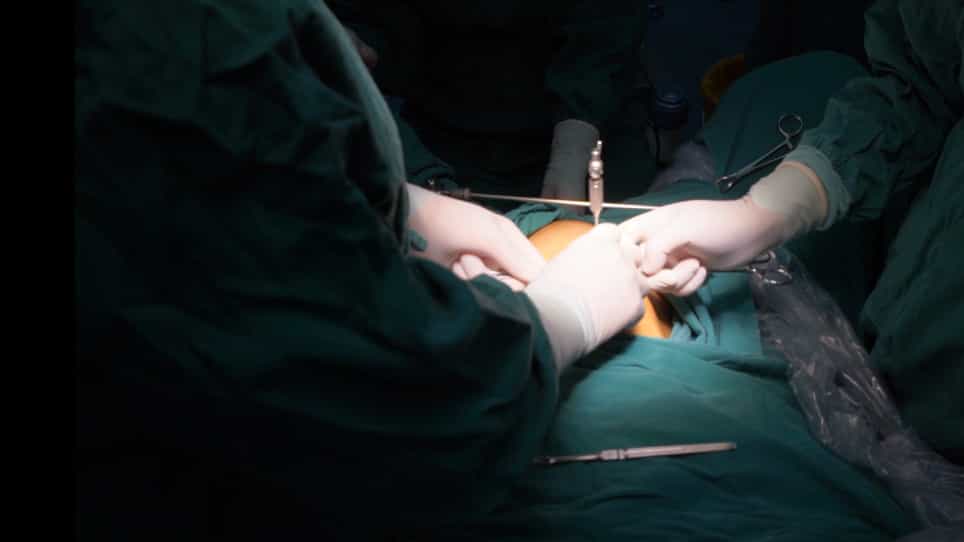
Introduction of Intracapsular Rotary-cut Procedures (IRCP): A Modified Hysteromyomectomy Procedures Facilitating Fertility Preservation
Published on: January 17, 2019
Robot-assisted laparoscopic fertility-sparing resection of accessory cavitated uterine malformation
Adrien Msika1, Pascal Rousset2, Lola Robelin1
1Service de Chirurgie Gynécologique et Oncologique, Obstétrique - Hopital Lyon Sud, Hospices Civils de Lyon.

Objective:
To describe a fertility sparing robot-assisted laparoscopic resection of accessory cavitated uterine malformation (ACUM) SETTING: A referral center specialising in minimally invasive gynaecological surgery.
Participant:
A 28 years old G0P0 woman, with a history of a laparoscopic exploration for abdominal pain and appendicectomy was performed. Pathological analysis did not formally diagnose appendicitis. Pelvic symptoms began at the age of 13 with dysmenorrhea, pelvic pain, and later deep dyspareunia. Pelvic MRI was performed in the late adult age and revealed a mass on the side of the uterus, measuring 30 × 30 × 24 mm, classified as FIGO VI from Munro et al.'s leiomyoma subclassification system (1), with a central haemorrhagic component and a peripheral muscular component consistent with the diagnosis of an ACUM.
Interventions:
A robot-assisted laparoscopic procedure was performed. ACUM was suspected during the procedure. A vertical myometrial incision was created. Careful dissection was then carried out using monopolar energy. The vascular structures were identified and preserved during the dissection. The accessory uterine malformation was removed without uterine cavity perforation. The myometrial layer was then closed using three interrupted 0 polyglactin 910 sutures (Vicryl 0) sutures.
Conclusion:
ACUM is a rare condition. A diagnostic odyssey is common for young patients with chronic pelvic pain. Vaginal ultrasound and/or pelvic MRI remain the most important complementary imaging tests for making a diagnosis. However, the final diagnosis is histopathological. A FIGO-based classification (1) may be useful for categorizing the location of accessory cavitated uterine malformations and guiding surgical management. In a retrospective cohort study, approximately 70% of lesions were classified as FIGO-type 7 or 8 (2) Thus, for most patients, fertility-sparing surgery with no uterine cavity effraction is possible and offers complete resolution of pelvic pain. Robotic assistance enables precise dissection with stability and magnification; particularly useful for these lesions, which sometimes do not display a clear dissection plan.