Related Experiment Video For Fusion biopsy
Updated: May 8, 2026

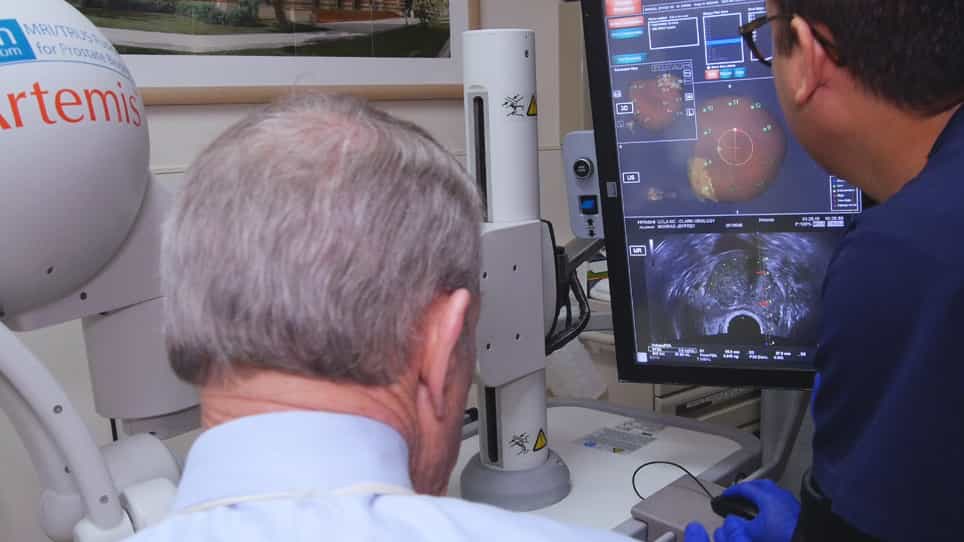
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Urologist and radiologist contributions to variation in prostate cancer detection at fusion biopsy
Daniel Triner1, Kevin B Ginsburg2, Ana Moser2
1Department of Urology, Stanford University, Stanford, CA, USA.

Objectives:
To quantify the relative contribution of radiologists and urologists to variability in clinically significant prostate cancer (CSPC) detection across multiparametric magnetic resonance imaging (mpMRI)-guided prostate fusion biopsies and to determine whether this differed across Prostate Imaging-Reporting And Data System (PI-RADS) categories.
Subjects, Patients And Methods:
We analysed biopsy-naïve men within the Michigan Urological Surgery Improvement Collaborative (MUSIC) who underwent fusion biopsy between August 2017 and November 2021. The primary outcome was the proportion of variance in CSPC detection (Gleason score ≥3 + 4) at targeted regions of interest that was explained by individual urologists and radiologists. We used generalised linear mixed-effects models to partition variance and estimate intraclass correlation coefficients (ICCs) for radiologist- and urologist-level effects for PI-RADS score 3-5 lesions. We calculated the median odds ratio (MOR) to quantify the expected difference in odds of CSPC detection when comparing a randomly selected higher- vs lower-detecting provider from the same distribution.
Results:
Among 1544 men with 2045 targeted lesions, mpMRIs were interpreted by 115 radiologists and biopsies performed by 86 urologists. For PI-RADS score 3 lesions, urologists (ICC = 0.15, MOR = 2.07) accounted for greater variance in CSPC detection than radiologists (ICC = 0.07, MOR = 1.61). For PI-RADS score 4, both urologist (ICC = 0.05, MOR = 1.49) and radiologist (ICC = 0.07, MOR = 1.61) contributed modestly. For PI-RADS score 5, radiologists (ICC = 0.17, MOR = 2.19) explained a larger proportion of variance than urologists (ICC = 0.01, MOR = 1.19), suggesting individual radiologists meaningfully impact CSPC detection of high-risk lesions.
Conclusions:
For PI-RADS score 3 lesions, the specific urologist performing the biopsy was a strong source of variation, while for PI-RADS score 5 lesions, the radiologist had greater influence on CSPC detection rates. Optimising MRI acquisition and interpretation, ensuring accurate fusion registration, and improving biopsy accuracy are critical to improving diagnostic consistency.
Related Concept Videos
 01:22
Imaging Studies V: Intravenous Urography and Retrograde Pyelography
 01:27
Imaging Studies IV: Magnetic Resonance Imaging
 01:28
Imaging Studies I: Kidney, Ureter, and Bladder Studies
 01:27
Imaging Studies III: Computed Tomography