Related Experiment Video
Updated: May 12, 2026

Deep Neuromuscular Blockade Leads to a Larger Intraabdominal Volume During Laparoscopy
Published on: June 25, 2013
Effect of neuromuscular blockade on opioid consumption in high-risk children undergoing adenotonsillectomy: A
Proshad N Efune1, Paul A Nakonezny2, Pedro Pinales3
1Department of Anesthesiology and Pain Management, University of Texas Southwestern Medical Center, 5323 Harry Hines Blvd, Dallas, TX 75235, USA.

Insights
Neuromuscular blockade did not reduce opioid consumption in children undergoing adenotonsillectomy (AT). This study found no significant difference in opioid use or respiratory events between blockade and no blockade groups for high-risk pediatric patients.
Area of Science:
- Pediatric Anesthesiology
- Respiratory Physiology
- Surgical Outcomes
Background:
- Coughing during pediatric adenotonsillectomy (AT) can necessitate high opioid doses.
- Children at high risk for respiratory complications require careful anesthetic management.
Purpose of the Study:
- To determine if nondepolarizing neuromuscular blockade reduces opioid consumption and postoperative respiratory events in high-risk pediatric AT patients.
- To compare outcomes between children receiving neuromuscular blockade versus no blockade.
Main Methods:
- A randomized, controlled trial involving 172 children (2-12 years) undergoing AT with planned postoperative admission.
- Participants were randomized to receive neuromuscular blockade or no blockade.
- Primary outcome: cumulative opioid consumption; Secondary outcomes: respiratory events and low minute ventilation (MV).
Main Results:
- No significant difference in cumulative opioid consumption between the neuromuscular blockade group and the no blockade group.
- Postoperative respiratory events occurred in 49% of the blockade group vs. 59% of the no blockade group.
- Low MV events were more frequent in the blockade group (38%) compared to the no blockade group (25%).
Conclusions:
- Neuromuscular blockade did not reduce opioid consumption in high-risk pediatric AT patients.
- The use of neuromuscular blockade is not supported for reducing opioid consumption in this population.
- Further research may be needed to explore alternative strategies for managing respiratory complications.
Background:
Protective reflexes like coughing occur frequently during pediatric adenotonsillectomy (AT) and are difficult to blunt with anesthetics, potentially leading to higher than necessary opioid administration. Our objective was to evaluate if nondepolarizing neuromuscular blockade reduces opioid consumption and postoperative respiratory events, compared to no blockade, in children at high-risk for respiratory complications after AT.
Methods:
We conducted a patient- and assessor-blinded, superiority, randomized, controlled trial at a pediatric hospital between April and September 2024. We enrolled 172 children, 2-12 years of age, undergoing AT with pre-planned postoperative admission due to: age < 3 years, severe obstructive sleep apnea, or obesity. Participants were randomized to receive neuromuscular blockade or no blockade. Our primary outcome was cumulative intra- and postoperative opioid consumption until 24 h post-AT, or discharge, whichever occurred first. Secondary outcomes included respiratory events in PACU and on the ward until 24 h post-AT or discharge, whichever occurred first, and low minute ventilation (MV) in the PACU measured using a respiratory volume monitor.
Results:
There was no difference in cumulative opioid consumption between groups (0.209 [SE, 0.009] versus 0.188 [SE, 0.009] IV MME kg-1; difference 0.021; 95% CI -0.005 to 0.047) or intraoperative opioid administration (0.144 [SE, 0.006] versus 0.133 [SE, 0.006] IV MME kg-1; difference 0.011; 95% CI -0.007 to 0.029). Postoperative respiratory events occurred in 32/86 (49%) in the blockade group versus 38/86 (59%) in the no blockade group (aOR 0.55 95% CI 0.26 to 1.12). Low MV events occurred in 33/86 (38%) in the blockade group and 21/84 (25%) in the no blockade group (difference 13%, 95% CI -1 to 27%).
Discussion:
Among children at high risk of post-AT respiratory events, anesthesia with neuromuscular blockade compared with no blockade did not reduce opioid consumption. The findings do not support the use of neuromuscular blockade for this purpose.
Trial Registration:
Clinicaltrials.gov identifier NCT06225466 FUNDING: Merck Investigator Studies Program.
Related Concept Videos
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:25
Analgesia and Pain Management
 01:17
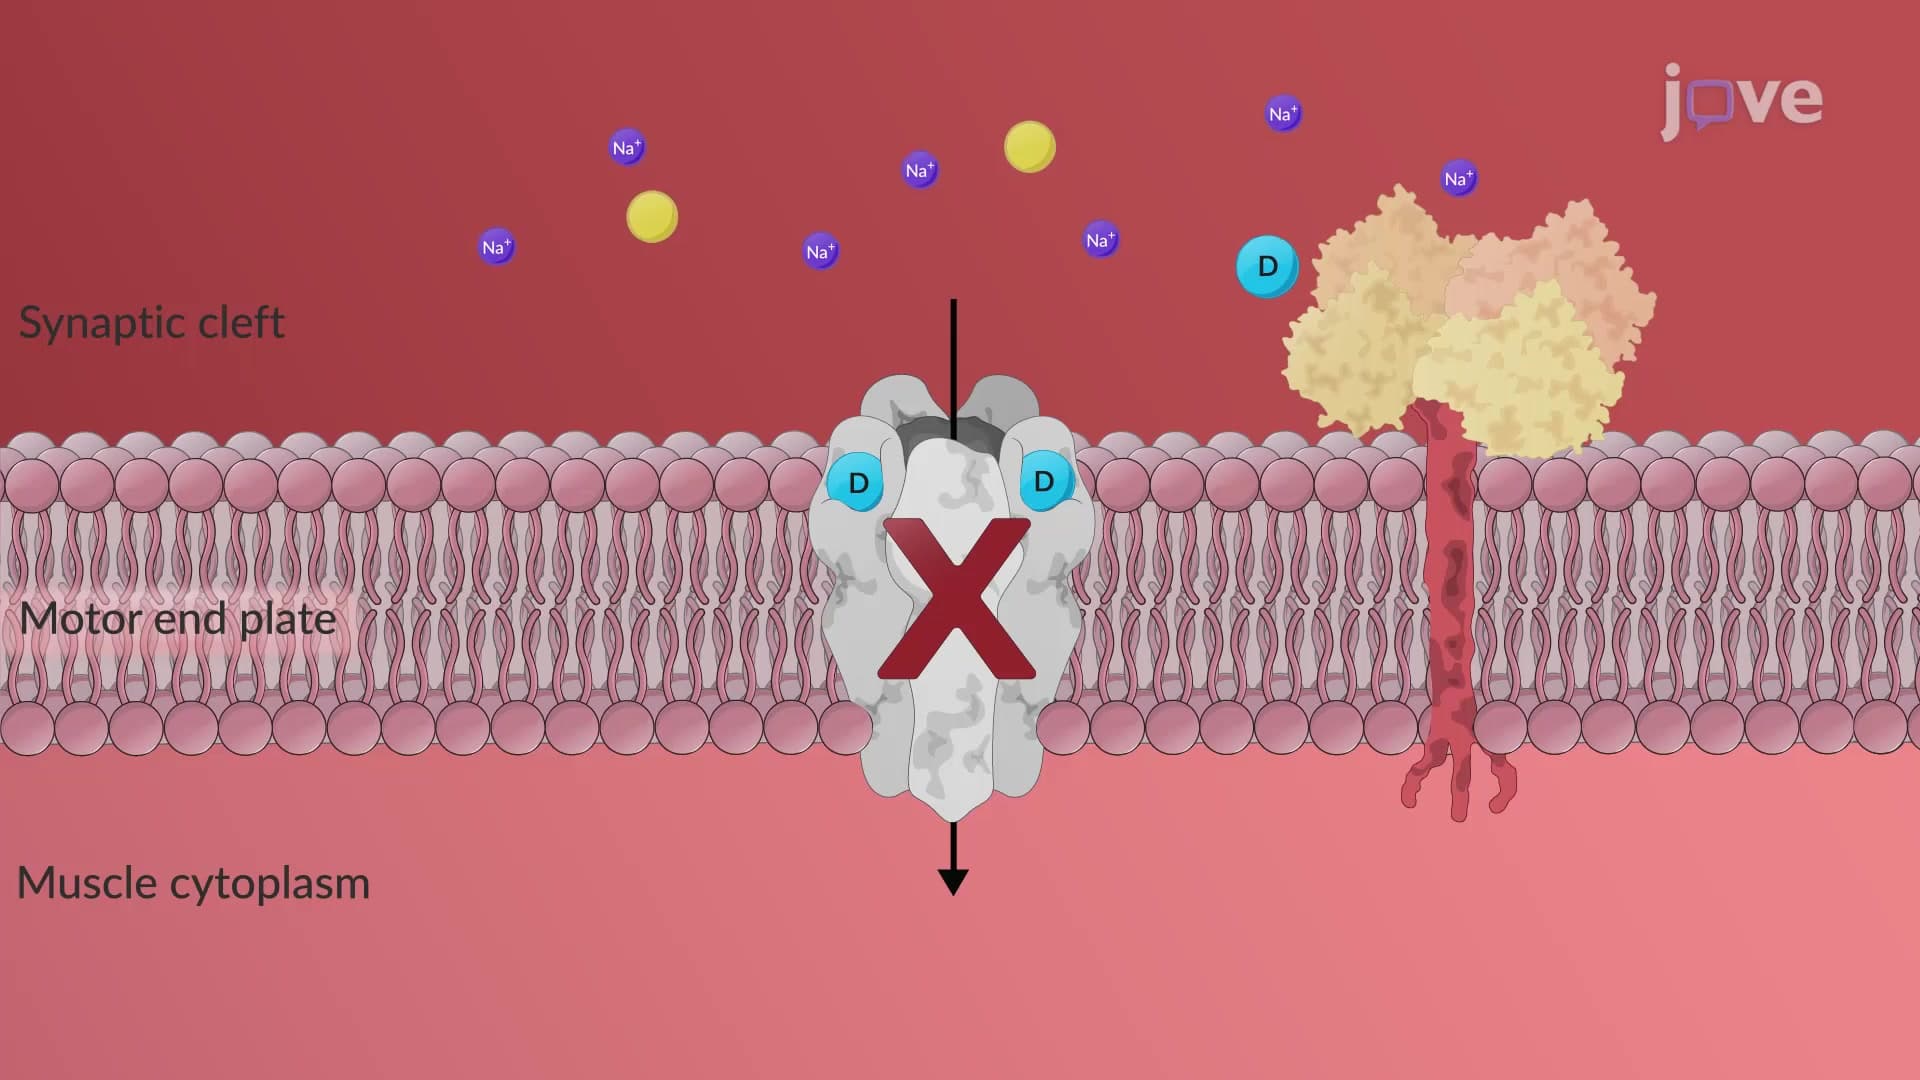
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...