Related Experiment Video
Updated: Jul 3, 2026
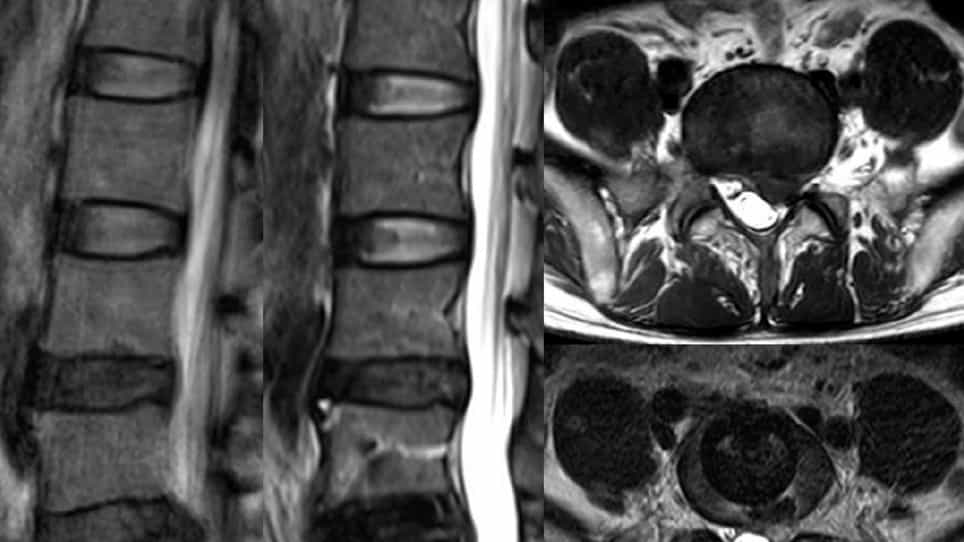

Clinical Application of Microscope-Assisted Minimally Invasive Anterior Lumbar Interbody Fusion
Published on: June 16, 2023
Preoperative CT-Based Finite Element Vertebral Modulus Analysis Predicts Bone Quality-Related Complications After
Gregory Chang1, Chamith S Rajapakse2,3, Travis C Philipp4
1Department of Radiology, New York University Langone Health, 660 1st Ave, New York, NY, 10016, USA.

Study Design:
Retrospective single-center cohort study.
Objective:
To evaluate whether preoperative CT-based finite element analysis (FEA) of vertebral bone modulus predicts bone quality-related complications after lumbar spine fusion.
Summary Of Background Data:
In spine surgery patients, poor bone quality increases the risk of proximal junctional kyphosis/failure, pedicle screw loosening, adjacent segment disease, and pseudoarthrosis, leading to higher revision rates. DXA-based areal bone mineral density (BMD) often fails to identify high-risk patients, particularly in degenerative spines. Three-dimensional CT-based methods, such as Hounsfield units (HU), volumetric BMD, and CT-based FEA, may better capture vertebral mechanical competence by integrating density and microarchitecture.
Methods:
Patients undergoing lumbar fusion at a single academic center in 2017 with ≥2-year follow-up were included (n=85) and classified by the presence of bone quality-related complications. For L1-L5 on preoperative CT, trabecular VOIs were analyzed to obtain mean HU, phantomless-calibrated BMD, and FEA-derived bone modulus. Group differences were assessed with independent-samples t tests, and ROC analysis and multivariable logistic regression examined associations with complication status.
Results:
Thirty-one patients (36.5%) experienced ≥1 bone quality-related complication; 18 had ≥2 events. Bone modulus was significantly lower in the complication cohort (-15.7% to -23.2%; all p≤0.02), whereas HU and BMD differences were nonsignificant. Bone modulus showed greater ability to distinguish patients with and without complications (AUC 0.65-0.70; all P<0.03), while HU and BMD did not (AUC ~0.57-0.60; all P>0.10). Multivariable models including modulus, BMD, and demographics achieved AUC up to 0.81 at L5 (P<0.001).
Conclusion:
Preoperative CT-based FEA of vertebral bone modulus outperforms HU and BMD in identifying lumbar fusion patients at risk for bone quality-related complications and may provide a useful adjunct for preoperative risk stratification and surgical planning.