Related Experiment Videos
Finerenone Across the Cardiovascular-Kidney-Metabolic Continuum: From Mechanistic Rationale to Clinical Positioning-A
Jacek Kubica1,2, Aldona Kubica1,2, Jakub Ratajczak1
1Collegium Medicum, Nicolaus Copernicus University, 85-094 Bydgoszcz, Poland.

Abstract:
The cardiovascular-kidney-metabolic (CKM) syndrome has emerged as an integrated framework linking obesity, type 2 diabetes, chronic kidney disease (CKD), and heart failure with preserved or mildly reduced ejection fraction through shared mechanisms including inflammation, oxidative stress, endothelial dysfunction, and fibrosis. Persistent mineralocorticoid receptor overactivation plays a central role in this continuum, contributing to progressive cardiac and renal injury despite optimized renin-angiotensin system blockade. Finerenone, a selective non-steroidal mineralocorticoid receptor antagonist, has therefore gained increasing attention as a targeted strategy to reduce residual cardiorenal risk. This narrative review summarizes the mechanistic rationale and clinical evidence supporting finerenone across the CKM spectrum. Experimental data indicate that finerenone attenuates inflammation, fibrosis, myocardial hypertrophy, and adverse remodeling, while proteomic and translational analyses suggest biological complementarity with sodium-glucose cotransporter 2 inhibitors. Clinically, pivotal randomized trials have demonstrated that finerenone reduces kidney disease progression and major cardiovascular events in patients with CKD and type 2 diabetes, while the FINEARTS-HF trial extended these benefits to patients with heart failure with mildly reduced or preserved ejection fraction by reducing worsening heart failure events. Additional subgroup, pooled, and meta-analytic data reinforce the consistency of these effects across a broad range of cardiorenal phenotypes. Taken together, current evidence positions finerenone as an important component of contemporary CKM management, particularly in patients with diabetic CKD and selected heart failure phenotypes. Its principal value lies in targeting residual inflammatory and fibrotic risk beyond conventional hemodynamic and metabolic control. Future progress will depend on earlier phenotype recognition, improved implementation and adherence, and wider adoption of pathway-oriented combination therapy across the cardiorenal continuum.
Related Concept Videos
 01:06
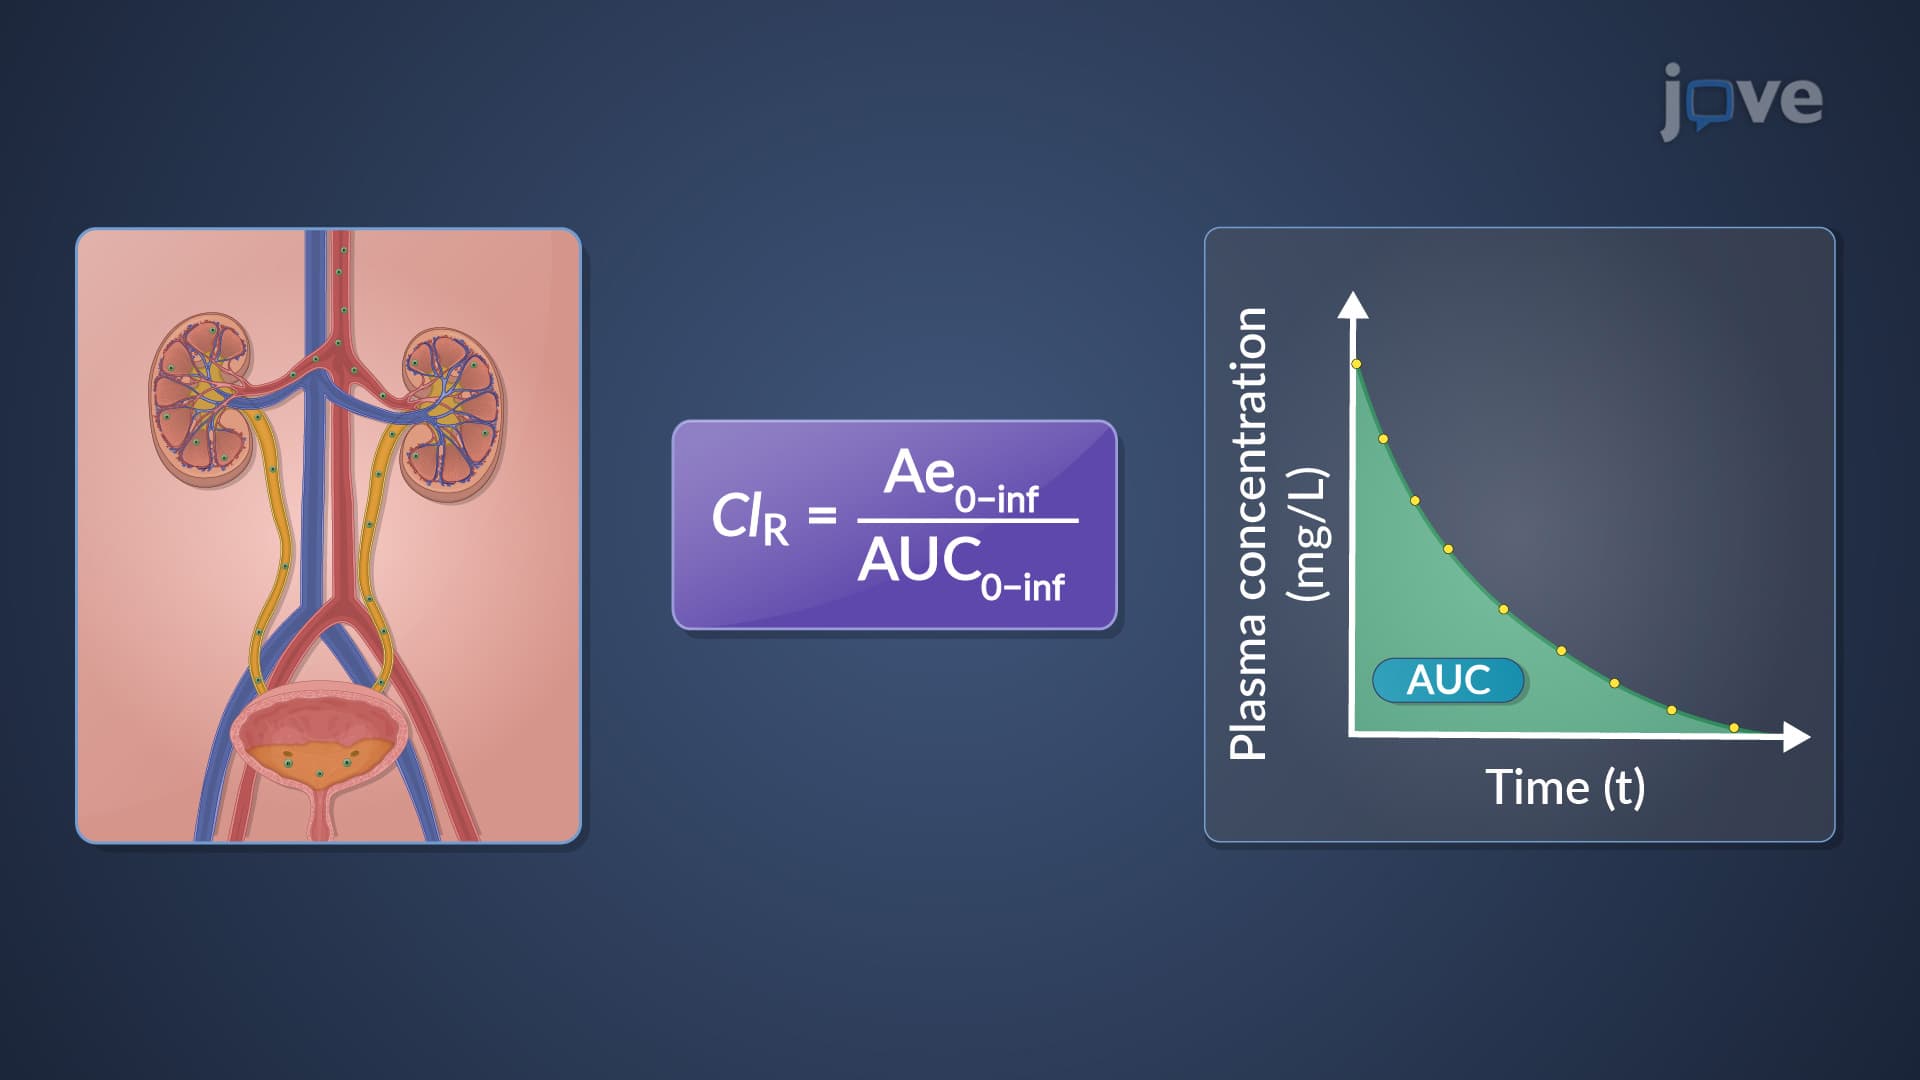
Renal Drug Clearance: Overview
Renal clearance can be calculated using different methods. One approach is to divide the urinary drug excretion rate by the plasma drug concentration. This method directly measures renal clearance, indicating the kidneys' efficiency in...
 01:15
Renal Drug Excretion: Overview
A nephron consists of two primary structures: the renal corpuscle and the renal tubule. The renal corpuscle contains the glomerulus, a network of capillaries where the first step of renal excretion, glomerular filtration, occurs. Blood pressure forces water, ions, and small molecules out...
 01:31
Factors Affecting Renal Clearance: Drug's Physicochemical Properties and Plasma Levels
One important factor is the drug's molecular size. The kidneys readily excrete smaller molecules below 300 Daltons (Da). On the other hand, molecules weighing between 300 and 500 Da are excreted through both urine and bile. Larger molecules above 500 Da tend to be excreted less...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:29
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:29
Physiology of the Genitourinary System I: Renal Blood Flow and Glomerular Filtration