Related Experiment Video
Updated: May 17, 2026
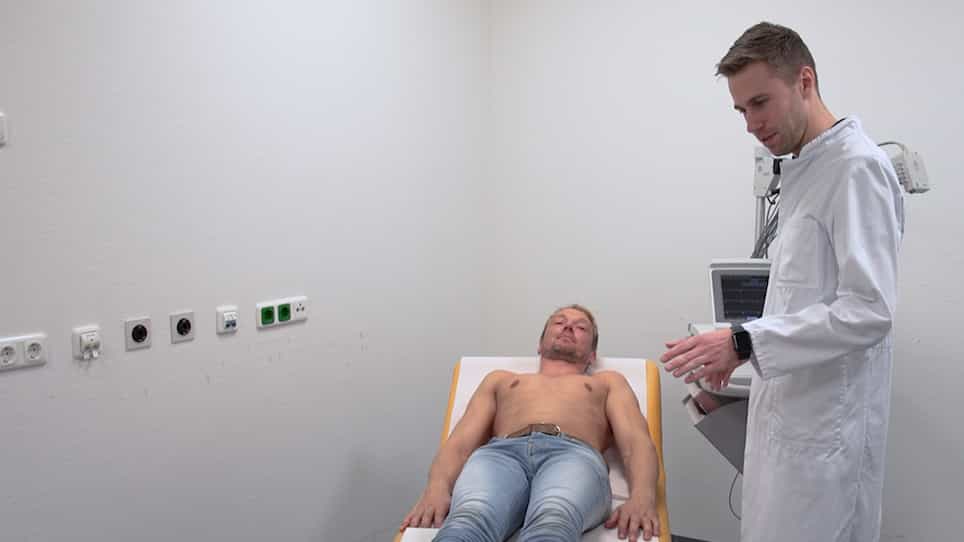

Patient Directed Recording of a Bipolar Three-Lead Electrocardiogram using a Smartwatch with ECG Function
Published on: December 11, 2019
Prevalence and Recovery of Arrhythmia-Induced Cardiomyopathy in Patients With Newly Diagnosed Heart Failure Using a
Joerg Yogarajah1, Jana Dannebaum1, Ahmed Halim1
1Department of Cardiology, Kerckhoff Heart and Thorax Center, Campus Kerckhoff, Justus Liebig University Giessen, Bad Nauheim, Germany.

Background:
Arrhythmia-induced cardiomyopathy (AIC) is a potentially reversible cause of heart failure triggered by different sustained arrhythmias, but data on its real-world prevalence, recognition, and outcomes are limited.
Objective:
To assess frequency, predictors, and outcomes of AIC in patients with newly diagnosed left ventricular systolic dysfunction (LVSD) and concurrent arrhythmia undergoing early rhythm control with a wearable cardioverter-defibrillator (WCD).
Methods:
Among 780 WCD-treated patients (2017-2023), those with newly diagnosed idiopathic LVSD (LVEF < 35%) and persistent arrhythmia (atrial fibrillation/flutter or > 20% ventricular ectopy) were included. Diagnostic workup comprised echocardiography, coronary angiography, and cardiac MRI. Effective rhythm control was achieved via cardioversion, antiarrhythmic drugs, and/or ablation. Follow-up was up to 6 months. AIC was defined as LVEF improvement > 15% with restored sinus rhythm or suppressed ventricular ectopy.
Results:
Of 780 WCD patients, 142 (18.2%) had LVSD with arrhythmia; 74 idiopathic cases were analyzed. At a mean follow-up of 138 days (4.5 months), 54 patients (73%) maintained sinus rhythm or suppressed ventricular ectopy after rhythm control, of whom 32 (59.3%) fulfilled AIC criteria. LVEF improved from 28% to 43% in AIC; 56.3% of AIC patients fully recovered (> 50%). Non-AIC patients had larger LV dimensions, lower heart rates, more mitral regurgitation, and a non-significant trend toward more frequent late gadolinium enhancement (p = 0.073). No parameter reliably predicted AIC; LVEF < 25% predicted lack of full recovery (p = 0.040). No appropriate WCD shocks occurred. ICD indication decreased from 100% to 17% post-therapy in AIC and Non-AIC patients (3.1% vs. 36.4%, p = 0.001).
Conclusions:
AIC related to atrial fibrillation, flutter, or frequent ventricular ectopy is more prevalent and reversible than often recognized. Early rhythm control under WCD protection, supported by comprehensive diagnostics, allows identification of reversible LVSD and may help prevent unnecessary ICD implantation.

Related Concept Videos
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:30
Dysrhythmias V: Evaluating Dysrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:29
Cardiomyopathy V: Interprofessional Care
 01:30
Pulse rhythm
Conversely, an irregular pulse pattern is termed dysrhythmia, stemming from disruptions in cardiac muscle...
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy