Related Experiment Video
Updated: May 19, 2026

Management of the Uncinate Process in No-Touch Laparoscopic Pancreaticoduodenectomy
Published on: May 5, 2023
Surgical management of pancreatic cancer: an overview
Daniel Chun Pong Kwok1, Kenneth Siu Ho Chok1
1Division of Hepatobiliary and Pancreatic Surgery, Department of Surgery, Prince of Wales Hospital, Hong Kong, China.

Abstract:
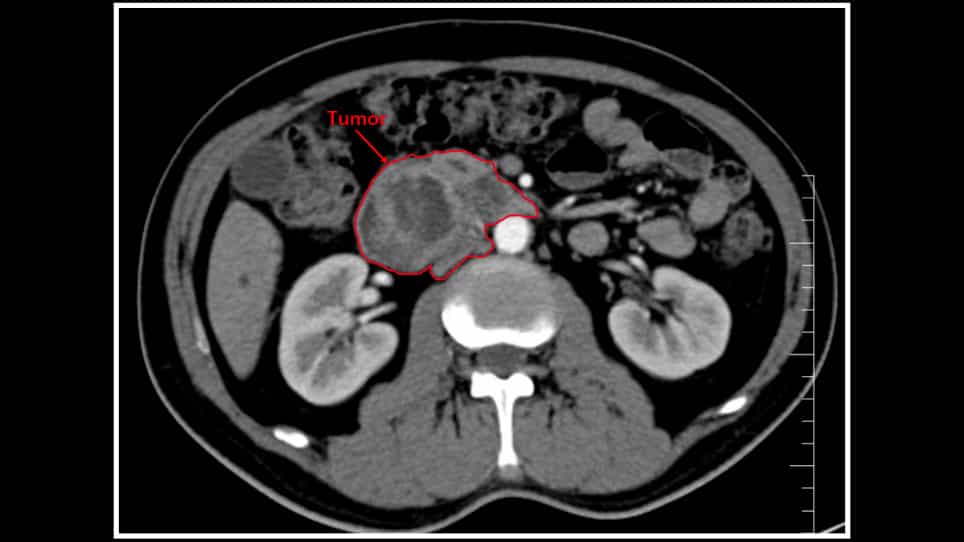
Pancreatic ductal adenocarcinoma (PDAC) is notorious for its aggressive tumour biology as well as its generally poor prognosis despite advances in systemic treatment. Oncological surgery with curative intent remains the hope for a potential cure for patients with pancreatic cancer. Apart from the usual tumour classification based on primary tumour, regional lymph nodal, and distant metastasis (TNM) staging, pancreatic cancer is also categorised into resectable, borderline resectable and locally advanced based on the anatomical relationship of the tumour with the adjacent important vasculature, namely superior mesenteric artery (SMA) and superior mesenteric vein (SMV), celiac trunk, common hepatic artery (CHA), portal vein (PV) to decide on resectability. The anatomical location of the pancreatic tumour and its extent decide the option of surgery, usually pancreaticoduodenectomy for head and uncinate tumours, whereas distal pancreatectomy for tumours in the body or tail. Sometimes, total pancreatectomy is indicated for extensive infiltrative tumours or multifocal tumours to achieve a negative resection margin. Variations in surgical techniques have been described to reduce the complications, e.g., postoperative pancreatic fistula (POPF), and the related morbidity or even mortality. However, no single technique has been shown to be consistently superior to the others in the literature. To further improve the resection margin clearance, extended resection techniques, namely radical antegrade modular pancreatosplenectomy (RAMPS), distal pancreatectomy with celiac axis resection (DP-CAR) (also known as modified Appleby procedure), were also described, but the benefit on overall survival is yet to be proven. For patients with unresectable or locally advanced pancreatic tumour, sometimes surgical bypass with palliative intent could be performed to relieve the biliary or duodenal obstruction. There is a potential role of tumour ablative therapy, either by thermal energy or non-thermal [e.g., irreversible electroporation (IRE), radiofrequency ablation, or microwave ablation], for local tumour control; however, evidence is still limited to conclude its value. Management of PDAC is often challenging for the surgeon and very often necessitates a multidisciplinary meeting for conjoint decision and collaboration for subsequent tailored management.
Related Concept Videos
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease