Related Experiment Video
Updated: May 23, 2026
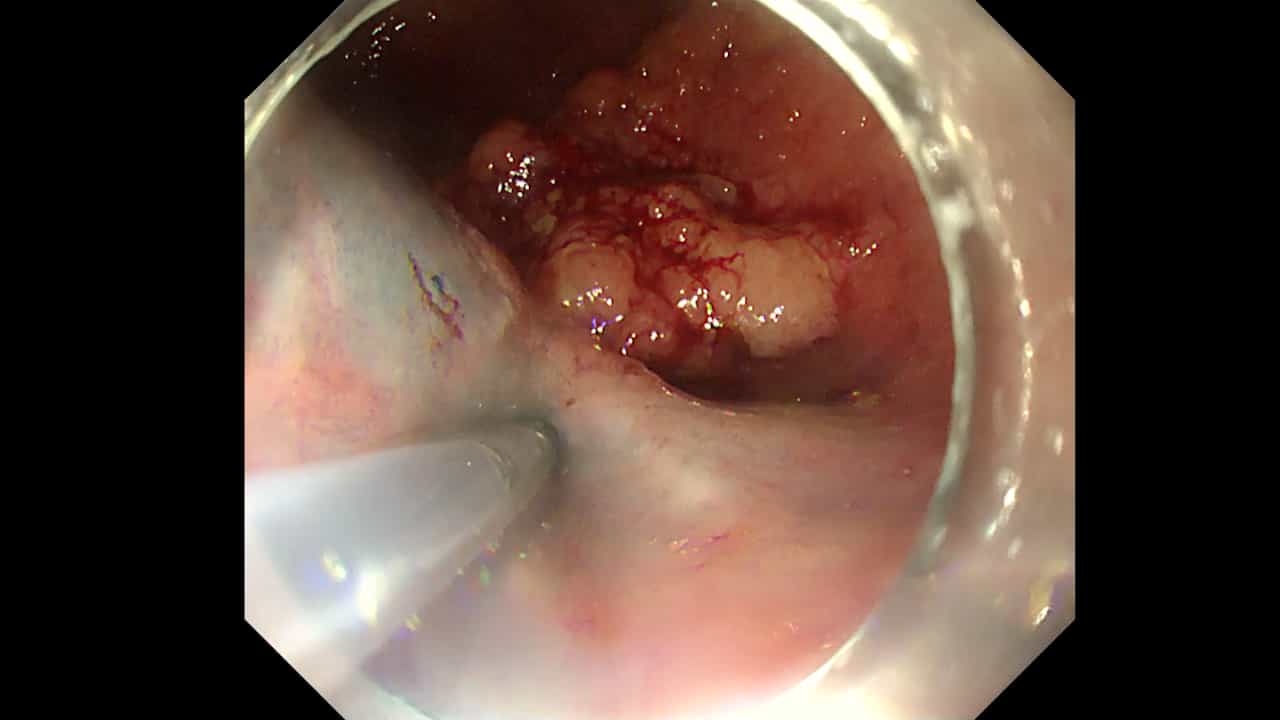

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
A novel mucosal zipper endoscopic resection technique versus endoscopic full-thickness resection for gastric
Zhenkai Luo1, Rongwei Ruan1, Jiangping Yu1
1Department of Endoscopy, Zhejiang Cancer Hospital, Hangzhou Institute of Medicine (HIM), Chinese Academy of Sciences, Banshan Road 1, Gongshu District, Hangzhou, 310022, Zhejiang, China.

Background:
Mucosal zipper endoscopic resection (MZER) is a novel technique developed at our center for the treatment of gastric submucosal tumors (SMTs). This study describes the technique and compares its efficacy and safety with endoscopic full-thickness resection (EFTR).
Methods:
This retrospective study included 309 patients with gastric SMTs treated with MZER (n = 143) or EFTR (n = 166) between January 2021 and June 2025. Clinicopathological characteristics, perioperative outcomes, and follow-up outcomes were compared. Univariable and multivariable analyses were performed for wound closure time, and subgroup analyses were conducted according to tumor size (≤ 1 vs. > 1 cm).
Results:
The en bloc resection rate was 100% in both groups. Compared with EFTR, MZER was associated with a shorter median wound closure time (8 vs. 15 min, absolute difference, 7 min; P < 0.001), shorter postoperative stay (3 vs. 5 days, absolute difference, 2 days; P < 0.001), and lower total cost (USD 2285 vs. USD 2986, absolute difference, USD 701; P < 0.001). Postoperative abdominal pain (7.0 vs. 20.5%, absolute difference, 13.5 percentage points; P = 0.001) and fever (11.2 vs. 21.7%, absolute difference, 10.5 percentage points; P = 0.015) were less frequent in the MZER group. In multivariable analysis, MZER remained significantly associated with shorter wound closure time. In subgroup analyses, differences in wound closure time, postoperative stay, and cost were observed in both tumor size subgroups, whereas differences in abdominal pain and fever were significant only in the > 1 cm subgroup. No recurrence was observed during a median follow-up of 23 months.
Conclusion:
MZER was associated with comparable resection success and a favorable safety profile, with improved perioperative efficiency in this cohort.