Related Experiment Video
Updated: May 25, 2026
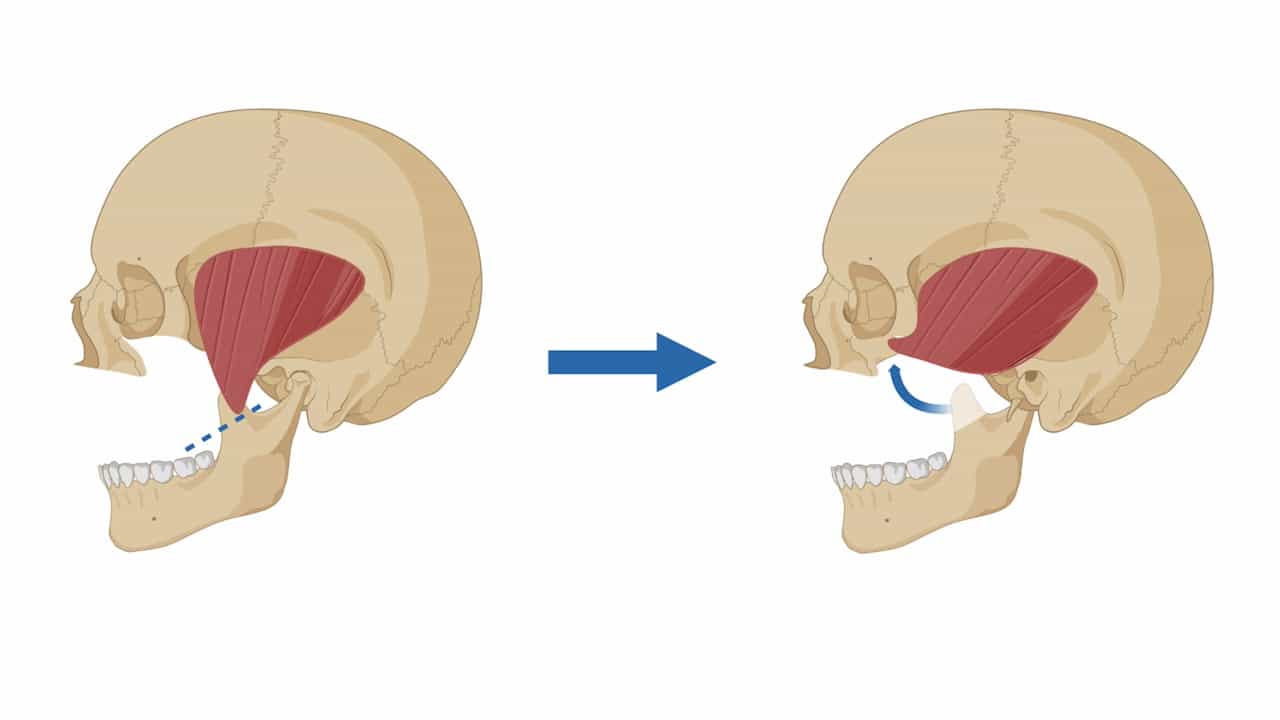
Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Comparative assessment of the infraorbital canal course in patient with cleft lip and palate with control group: a
Abdolaziz Haghnegahdar1, Salma Tabatabaei2, Fatemeh Khandani3
1Associate Professor, Oral and Dental Disease Research Center, Oral and Maxillofacial Radiology, School of Dentistry, Shiraz University of Medical Sciences, Shiraz, Iran.

Aim:
This study aimed to assess the course of the infraorbital canal (IOC) in cleft lip and palate (CLP) patients compared to a matched control group using CBCT imaging, evaluating the potential anatomical variations that may influence surgical risks in the maxillofacial region.
Materials And Methods:
In this cross-sectional study, CBCT scans of 67 CLP patients (50 unilateral, 17bilateral) were evaluated alongside 67 age- and sex-matched controls. IOC courses were classified into three types using the Ference method: Type I (within sinus roof), Type II (juxtaposed), and Type III (protruded). Infraorbital foramen (IOF) dimensions and distances to the orbital floor, as well as the presence of Haller cells and concha bullosa, were recorded. Statistical analyses included chi-square tests and odds ratios using SPSS v25.
Results:
The embedded IOC type (Type I) was most prevalent (49.6%), followed by Type II (34.3%) and Type III (16.0%), with no significant difference between cleft and control groups. IOF-orbital floor distance was significantly shorter on the cleft side (P < 0.001). No association was found between cleft status and the presence of Haller cells or concha bullosa. IOC course symmetry between sides was moderate in both groups (kappa 0.4-0.6).
Conclusion:
IOC course distribution was not significantly influenced by the presence of cleft deformities. However, the reduced IOF-orbital floor distance in cleft patients may have clinical relevance during surgical planning in the maxillofacial region.
