Related Experiment Video
Updated: May 26, 2026
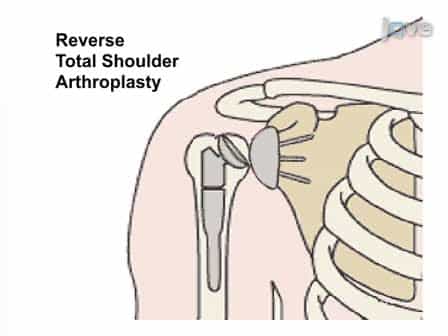
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Defining surgeon experience thresholds for the reduction in complications and revisions after shoulder arthroplasty:
Mohammad Daher1, Muhammad Hamza Ilyas2, Diego Gonzalez-Morgado3
1Department of Shoulder and Elbow Surgery, Rothman Orthopaedics, Philadelphia, PA, USA.

Background:
Shoulder arthroplasty utilization has increased substantially, with a growing proportion of cases performed by surgeons early in the learning curve. Surgeon-volume definitions vary widely across the literature, and although higher volume is generally associated with better outcomes, there is no consensus on the thresholds that define high volume. This study aimed to determine shoulder arthroplasty cases/yr thresholds at which complication and revision risks diverge between low- and high-volume surgeons.
Methods:
PubMed, Cochrane, and Google Scholar were queried through December 2025. Inclusion criteria consisted of comparative studies evaluating the number of complications and revisions after shoulder arthroplasty across different categories of surgeon experience. Five different thresholds of cases/yr were established to perform the analysis and define high- and low-volume surgeons: 5 cases/yr, 10 cases/yr, 14 cases/yr, 20 cases/yr, and 25-28 cases/yr.
Results:
Eight studies with 332,542 patients were included. At the 5 cases/yr threshold, low-volume surgeons had higher odds of complications (odds ratio [OR] = 1.41; 95% confidence interval [CI], 1.28-1.55; P< .001) and revision (OR = 1.41; 95% CI, 1.28-1.57; P< .001). At the 10 cases/yr threshold, there were no differences in complications (OR = 1.21; 95% CI, 0.94-1.56; P= .14) or revision (OR = 1.18; 95% CI, 0.90-1.54; P= .22). At the 14 cases/yr threshold, revisions were similar (OR = 1.15; 95% CI, 0.89-1.48; P= .28). At the 20 cases/yr threshold, revision did not differ (OR = 1.15; 95% CI, 0.87-1.52; P= .34). At the 25-28 cases/yr threshold, low-volume surgeons had higher odds of complications (OR = 1.39; 95% CI, 1.11-1.75; P= .004) and revision (OR = 1.22; 95% CI, 1.15-1.30; P< .001).
Conclusion:
This study identified surgeon-volume thresholds for shoulder arthroplasty of 5 cases/yr and 25-28 cases/yr, which may possibly define low-to-medium and medium-to-high-volume thresholds, respectively. Patients treated by surgeons below these thresholds had higher risks of complications and revision compared with those treated by surgeons above the respective thresholds.