Related Experiment Video
Updated: May 28, 2026
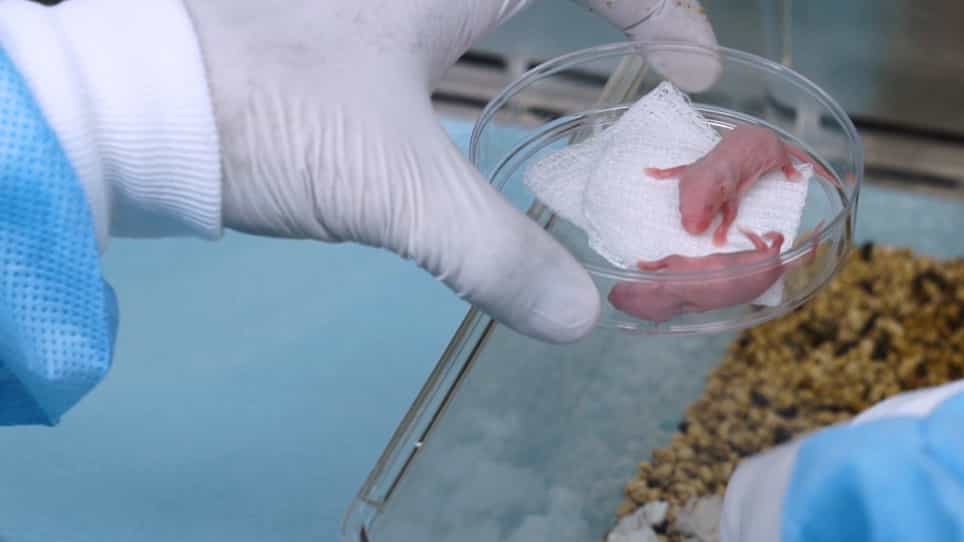
Chronic, Acute, and Reactivated HIV Infection in Humanized Immunodeficient Mouse Models
Published on: December 3, 2019
Pre-ART Platelet-to-Lymphocyte Ratio and Neutrophil-to-Lymphocyte Ratio and the Risk of Non-AIDS-events, AIDS-Events,
Paola Saltini1,2, Alessandro Cozzi-Lepri3, Giorgio Bozzi1
1Infectious Diseases Unit, Fondazione IRCCS Ca' Granda Ospedale Maggiore Policlinico, Milan, Italy.

Background:
Among people with HIV (PWH) on antiretroviral therapy (ART), serious non-AIDS-events (SNAEs) are linked to inflammation. Neutrophil-to-lymphocyte ratio (NLR), platelet-to-lymphocyte ratio (PLR) and lymphocyte-to-monocyte ratio (LMR) are inflammatory biomarkers. We investigated their performance in PWH.
Methods:
PWH enrolled in the national cohort Italian Cohort Naive Antiretrovirals who started ART over 1997-2021 with measures of NLR, PLR, and/or LMR within 6 months pre-ART ("baseline") were included. Biomarkers were grouped using tertiles of their distribution (Q1, Q2, and Q3). Association between baseline biomarkers values and risk of SNAEs, AIDS, and all-cause mortality were tested using Kaplan-Meier and Cox proportional hazard models adjusting for baseline age, CD4 + count, human immunodeficiency virus-ribonucleic acid (HIV-RNA), HCV-status, and year of starting ART.
Results:
We included 9248, 8727, and 1090 individuals in the PLR, NLR, and LMR analyses, respectively: 77% male, median age 38. Baseline PLR, NLR, and LMR mean values were 248.9, 2.7, and 8.2, respectively. After adjusting for confounders, the risk of SNAEs was higher for Q1-PLR vs Q2 and Q3 [adjusted-hazard ratio (HR) 0.76 (95% CI: 0.64 to 0.90) and 0.78 (95% CI: 0.66 to 0.94), respectively], and mortality [adjusted-HR 0.54 (95% CI: 0.41 to 0.70), and 0.68 (95% CI: 0.53 to 0.87), respectively], and the risk of AIDS was lower for Q2-PLR (adjusted-HR = 0.74, 95% CI: 0.60 to 0.90). Mortality was higher for Q3-NLR [adjusted-HR 1.32 (95% CI: 1.01 to 1.72)]. Q1-LMR showed higher risks of SNAEs, AIDS, and mortality, but this weakened after adjusting for confounders.
Conclusions:
A baseline PLR below 93.2 was associated with SNAEs, AIDS, and mortality, and NLR above 2.04 was associated with mortality. Derived from routinely collected blood parameters, PLR, and NLR may help clinicians identifying PWH at risk of poor outcomes.

