Related Experiment Video
Updated: May 29, 2026


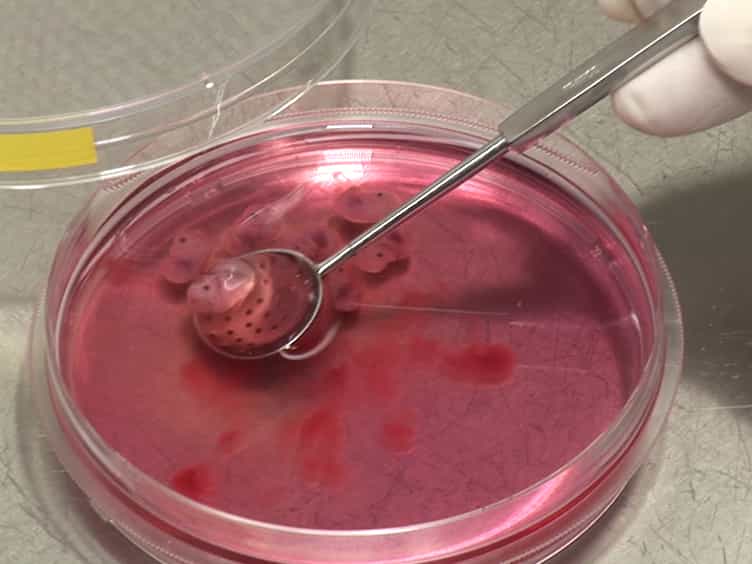
Isolation and Transplantation of Different Aged Murine Thymic Grafts.
Published on: May 13, 2015
Rebooting immunity in congenital athymia: Factors impacting reconstitution with thymus implantation
Samantha Cresoe-Ortiz1, Guglielmo Venturi1, Elizabeth A McCarthy1
1Division of Allergy and Immunology, Department of Pediatrics, Duke University School of Medicine, Durham, NC, USA.

Allogeneic processed thymus tissue-agdc (RETHYMIC) is the only Food and Drug Administration-approved therapy for immune reconstitution in children with congenital athymia. Evaluating factors impacting successful immune reconstitution is necessary to improve outcomes. Using data from 10 open-label, single-arm studies, this retrospective cohort study evaluated 76 children with 1-year survival following thymus tissue implantation. Variables included receipt of immune-suppressing agents, human leukocyte antigen (HLA) matching, preimplantation T cell function, and age at implantation. Outcomes include lymphocyte subsets, T cell function, and naive T cell reconstitution, defined as >100 naive T cells/mm3 at 1-year after implantation. Median total T, B, and NK cell counts at 1 year following implantation were not associated with T cell function at implantation, immune-suppressing therapies, or donor and recipient HLA matching; however, naive T cell counts were higher among those with low T cell function at time of implantation. Younger age at implantation was associated with improved immune reconstitution, supporting the importance of early diagnosis and referral for treatment.
Allogeneic processed thymus tissue-agdc (RETHYMIC) is the only Food and Drug Administration-approved therapy for immune reconstitution in children with congenital athymia. Evaluating factors impacting successful immune reconstitution is necessary to improve outcomes. Using data from 10 open-label, single-arm studies, this retrospective cohort study evaluated 76 children with 1-year survival following thymus tissue implantation. Variables included receipt of immune-suppressing agents, human leukocyte antigen (HLA) matching, preimplantation T cell function, and age at implantation. Outcomes include lymphocyte subsets, T cell function, and naive T cell reconstitution, defined as >100 naive T cells/mm3 at 1-year after implantation. Median total T, B, and NK cell counts at 1 year following implantation were not associated with T cell function at implantation, immune-suppressing therapies, or donor and recipient HLA matching; however, naive T cell counts were higher among those with low T cell function at time of implantation. Younger age at implantation was associated with improved immune reconstitution, supporting the importance of early diagnosis and referral for treatment.

Related Concept Videos
 01:40
Cell-mediated Immune Responses
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:23
Immunological Memory
What is Immunological Memory?
Immunological memory is an integral function of the immune system that allows it to recognize and react more rapidly and effectively to pathogens previously encountered. This feature is...
 01:51
Vaccinations
 01:20
Special Features of Adaptive Immunity
The primary cell types involved in adaptive immunity are T cells and B cells. Each type has a unique role in defending the body against pathogens. T cells are responsible for cell-mediated immunity. They identify and eliminate infected cells directly,...
 01:23
Cells of the Adaptive Immune Response