Related Experiment Video
Updated: May 31, 2026
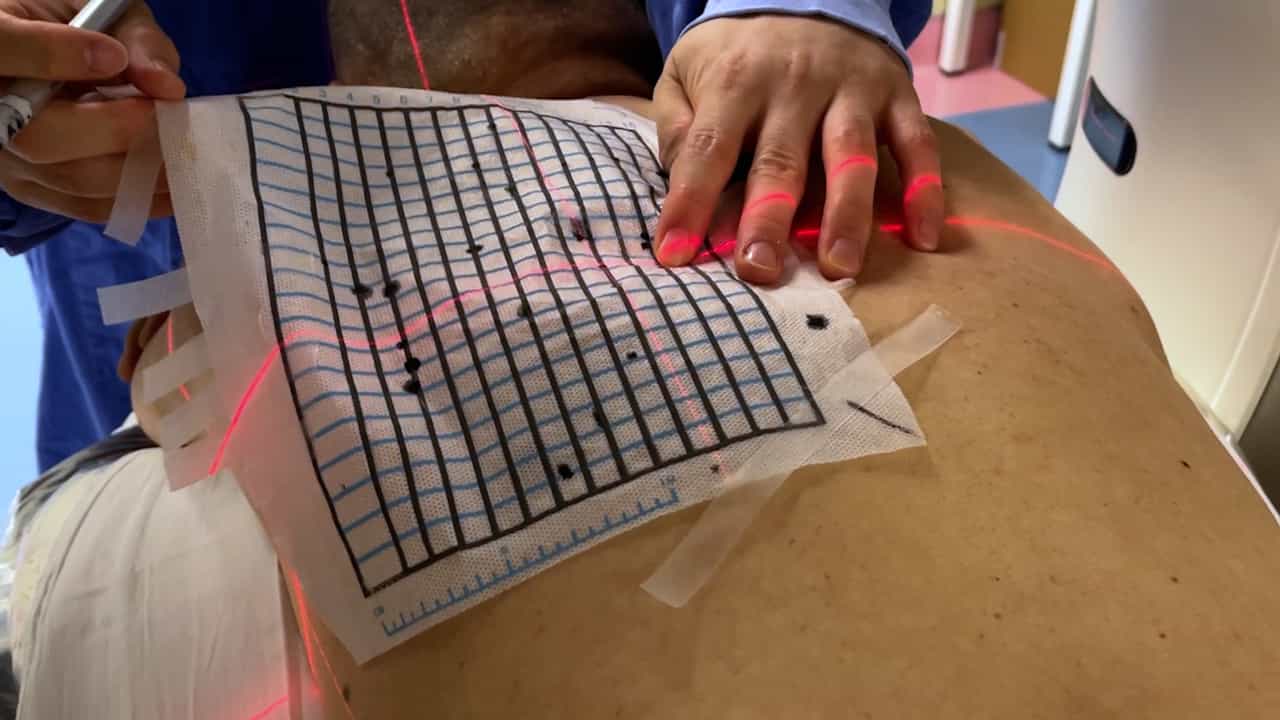

CT-guided Preoperative Localization of Pulmonary Nodules Using a Glucose Test and Tissue Adhesive
Published on: January 30, 2026
Preoperative low-attenuation area on computed tomography is associated with recurrence after curative resection for
Hironobu Samejima1,2, Kensuke Kojima3, Shigeki Shimizu4
1Department of General Thoracic Surgery, NHO Kinki Chuo Chest Medical Center, 1180 Nagasone-cho, Kita-ku, Sakai-shi, Osaka, 591- 8555, Japan.

Background:
Recurrence after curative-intent resection remains a major determinant of long-term outcomes in non-small-cell lung cancer (NSCLC). Preoperative computed tomography (CT)-derived low-attenuation area (LAA) is an objective marker of smoking-related parenchymal injury, but its independent association with postoperative recurrence and the shape of its exposure-response relationship remain incompletely defined.
Methods:
We retrospectively analyzed 660 consecutive patients who underwent R0 resection for NSCLC between 2017 and 2021. LAA was quantified on inspiratory CT as the percentage of lung volume with attenuation values < - 950 Hounsfield units. The primary endpoint was recurrence-free survival (RFS). Prespecified multivariable Cox models adjusted for major clinicopathologic and treatment-related factors, with LAA modeled per 1% increase and dichotomized using a Youden index-derived cutoff. Potential nonlinearity was assessed using restricted cubic splines and a one-knot hinge model. Model performance was summarized using time-specific calibration and decision-curve analysis. Machine learning analyses visualized the LAA-recurrence relationship using random forest partial dependence plots and explored predictor importance using permutation-based methods and a random survival forest.
Results:
Recurrence occurred in 119 patients (18%), including 32 locoregional-only recurrences and 87 distant recurrences with or without locoregional recurrence. Higher LAA was independently associated with shorter RFS (per 1% increase: adjusted hazard ratio [HR], 1.05; 95% confidence interval [CI], 1.01-1.08; P = 0.007). In an exploratory dichotomized analysis using a data-derived 1.3% cutoff, LAA ≥ 1.3% was also associated with shorter RFS (HR, 1.84; 95% CI, 1.20-2.83; P = 0.005). Global spline tests did not show statistically significant nonlinearity across the full LAA distribution; however, prespecified low-range analyses suggested a possible change in the risk gradient around 1%-2% LAA. Machine learning analyses ranked pathologic stage and PD-L1 as the strongest predictors, with LAA contributing additional but smaller prognostic information.
Conclusions:
Preoperative CT-derived LAA was independently associated with postoperative recurrence after R0 resection for NSCLC. LAA may provide complementary host-lung imaging information alongside established clinicopathologic predictors, but the low-range signal and the data-derived 1.3% cutoff should be regarded as hypothesis-generating pending external validation in multicenter cohorts with standardized CT acquisition and quantification.