Related Experiment Video
Updated: Jun 9, 2026

In Silico Clinical Trials for Cardiovascular Disease
Published on: May 27, 2022
The inverse problem of electrocardiography: From a clinical point of view
José Nunes de Alencar1, Gabriel Scarpioni Barbosa2
1Research Division, Dante Pazzanese Cardiology Institute, São Paulo, Brazil.

Background:
The 12-lead electrocardiogram (ECG) records body-surface potentials that represent cardiac electrical activity filtered through the torso. Recovering the original cardiac sources from these surface signals-the inverse problem of electrocardiography-is mathematically ill-posed: multiple distinct source configurations produce identical tracings. This constraint is seldom discussed in clinical practice, yet it underlies many recognized ECG diagnostic limitations.
Methods:
This narrative review provides a clinician-oriented summary of the forward and inverse formulations, and then organizes ECG interpretive pitfalls into five mechanistic categories: volume-conductor filtering, source-model ambiguity, cardiac motion during repolarization, patient-specific anatomy and lead-placement variability, and signal noise and filtering. Each category is linked to quantitative clinical data and to practical reporting recommendations.
Results:
Volume-conductor attenuation limits VA localization accuracy to 38.9% at the AHA-segment level. Source ambiguity allows 59% of combined anterior-inferior ST elevation to originate from RCA rather than LAD occlusion, and permits unrelated diseases (pulmonary embolism, arrhythmogenic cardiomyopathy) to produce identical repolarization patterns. Cardiac motion during repolarization introduces time-variant geometric distortion independent of pathology. The Mason-Likar lead system erases established inferior infarctions and shifts QRS axes by up to 60°. Fragmented QRS detects scar (sensitivity 68%, specificity 80%) but fails territorial localization (sensitivity 1.7%). Electrocardiographic imaging reduces localization error but cannot recover spatial detail lost to the torso filter.
Conclusions:
The inverse problem imposes identifiability limits on every 12-lead ECG. Territorial labels should be treated as probabilistic and corroborated with imaging or hemodynamics when localization carries therapeutic consequences.

Related Concept Videos
 01:29
Electrocardiogram
Three major waveforms are present in a typical ECG recording: the P wave, the QRS complex, and the T...
 01:28
Electrocardiogram Fundamentals
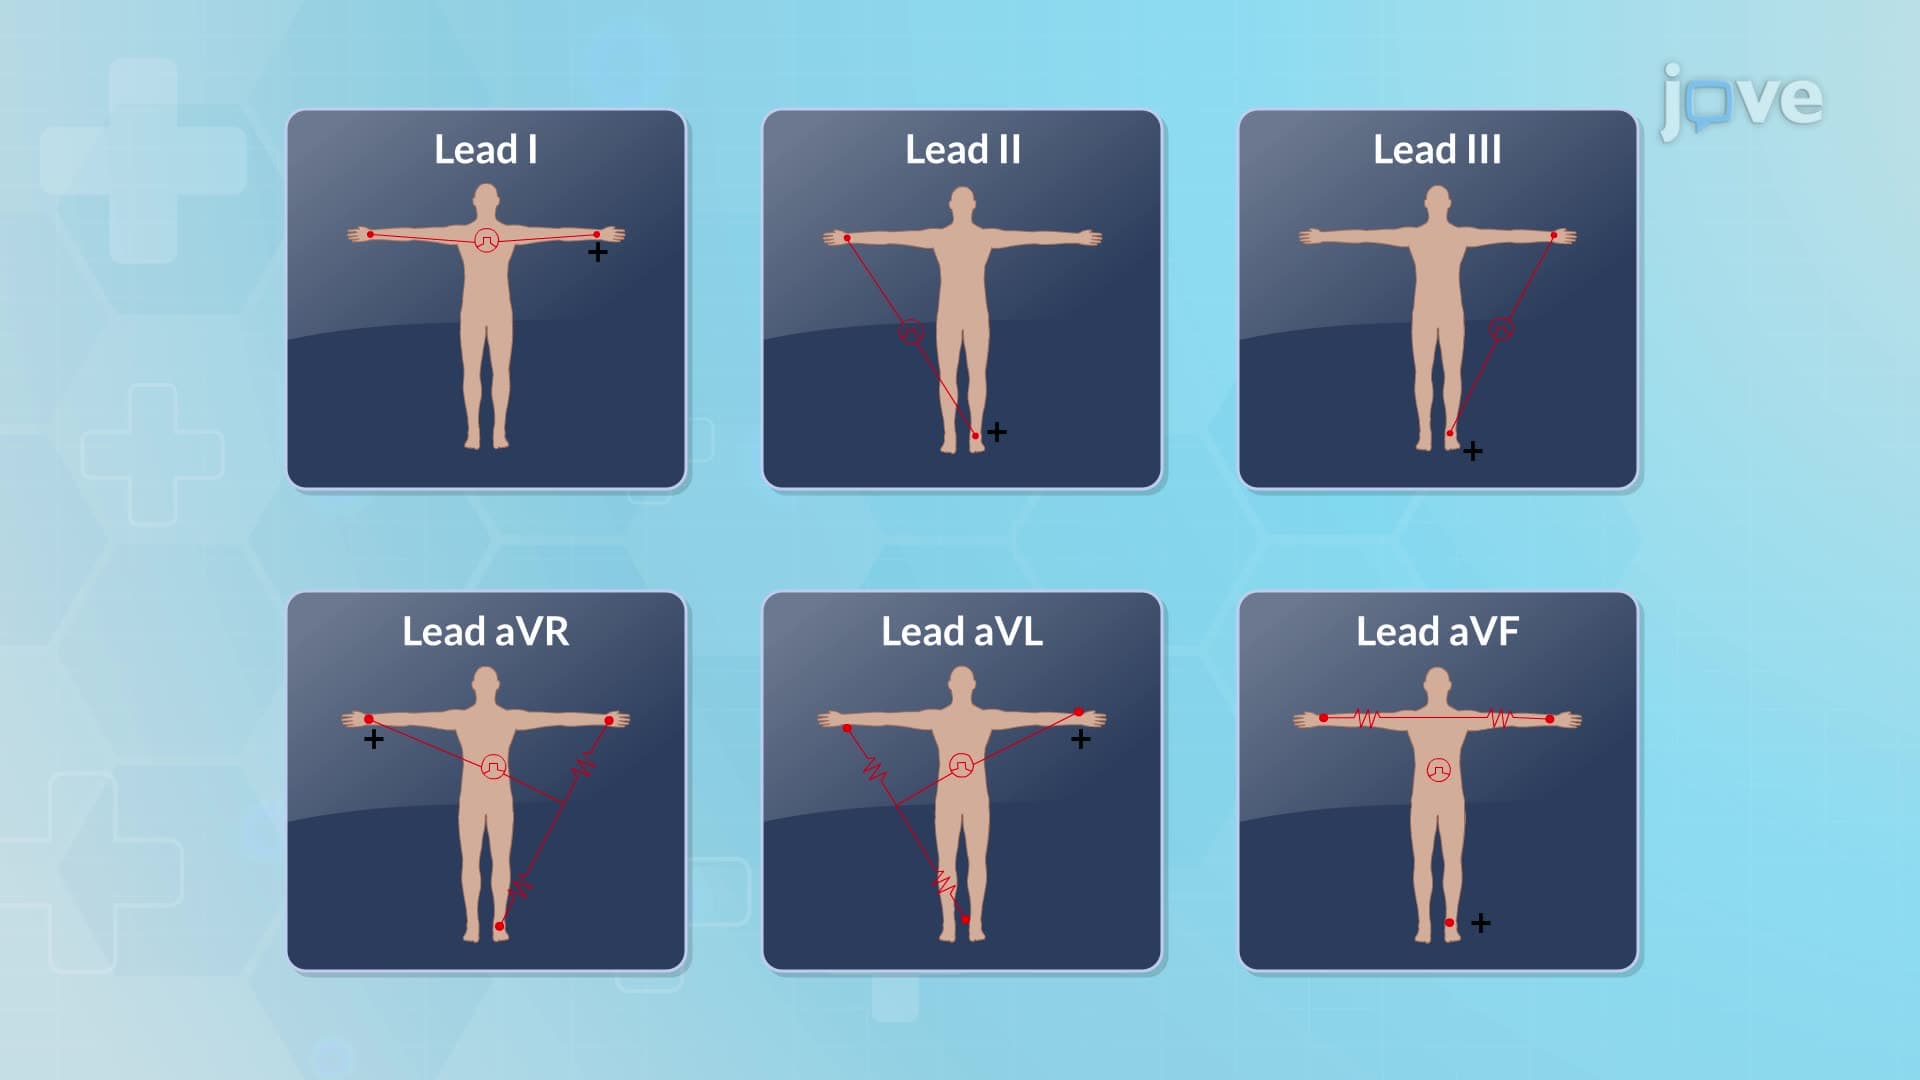
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
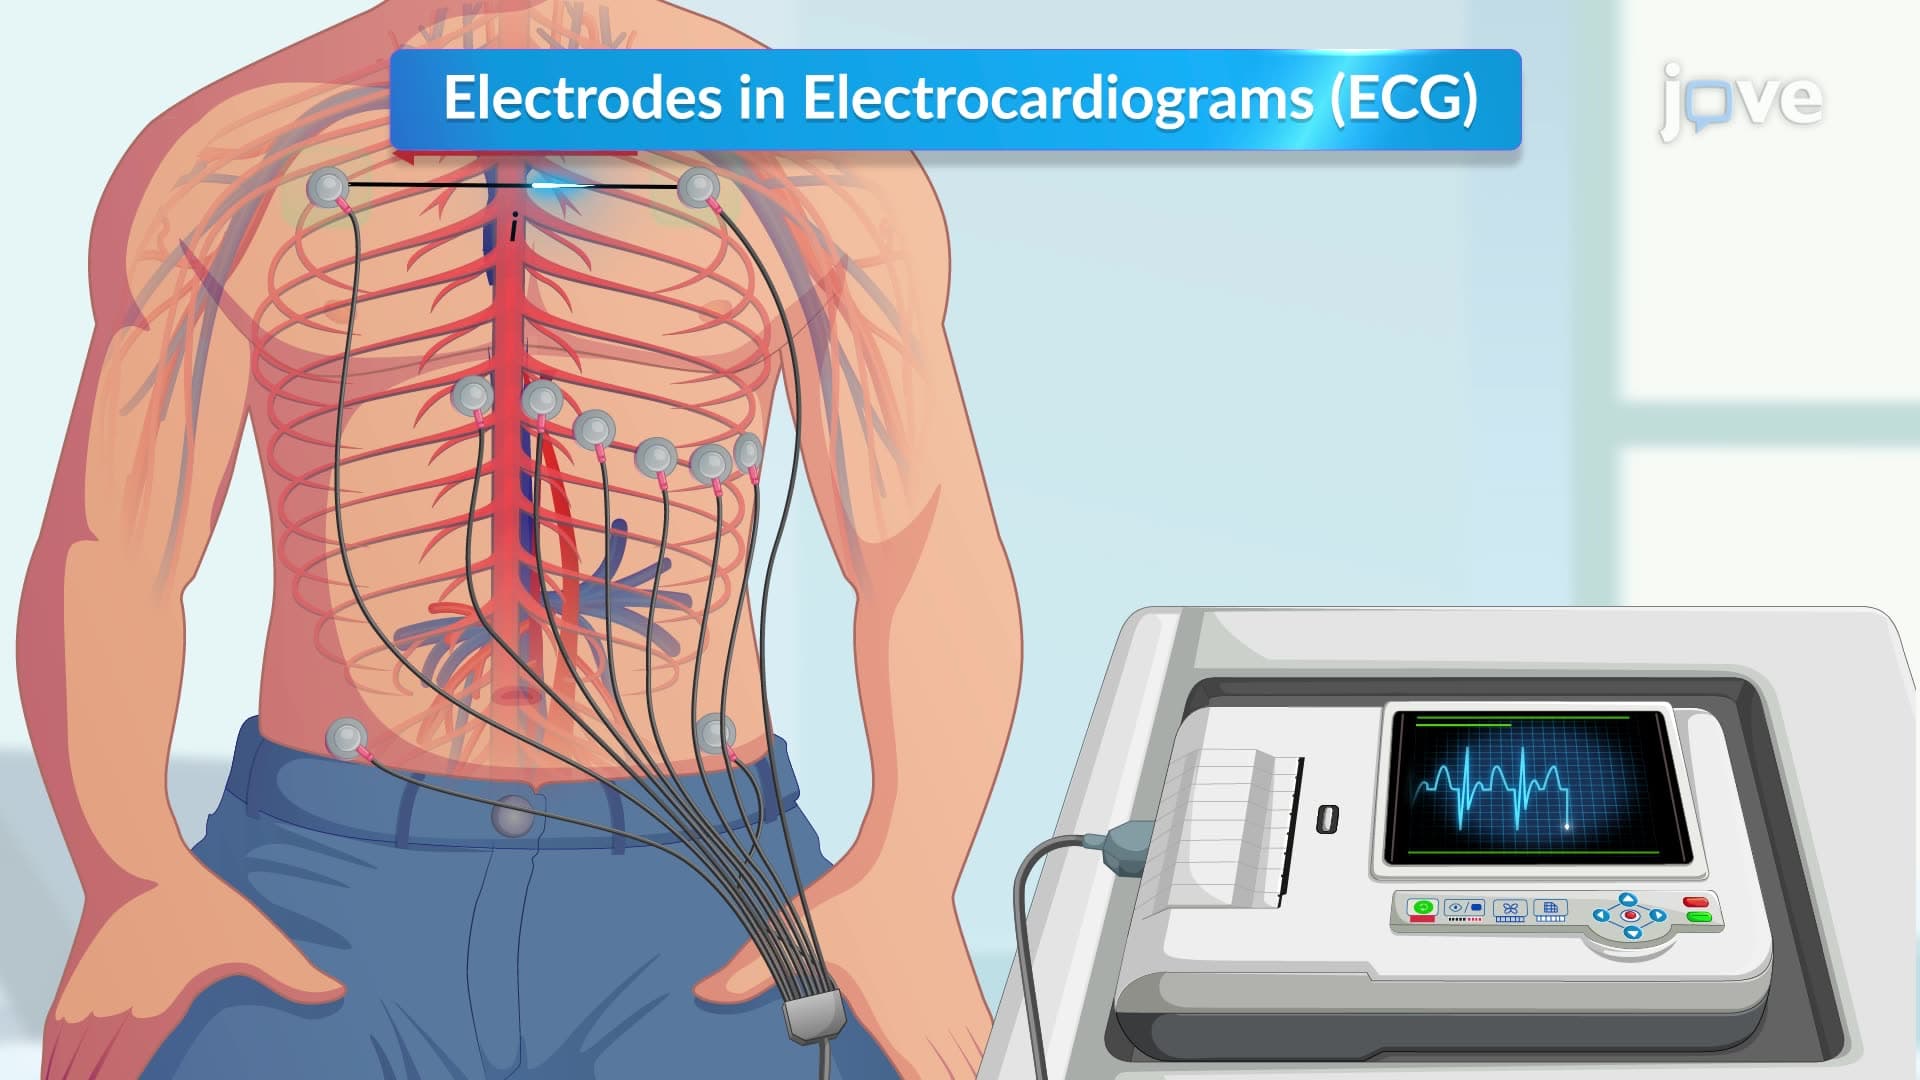
An ECG utilizes electrodes on the skin to...
 01:30
Cardiac Action Potential
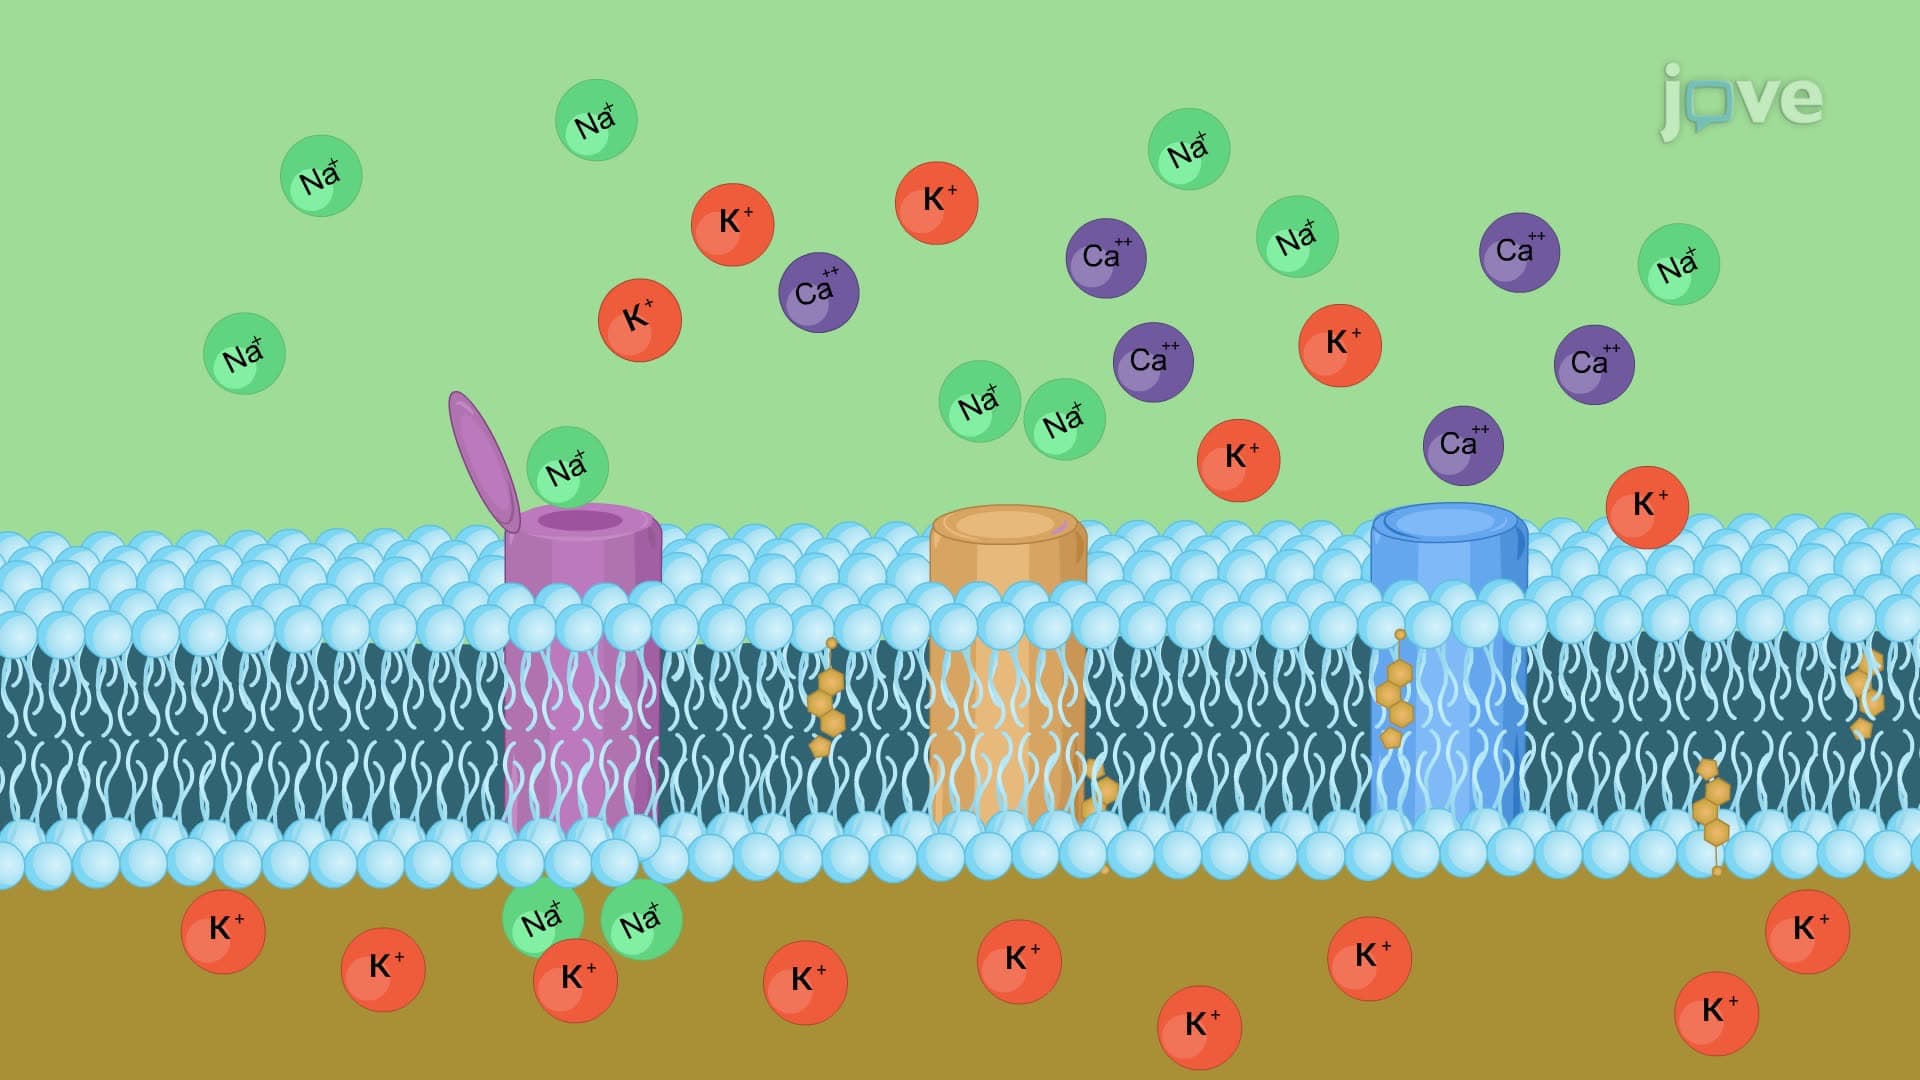
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:24
ECG Interpretation of Rhythms
Components of the Electrocardiogram
The primary components of a normal ECG waveform in Normal sinus rhythm(NSR) include the P wave, PR interval, QRS complex, ST segment, T wave, and occasionally a U wave.
ECG waveforms are divided by vertical and horizontal lines at standard intervals.
The horizontal axis measures time and rate, and the vertical axis measures amplitude or voltage. When...
 01:24
Bode Plots Construction
 01:30
Dysrhythmias V: Evaluating Dysrhythmias