Related Experiment Video
Updated: Jun 11, 2026
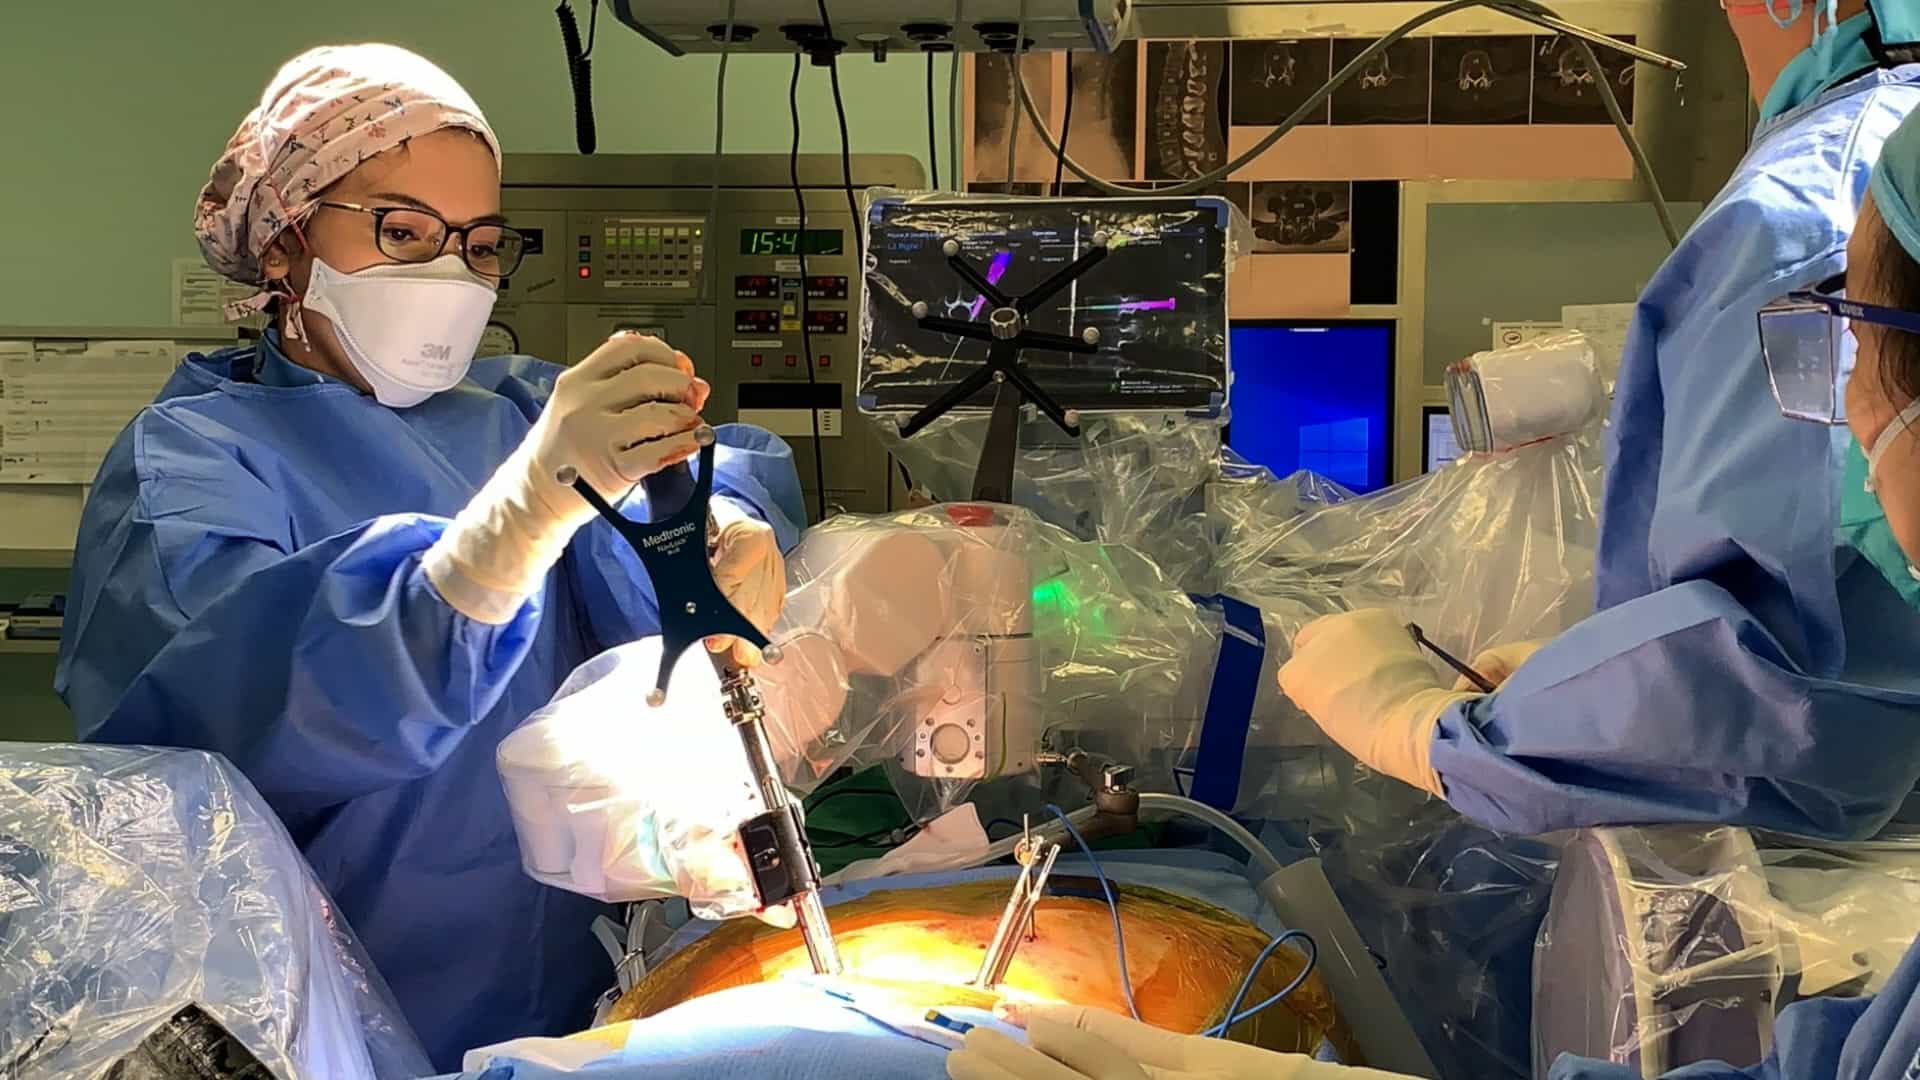

Multilevel Oblique Lumbar Interbody Fusion in Degenerative Lumbar Disc Disease with Instability
Published on: July 25, 2025
Predicting cage subsidence after lumbar interbody fusion: a meta-analysis of opportunistic bone quality metrics
Shaan Patel1, Shiva A Nischal2, Gargee Sree Nallankuka3
1Department of Neurological Surgery, Thomas Jefferson University Hospital, Philadelphia, PA, USA.

Background Context:
Cage subsidence (CS) is a frequent complication following lumbar interbody fusion and is closely linked to vertebral and endplate bone quality. Although CT- and MRI-derived bone metrics are increasingly used for preoperative risk stratification, their comparative discriminative performance for CS has not been systematically evaluated.
Purpose:
To evaluate and compare the discriminative performance of CT- and MRI-derived bone quality metrics for CS following degenerative lumbar fusion.
Study Design/Setting:
Systematic review and meta-analysis.
Methods:
PubMed, Embase, and CENTRAL were searched from inception to January 2026. Observational studies reporting preoperative imaging-based bone quality metrics in adult patients undergoing lumbar interbody fusion were included. Primary metrics included CT-based Hounsfield units, MRI-based vertebral bone quality (VBQ) and endplate bone quality (EBQ), and CT-derived bone mineral density (CT-BMD). Secondary outcomes included DEXA T-scores. Random-effects meta-analyses synthesized continuous inter-group differences and diagnostic accuracy parameters, summarized using pooled sensitivity, specificity, likelihood ratios, diagnostic odds ratios, and SROC curves. Risk of bias was assessed using QUADAS-2.
Results:
Thirty-six studies encompassing 5482 patients were included, of whom 1679 (30.6%) developed CS. Across all metrics, patients with subsidence demonstrated poorer preoperative bone quality, including lower Hounsfield units (MD -26.9; p<.01), lower CT-BMD (MD: -33.0; p<.01), and lower DEXA T-scores (MD: -0.77; p<.01), alongside higher VBQ (MD: 0.60; p<.01) and EBQ scores (MD: 0.68; p<.01). Diagnostic accuracy was moderate-to-good, with pooled AUCs ranging from 0.77 to 0.85. Differences in discriminative performance between metrics were modest and nonsignificant on meta-regression, with nomogram analyses demonstrating risk-shifting rather than definitive rule-in or rule-out performance.
Conclusions:
Imaging-derived bone quality metrics demonstrate consistent associations and moderate-to-good discrimination for CS after degenerative lumbar fusion, reflecting shared vulnerability at the cage-endplate interface and supporting their use as pragmatic tools for preoperative risk stratification and surgical planning.