Related Experiment Video
Updated: Jun 16, 2026


Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Airway Occlusions to Measure Inspiratory Effort, Respiratory Drive, and Lung Mechanics During Noninvasive Ventilation
Francesco Murgolo1,2,3, Domenico Luca Grieco4,5, Rossana Soloperto1,2
1Department of Precision-Regenerative Medicine and Jonic Area (DiMePRe-J), Section of Anesthesiology and Intensive Care Medicine, University of Bari "Aldo Moro", Bari, Italy.

Rationale:
In intubated patients, occlusion maneuvers allow non-invasive assessment of inspiratory effort, respiratory drive and lung mechanics.
Objectives:
To assess the feasibility of occlusion maneuvers during noninvasive ventilation (NIV).
Methods:
In this multicenter study, 60 hypoxemic patients underwent two randomized 1-hour NIV sessions with oro-nasal and full-face masks after extubation. End-expiratory and end-inspiratory occlusions measured expiratory occlusion pressure (Pocc), 100-ms airway-pressure drop (P0.1), and plateau pressure. Esophageal manometry, calibrated before extubation, provided reference values for inspiratory effort, assessed as esophageal pressure swing (ΔPes), and dynamic transpulmonary driving pressure (ΔPL,dyn = pressure support - ΔPes). Interface-specific conversion factors (K) translating Pocc into predicted ΔPes (K × Pocc) and predicted ΔPL,dyn (pressure support - predicted ΔPes) were derived through 100-interaction cross-validation (20-patient derivation set, 40-patient validation set).
Main Results:
Pocc was measurable in all patients. Mean K was 0.71 with the oro-nasal mask and 0.80 with the full-face mask. Predicted ΔPes agreed with observed ΔPes (oro-nasal bias -0.41 cm H2O, 95% limits of agreement -2.3 to 1.5; full-face 0.09, -2.9 to 3.1), and predicted ΔPL,dyn agreed with observed ΔPL,dyn (oro-nasal bias 0.03, -2.9 to 2.9; full-face -0.04, -4.3 to 4.2). Predicted ΔPes identified observed ΔPes ≤ -10 cm H2O, with areas under the receiver-operating-characteristic curve of 0.98 (oro-nasal) and 0.97 (full-face). Ventilator-derived P0.1 did not precisely quantify respiratory drive, but values >2.7 cm H2O with the oro-nasal mask and >3 cm H2O with the full-face mask identified high drive with specificity >90%. Plateau pressure was unstable in 78% (oro-nasal) and 90% (full-face) of patients. More negative predicted ΔPes, higher predicted ΔPL,dyn, and lower predicted lung compliance (expiratory tidal volume/predicted ΔPL,dyn) were associated with subsequent re-intubation.
Conclusion:
During NIV, Pocc-derived parameters provide non-invasive estimates of inspiratory effort, lung stress and mechanics, whereas ventilator P0.1 and plateau pressure are less reliable.

Related Concept Videos
 01:15
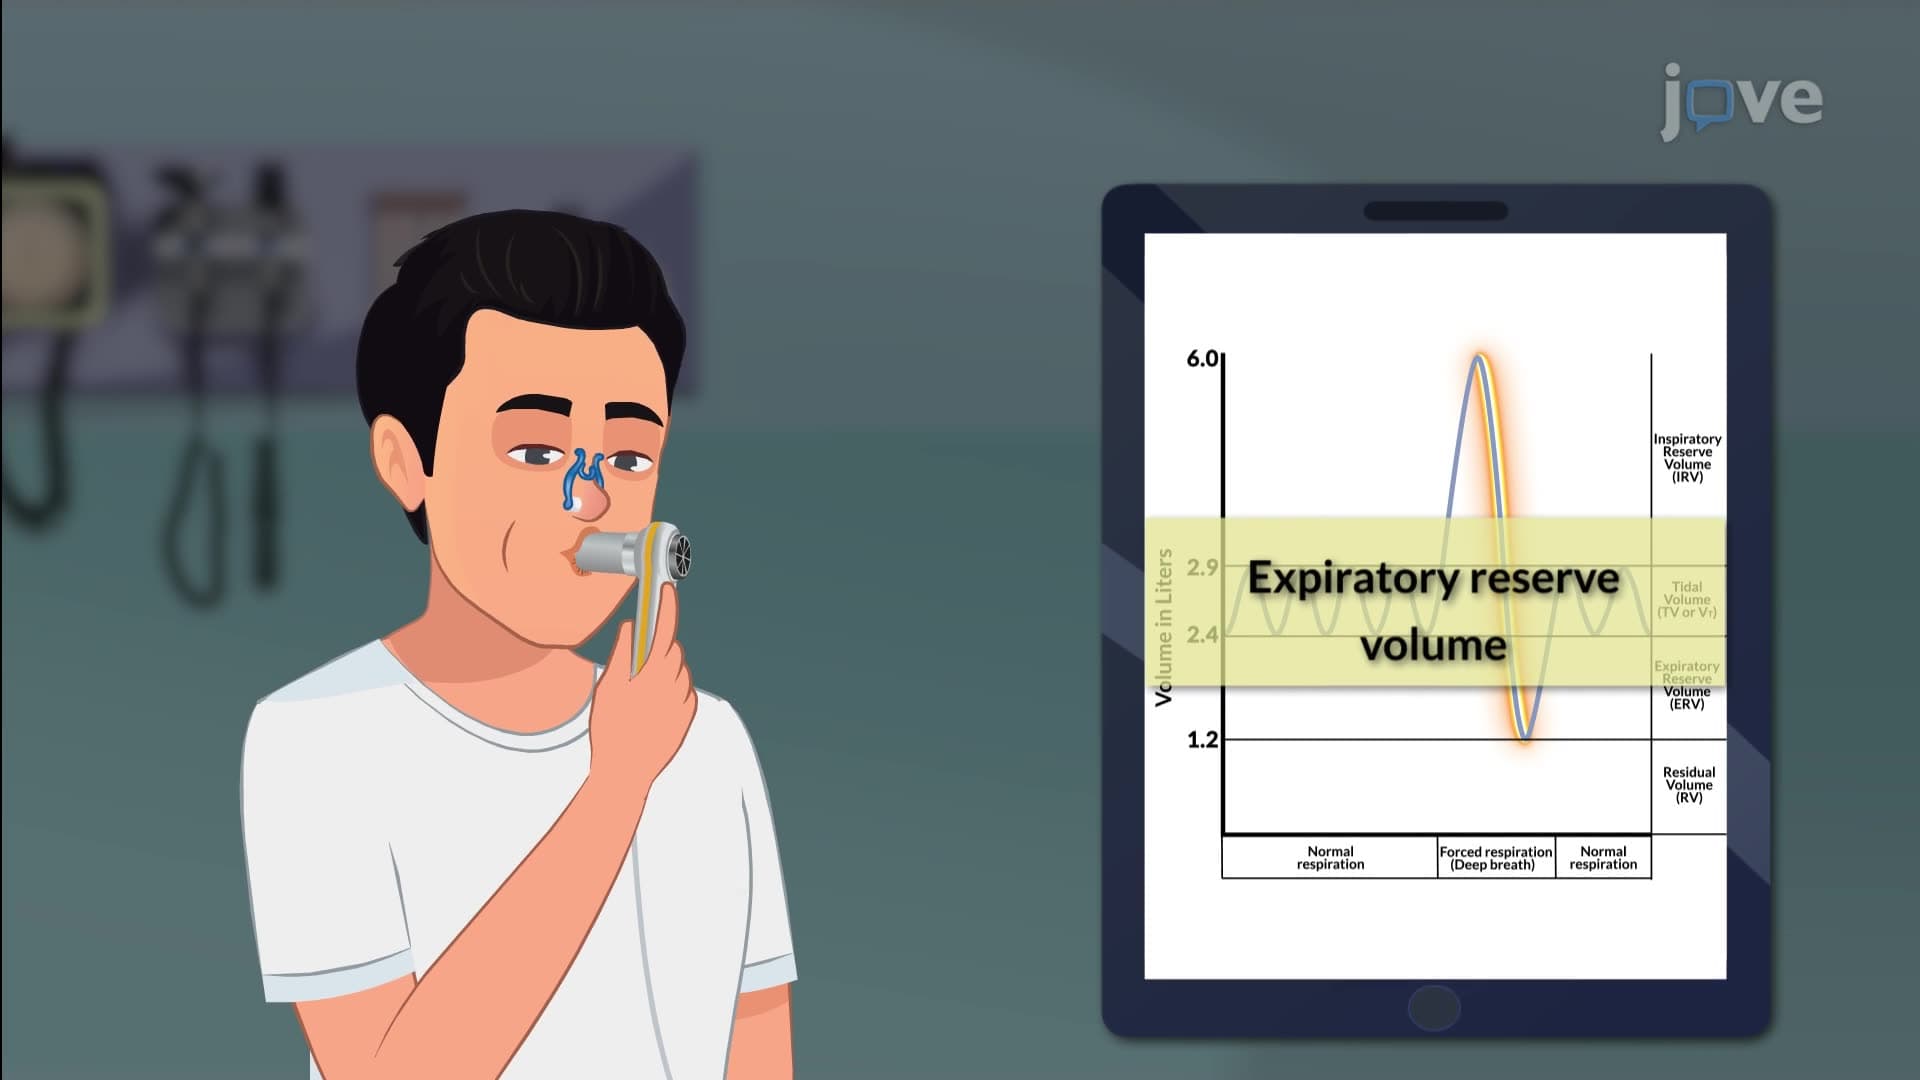
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management