
Central Pancreatectomy with Duct-to-Mucosa Pancreaticogastrostomy Using a Knotless Continuous Suturing Technique:
Mampei Kawashima1, Akira Matsushita2, Akira Hamaguchi2
1Department of Gastrointestinal Surgery, Nippon Medical School Chiba Hokusoh Hospital, Inzai, Chiba, Japan.

Purpose:
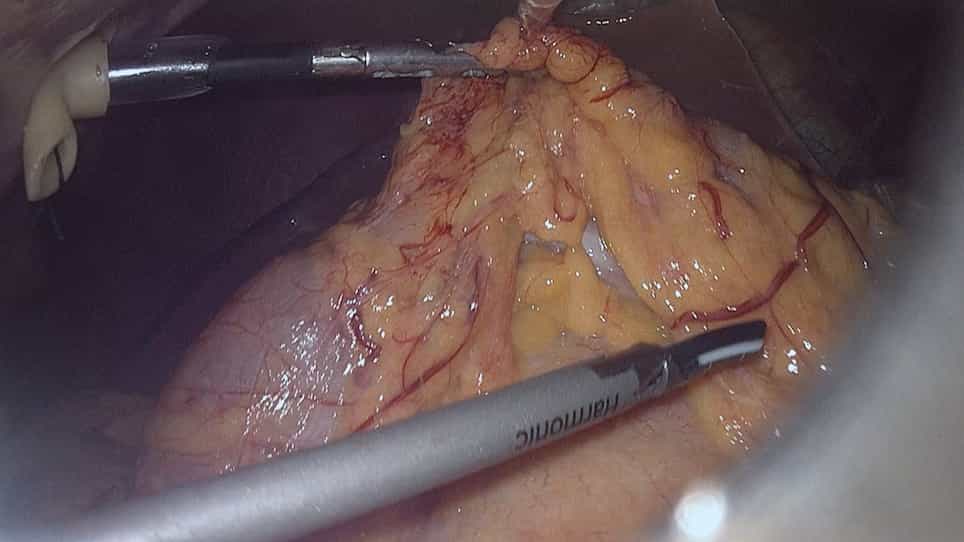
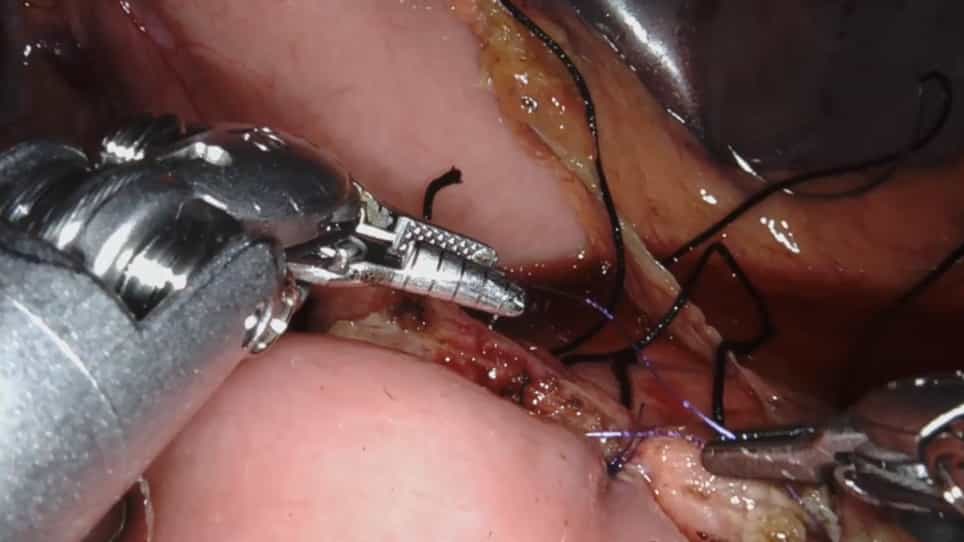
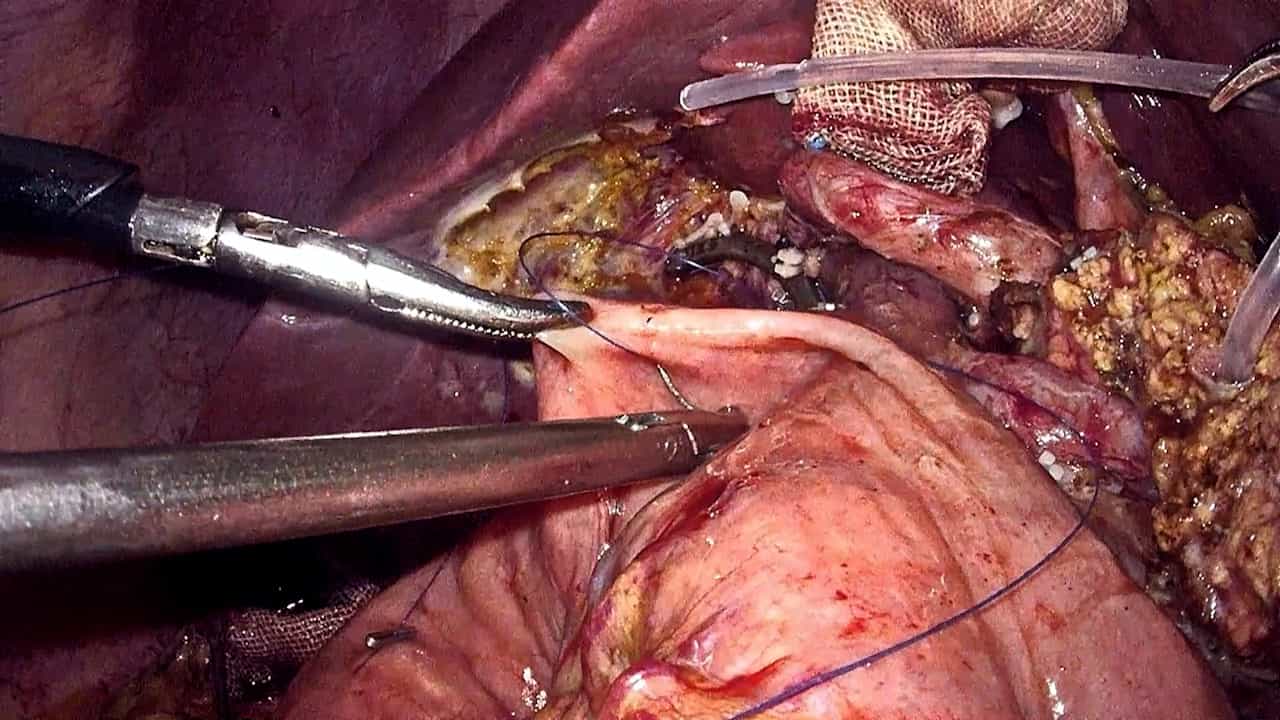
Central pancreatectomy (CP) preserves pancreatic parenchyma but remains technically demanding in minimally invasive surgery because two pancreatic transection surfaces increase the risk of postoperative pancreatic fistula and hemorrhage. This study aimed to evaluate the feasibility of totally laparoscopic central pancreatectomy (LCP) using a standardized risk-oriented surgical design, including a knotless continuous duct-to-mucosa pancreaticogastrostomy technique.
Methods:
This retrospective two-institution study evaluated the feasibility of totally laparoscopic central pancreatectomy (LCP). A standardized risk-oriented surgical design was adopted, consisting of stapler-based pancreatic transection and duct-to-mucosa pancreaticogastrostomy for distal reconstruction. Open CP performed using the same reconstructive concept served as a reference cohort.
Results:
Six patients underwent CP, including three treated with totally laparoscopic CP. All laparoscopic procedures were completed without conversion. One patient developed clinically relevant postoperative pancreatic fistula (ISGPS grade B). No postpancreatectomy hemorrhage, reintervention, or mortality occurred. The median operative time and estimated blood loss in the laparoscopic group were 287 min and 10 mL, respectively.
Conclusions:
Totally laparoscopic central pancreatectomy appeared technically feasible in selected patients when performed within a standardized, risk-oriented surgical framework.