Related Experiment Video
Updated: Jun 16, 2026


Electrocardiogram Recordings in Anesthetized Mice using Lead II
Published on: June 20, 2020
Case Report: Alocasia poisoning presenting with marked QTc prolongation and a MINOCA-like phenotype
Jin-Mei Xie1, Ren-Rong Lu2, Zong-Jie Zheng3
1Department of Electrocardiogram Diagnosis, Sanming First Hospital Affiliated to Fujian Medical University, Sanming, China.

Abstract:
A 75-year-old woman accidentally ingested approximately 10 g of the rhizome of Alocasia macrorrhizos. Within seconds, she developed oral numbness, throat swelling, sialorrhea, dysphagia, and heartburn. She immediately rinsed her mouth with copious amounts of water and presented to a local clinic. An electrocardiogram (ECG) obtained there was normal, with a corrected QT interval (QTc) of 400 ms. Following treatment with anti-allergic therapy, her symptoms resolved. Approximately 26 h after ingestion, she developed persistent, progressive substernal chest pressure. Upon presentation to our hospital (28 h post-ingestion), her cardiac troponin I (cTnI) level was 0.352 ng/mL, while myocardial enzymes and D-dimer were within normal limits. The ECG revealed diffuse T-wave inversions and a markedly prolonged QTc interval of 590 ms. Coronary angiography showed no obstructive lesions and normal coronary flow. Echocardiography demonstrated reduced wall motion in the mid-segment of the left ventricular anterior wall, consistent with a MINOCA-like phenotype. A final diagnosis of toxic myocardial injury was made. Following supportive care, including continuous ECG monitoring, myocardial metabolic support, and rate control with low-dose metoprolol, her chest pain completely resolved approximately 124 h after ingestion. The QTc interval normalized to 440 ms, T-wave inversions became less pronounced, and regional wall motion abnormalities resolved. At a 2-week follow-up, the QTc interval was 420 ms, with further improvement in T-wave inversions.
Conclusion:
This case demonstrates that Alocasia poisoning can cause marked QTc prolongation, diffuse T-wave inversions, and reversible segmental wall motion abnormalities, presenting with a MINOCA-like phenotype. Notably, the patient exhibited significant QTc prolongation despite only mildly elevated cardiac biomarkers, suggesting that the predominant mechanism of toxic myocardial injury in this context may be electrophysiological derangement rather than structural myocyte necrosis. In patients presenting with chest pain accompanied by pronounced QTc prolongation, only mildly elevated cardiac biomarkers, and normal coronary angiography, a detailed exposure history, including inquiry about plants, should be routinely obtained, and continuous ECG monitoring is warranted.
More Related Videos
 07:15
Determining the Likelihood of Variant Pathogenicity Using Amino Acid-level Signal-to-Noise Analysis of Genetic Variation
Published on: January 16, 2019
 10:01
High-Throughput Optical Controlling and Recording Calcium Signal in iPSC-Derived Cardiomyocytes for Toxicity Testing and Phenotypic Drug Screening
Published on: March 31, 2022
Related Concept Videos
 01:26
Anticholinesterase Agents: Poisoning and Treatment
Irreversible agents form a strong bond with the cholinesterase enzyme, making it inactive. The breakdown of the phosphorylated enzyme is slower than the...
 01:16
Drug toxicity: Idiosyncratic Reactions
 01:24
Drug Toxicity: Risk factors
 01:30
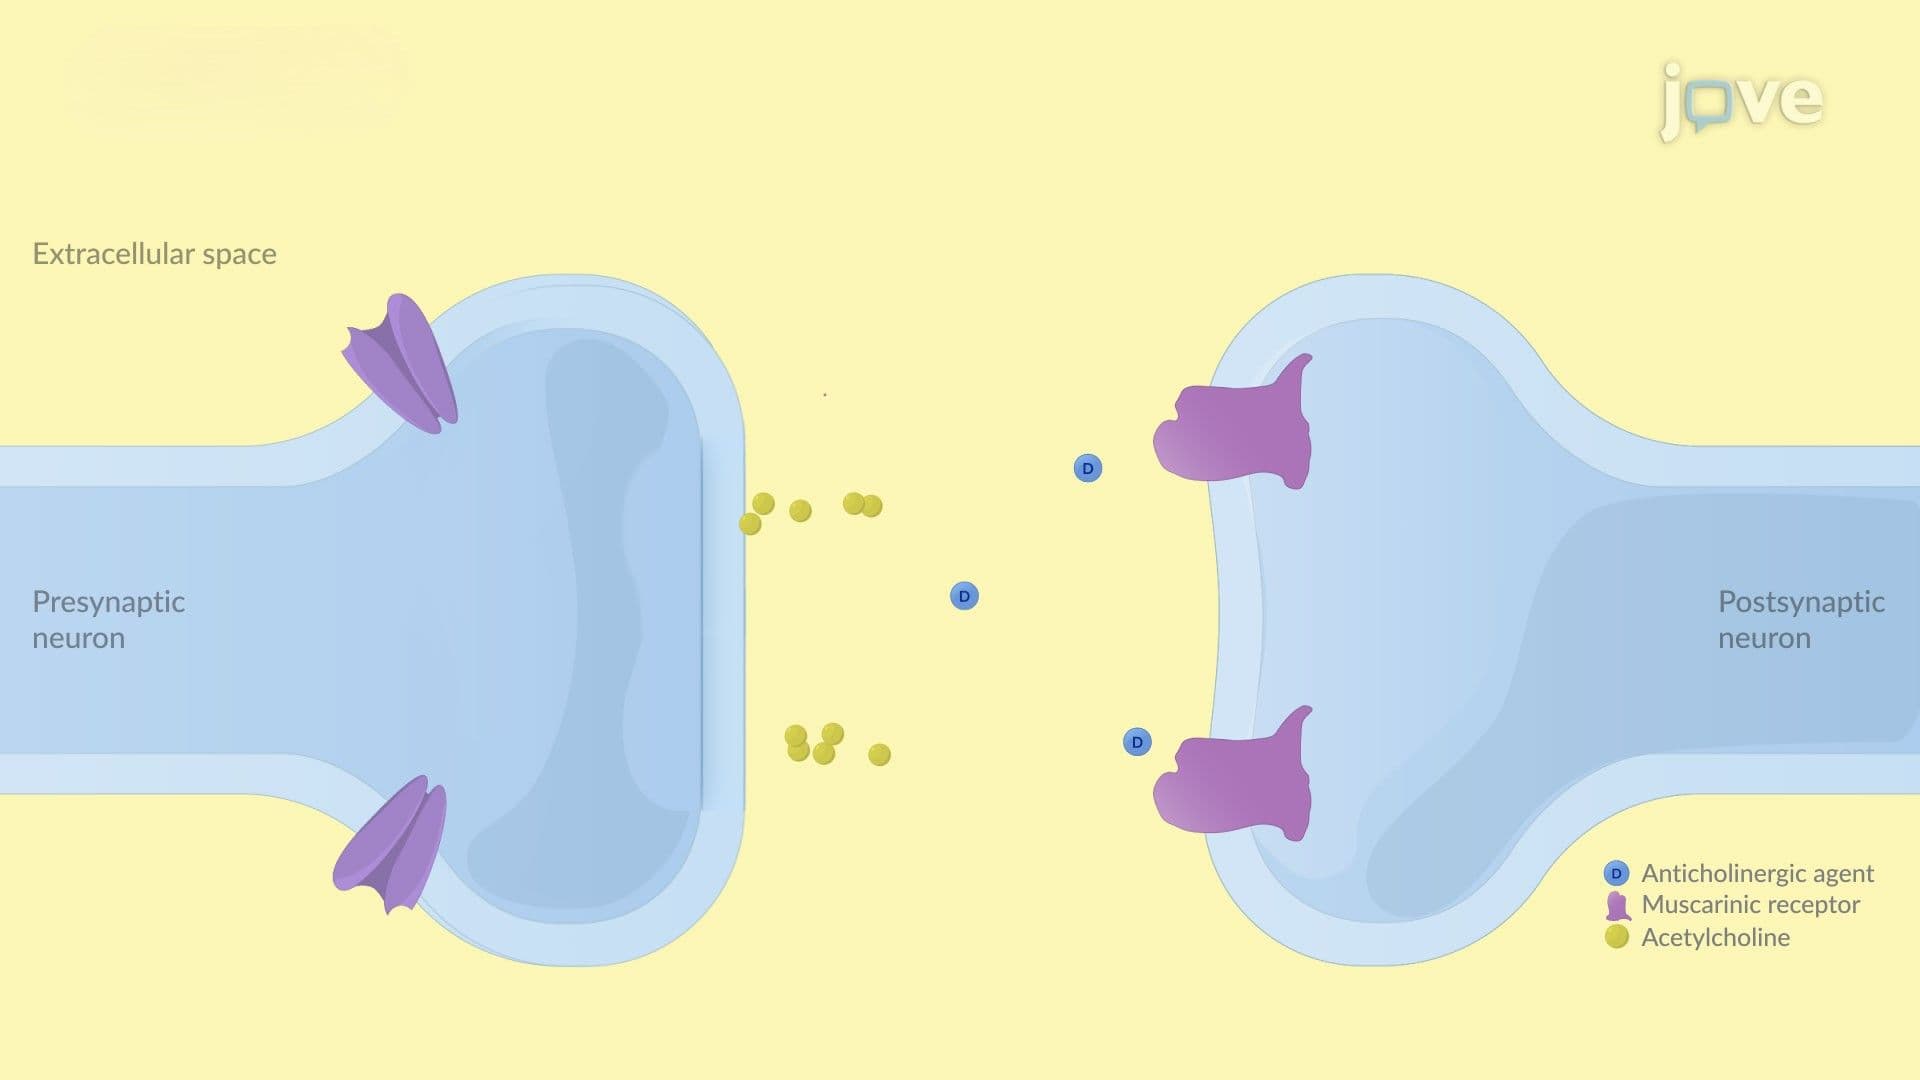
Toxidromes: Clinical Features
 01:00
Drug Toxicity: Overview
 01:26
Pharmaceutical Poisoning: Potential Scenarios