Related Experiment Video
Updated: Jun 17, 2026
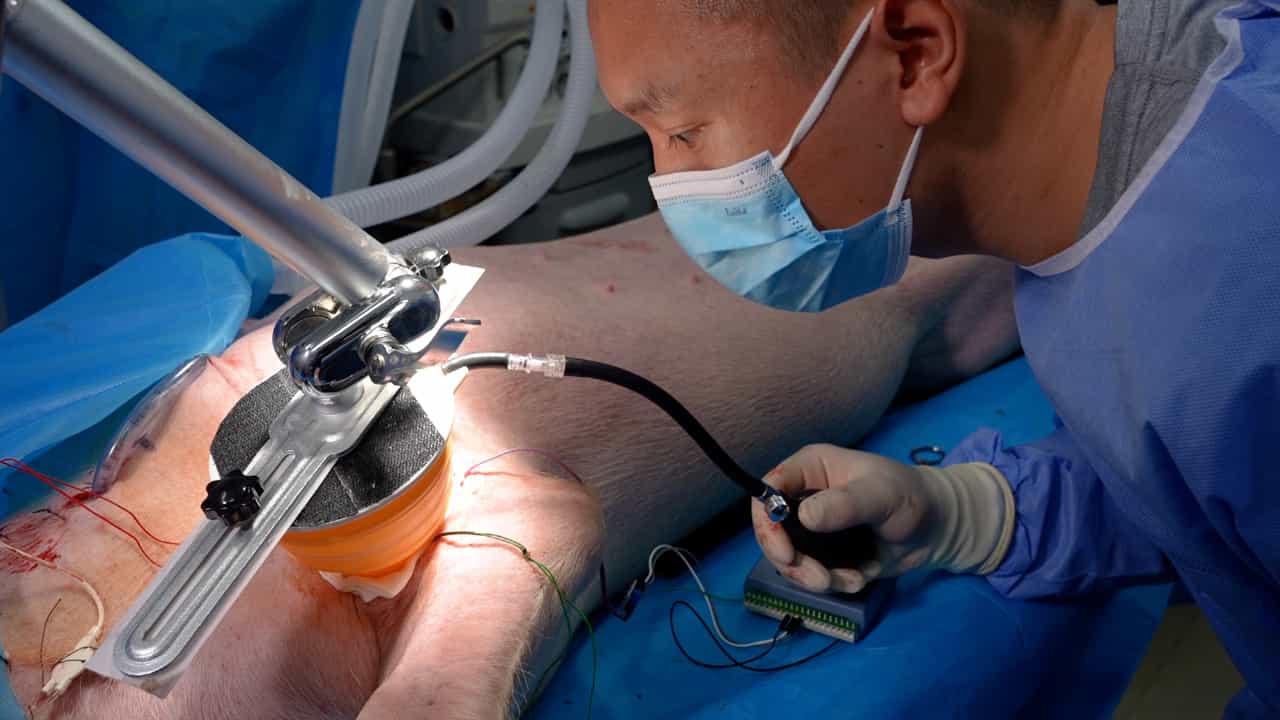

A New Hybrid Quantitative Evaluation Model for Axillary Junctional Hemorrhage in Swine
Published on: December 6, 2024
New approaches in the haemostatic management of postpartum haemorrhage
Catrin Cox1, Lucy Neave1, Beverley J Hunt1
1Thrombosis and Haemophilia, Guy's and St Thomas' Hospitals NHS Trust, London, UK.

Postpartum haemorrhage is the leading cause of maternal mortality worldwide, accounting for a substantial proportion of preventable deaths, particularly in settings with limited resources. Despite its clinical significance, understanding the haemostatic changes underpinning postpartum haemorrhage has historically been limited, with management strategies largely extrapolated from trauma related bleeding. Important physiological differences exist between these conditions, however, which has implications for diagnosis and treatment. Normal pregnancy is characterised by increased coagulation factors and reduced fibrinolysis, resulting in a hypercoagulable state. These adaptations are protective but influence the haemostatic response to bleeding. Recent evidence has refined our understanding of coagulopathy in postpartum haemorrhage. In most cases, haemostasis is preserved despite major blood loss, but fibrinogen depletion is an early and important predictor of severe haemorrhage. A distinct and rare entity, acute obstetric coagulopathy, has been described, characterised by hyperfibrinolysis, hypofibrinogenaemia, dysfibrinogenaemia, and depletion of selective coagulation factors, and is associated with poor maternal and neonatal outcomes. Traditional laboratory coagulation tests are limited by turnaround time and insensitivity to key abnormalities, such as fibrinolysis. Viscoelastic haemostatic assays (eg, thromboelastography (TEG) and rotational thromboelastometry (ROTEM)) offer rapid, point-of-care assessment of clot formation and stability, allowing earlier identification of coagulopathy and more targeted transfusion strategies. Evidence suggests that their use may reduce unnecessary administration of blood products without compromising outcomes. Management strategies are evolving. Tranexamic acid has shown a clear benefit in terms of mortality when given early, and is now widely recommended. In contrast, routine empiric use of fresh frozen plasma is increasingly questioned, given the relative preservation of coagulation factors in most patients with postpartum haemorrhage and the potential risks of over-transfusion. Instead, targeted correction of coagulopathy, especially hypofibrinogenaemia, and judicious use of blood components is gaining interest, guided by clinical and laboratory findings. In summary, advances in the understanding of haemostatic changes in postpartum haemorrhage support a shift towards individualised targeted transfusion strategies. Wider adoption of point-of-care testing and further high quality research are needed to optimise transfusion approaches and improve maternal outcomes globally.
Postpartum haemorrhage is the leading cause of maternal mortality worldwide, accounting for a substantial proportion of preventable deaths, particularly in settings with limited resources. Despite its clinical significance, understanding the haemostatic changes underpinning postpartum haemorrhage has historically been limited, with management strategies largely extrapolated from trauma related bleeding. Important physiological differences exist between these conditions, however, which has implications for diagnosis and treatment. Normal pregnancy is characterised by increased coagulation factors and reduced fibrinolysis, resulting in a hypercoagulable state. These adaptations are protective but influence the haemostatic response to bleeding. Recent evidence has refined our understanding of coagulopathy in postpartum haemorrhage. In most cases, haemostasis is preserved despite major blood loss, but fibrinogen depletion is an early and important predictor of severe haemorrhage. A distinct and rare entity, acute obstetric coagulopathy, has been described, characterised by hyperfibrinolysis, hypofibrinogenaemia, dysfibrinogenaemia, and depletion of selective coagulation factors, and is associated with poor maternal and neonatal outcomes. Traditional laboratory coagulation tests are limited by turnaround time and insensitivity to key abnormalities, such as fibrinolysis. Viscoelastic haemostatic assays (eg, thromboelastography (TEG) and rotational thromboelastometry (ROTEM)) offer rapid, point-of-care assessment of clot formation and stability, allowing earlier identification of coagulopathy and more targeted transfusion strategies. Evidence suggests that their use may reduce unnecessary administration of blood products without compromising outcomes. Management strategies are evolving. Tranexamic acid has shown a clear benefit in terms of mortality when given early, and is now widely recommended. In contrast, routine empiric use of fresh frozen plasma is increasingly questioned, given the relative preservation of coagulation factors in most patients with postpartum haemorrhage and the potential risks of over-transfusion. Instead, targeted correction of coagulopathy, especially hypofibrinogenaemia, and judicious use of blood components is gaining interest, guided by clinical and laboratory findings. In summary, advances in the understanding of haemostatic changes in postpartum haemorrhage support a shift towards individualised targeted transfusion strategies. Wider adoption of point-of-care testing and further high quality research are needed to optimise transfusion approaches and improve maternal outcomes globally.

Related Concept Videos
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:05
Introduction to Hemostasis
The three phases of hemostasis involve many clotting factors present in plasma and several substances released by platelets and injured tissue cells. It is a fast, localized, and...
 01:29
Venous Thrombosis III: Interprofessional Care
 01:30
Venous Thrombosis IV: Nursing Management
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...