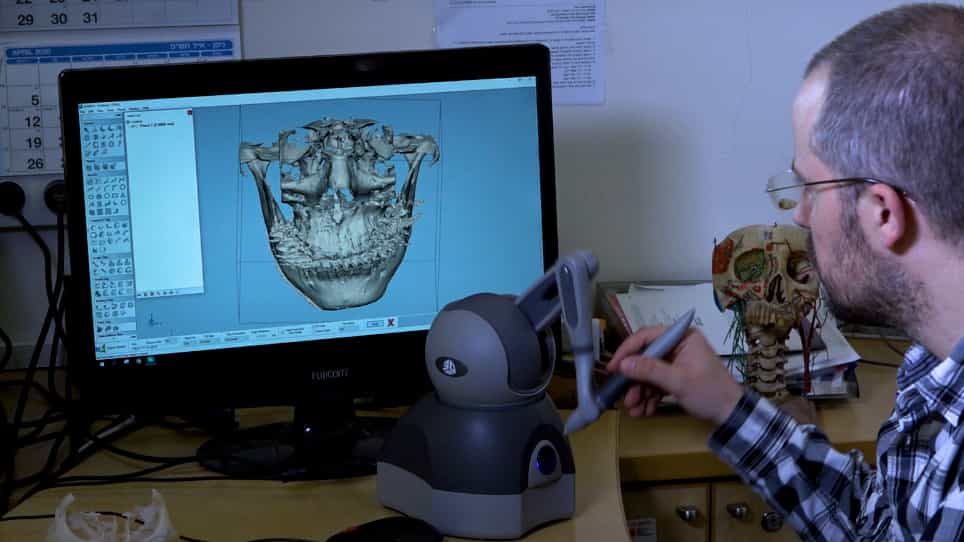
Related Experiment Video
Updated: Jun 19, 2026


A Postoperative Evaluation Guideline for Computer-Assisted Reconstruction of the Mandible
Published on: January 28, 2020
Digital Workflow Integration in Acute Panfacial Fracture Management
Michael V Joachim1, Michael Miloro2
1Attending Surgeon, Unit of Oral and Maxillofacial Surgery and Department of Plastic Surgery, Shamir (Assaf ha-Rofeh) Medical Center, affiliated to the Gray Faculty of Medical and Health Sciences, Tel Aviv University, Tzrifin, Israel.

Background:
Panfacial fractures are among the most technically demanding injuries in craniomaxillofacial trauma surgery. Digital workflows - including virtual surgical planning (VSP), three-dimensional printing, and intraoperative navigation - have demonstrated benefit in elective and delayed surgical settings, yet their integration into acute panfacial fracture management remains poorly characterized.
Purpose:
This systematic review evaluated the evidence for digital workflow integration in acute primary panfacial fracture management, characterizing achievable outcomes, assessing implementation feasibility, and identifying research priorities.
Study Selection:
PubMed, Embase, Cochrane Library, and Web of Science were searched from inception through March 2026. Studies reporting clinical outcomes of digital workflow integration in acute panfacial or complex multiregion facial fracture management in adults were eligible. Case reports and technical notes without clinical outcomes were excluded. Of 840 records identified, 5 studies met inclusion criteria.
Data Extraction And Synthesis:
Data were extracted using a standardized form. Methodological quality was assessed with the Newcastle-Ottawa Scale and the Institute of Health Economics quality appraisal tool. Evidence quality was rated using the Grading of Recommendations, Assessment, Development and Evaluation framework. Substantial heterogeneity precluded meta-analysis; findings are presented as a narrative synthesis.
Results:
Five studies comprising 82 subjects across 5 countries were included, spanning adjunctive modalities from intraoperative navigation alone to fully integrated in-house VSP with three-dimensional printing and thermoformed cage splints (TCS). Grading of Recommendations, Assessment, Development and Evaluation quality was moderate for operative time in one study, low for fracture reduction accuracy and occlusal outcomes, and very low for the ballistic case series. Intraoperative navigation statistically significantly reduced mean operative time by 124.8 minutes (36.1% reduction; 95% CI, 68.5 to 181.2 minutes, P < .001). Fully integrated VSP with intraoperative navigation achieved fracture reduction accuracy below the 2 mm clinical threshold - assessed as root mean square error referenced to the orthognathic surgery literature - across all facial thirds in the only strictly panfacial cohort (mandible 1.67 ± 0.75 mm; maxilla 0.88 ± 0.52 mm; midface 0.59 ± 0.47 mm; all P < .001). In-house workflows achieved planning intervals from a mean of 4.2 hours to within 24 hours of CT acquisition at approximately $597 USD per case.
Conclusions And Relevance:
Digital workflow integration in acute panfacial fracture management is feasible across the full spectrum of modalities; in-house point-of-care manufacturing overcomes the temporal barrier to acute implementation and supports institutional investment in digital workflow capacity.