Related Experiment Video
Updated: Jun 19, 2026


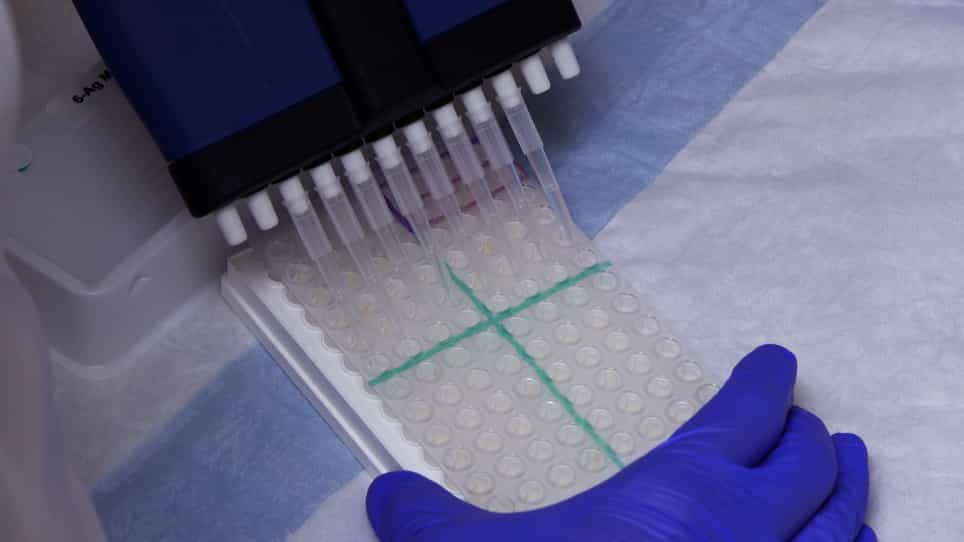
Electrochemiluminescence Assays for Human Islet Autoantibodies
Published on: March 23, 2018
Islet Autoantibody and Beta Cell Secretory Status at Diagnosis in Young Bangladeshi with Phenotypically Type 2
Kishore Kumar Shil1, Mashfiqul Hasan2, Nusrat Sultana2
1Khulna Medical College Hospital, Khulna, Bangladesh.

Background:
The overlapping clinical features in young-onset type 2 diabetes (T2DM) present significant diagnostic difficulties. Variable autoimmunity and beta-cell dysfunction, which are related to the phenomenon, are not sufficiently consolidated to distinguish subclasses.
Objectives:
To determine the frequency of islet autoantibodies and beta-cell secretory status in phenotypically young Bangladeshi with T2DM.
Methodology:
This cross-sectional study enrolled 83 patients with newly diagnosed young-onset phenotypically T2DM, aged 10 to 29 years, comprising 34 males (41%) and 48 females (59%), using non-probability purposive sampling. The demographic and clinical features of the patients were recorded. A fasting blood sample was collected for C-peptide and islet antibodies (anti-glutamic acid decarboxylase [GAD], zinc transporter 8 [ZnT8], and Islet Antigen 2 [IA-2] antibodies). C-peptide, anti-GAD Ab and IA-2 Ab were measured by chemiluminescence, while the ZnT8 Ab was measured by enzymelinked immunosorbent assay (ELISA).
Results:
An adequate beta cell secretory reserve was present in 97.6% of participants (N = 82), with a median C-peptide level of 4.3 ng/mL (IQR: 3.0-6.7). Of the 82 patients included, GAD Ab was found to be positive in 17% (n = 14), ZnT8 Ab in 2.4% (n = 2), and none were positive for IA-2 Ab or a double antibody (ZnT8 Ab + GAD Ab). The frequency of double diabetes (DD) [GAD Ab positive subjects] was 17% (14/82). Comparing the GAD Ab positive to the negative group, the former had a significantly lower homeostasis model assessment of β-cell function (HOMA-B) at 24.7 (16.3-99.1) [versus 81.9 (30-154) in the latter (p = 0.02)] and a significantly higher fasting plasma glucose (FPG) median IQR at 16 mmol/L (10-19) [compared to 9.5 (6.7-14.5) (p = 0.04) in the negative group.] The body mass index (BMI) was the only significant predictor of C-peptide (β = 0.44, p <0.001).
Conclusion:
GAD Ab was the most commonly detectable antibody in this study of young-onset phenotypically T2DM patients. The concentration of GAD Ab may influence the phenotypic presentation, but it is not a predictor of C-peptide levels. Beta-cell dysfunction in this subset of patients may depend on certain yet unexplored factors.

Related Concept Videos
 01:12
Type I Diabetes I: Introduction
 01:26
Type I Diabetes II: Pathophysiology
 01:22
Diabetes Mellitus: Overview and Type I Subtype
Type 1 diabetes is an autoimmune disease in which the immune system mistakenly attacks and destroys the insulin-producing beta cells in the pancreas. As a result, the body is unable to produce sufficient insulin, and individuals with...
 01:26
Type II Diabetes I: Introduction
 01:22
Diabetes Mellitus: Type 2 and Gestational
 01:24
Type II Diabetes II: Pathophysiology