Clinical outcomes and costs associated with viral lower respiratory tract disease hospitalisations
Related Experiment Video
Updated: Jun 20, 2026
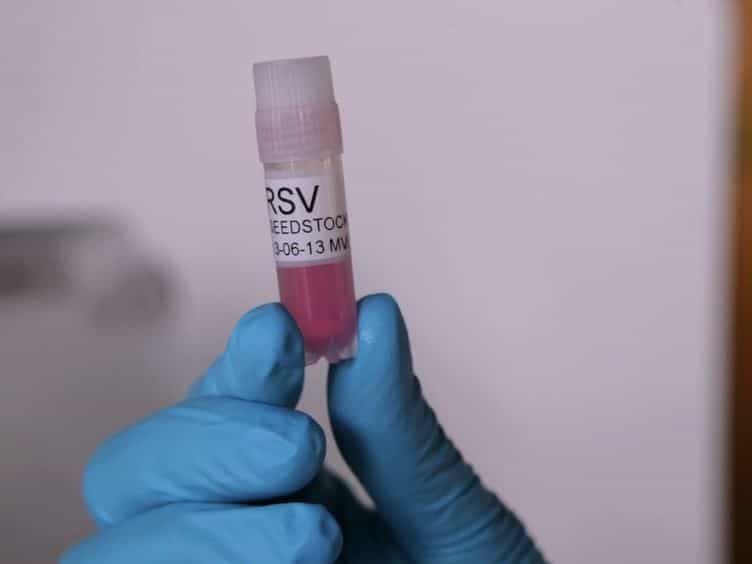
An In vitro Model to Study Immune Responses of Human Peripheral Blood Mononuclear Cells to Human Respiratory Syncytial Virus Infection
Published on: December 10, 2013
Ekaterina Maslova1, Malin Fagerås2, Trung Tran3
1BioPharmaceuticals Medical, AstraZeneca UK Limited, Cambridge, UK.

Background:
An updated comprehensive assessment of the burden of hospitalised viral lower respiratory tract disease (LRTD) is especially salient after the COVID-19 pandemic. Therefore, we aimed to comprehensively describe clinical characteristics and outcomes of US adults hospitalised with viral LRTD between 2015 and 2023.
Methods:
In this retrospective analysis, adults hospitalised between 1 January 2015 and 31 March 2023 were identified using Optum's deidentified Clinformatics Data Mart Database. Index date was the first International Classification of Diseases, 9th/10th Revision (ICD-9/10) code for viral LRTD hospitalisation. Outcomes included intensive care unit (ICU) admission, non-invasive ventilation (NIV), invasive mechanical ventilation/extracorporeal membrane oxygenation (IMV/ECMO), costs, 30-day mortality and 30-day readmissions. Outcomes were stratified by viral aetiology (ICD-9/10), clinical severity and time period (2015-2019; 2020-2021; 2022-2023). Time-to-event data were assessed using Kaplan-Meier estimates.
Results:
Of 387 449 patients hospitalised for viral LRTD, 38.1% were admitted to ICU within 30 days of index (84.6% of these were admitted on index date); 8.4% and 8.7%, respectively, received NIV and IMV/ECMO within 30 days of index and 30-day mortality was 15.1%. Median (IQR) length of stay and mean (SD) hospitalisation costs were 7 (4-15) days and $42 752 ($44 841), respectively. Admission to ICU, mortality and costs were substantial across all aetiologies but peaked from 2020 to 2021; readmissions and costs remained high even into 2022-2023.
Conclusions:
Severe viral LRTD incurred substantial burden for US healthcare systems across all viral aetiologies, even in non-pandemic years, with frequent ICU admission and ventilation use, and with considerable associated costs. Readmission rates and costs remain high even after the peak of COVID-19.
Related Concept Videos
 01:29
Respiratory Syncytial Virus Disease
 01:30
Pneumonia III: Complications and Assessment
 01:28
Pneumonia IV: Management
Bacterial Pneumonia Treatment
For bacterial pneumonia, antibiotics serve as the cornerstone of therapy. Initial treatment often begins with empirical antibiotics, tailored to the anticipated causative organism and adjusted based on culture results. Key antibiotic choices include:
 01:27
Influenza
 01:29
Pneumonia I: Introduction
 01:30
Pneumonia I: Introduction
Risk Factors
Various factors influence the likelihood of developing pneumonia. Age plays a crucial role, with infants, children under two, and individuals over 65 at increased risk due to their...