Related Experiment Video
Updated: Jun 23, 2026
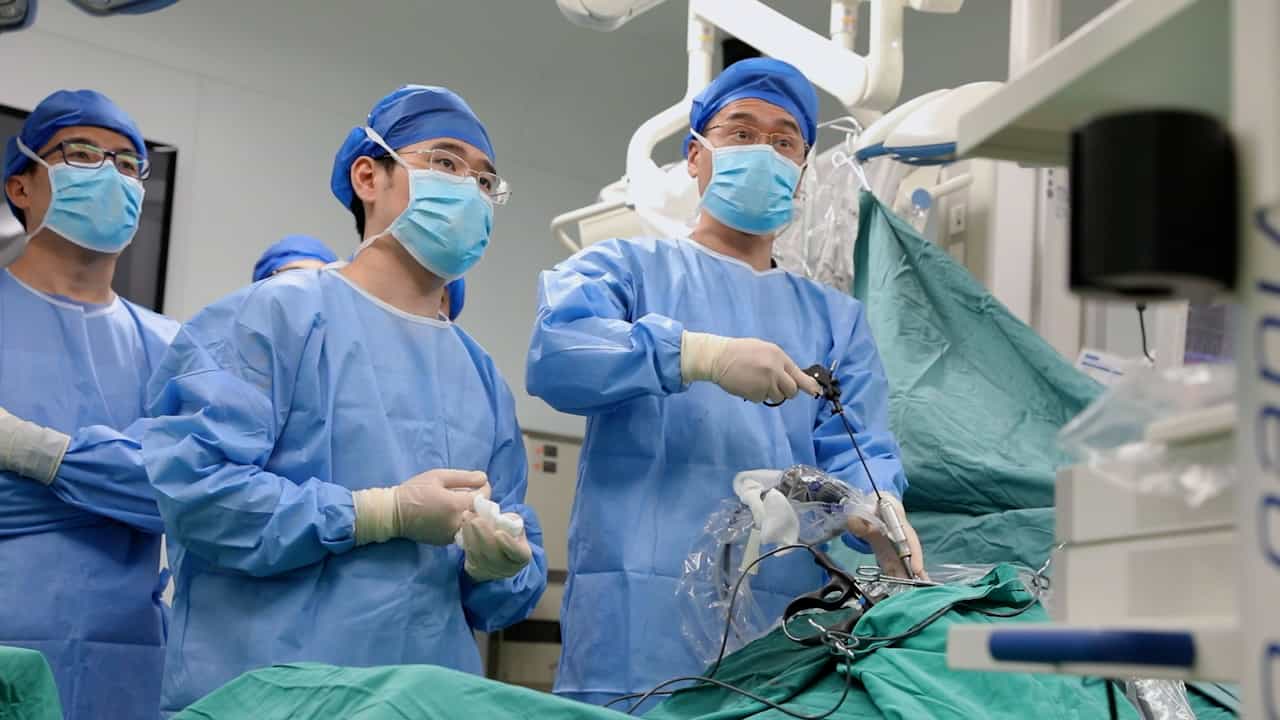

Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Preoperative Distal Motor Latency Testing and Long-Term Outcomes in Combined Lumbar Spinal Stenosis: A Retrospective
Shizumasa Murata1, Hiroshi Iwasaki1, Kimihide Murakami2
1Department of Orthopedic Surgery, Wakayama Medical University.

Study Design:
Retrospective cohort study.
Objective:
To determine whether a function-guided selective decompression strategy based on preoperative distal motor latency (DML) testing can avoid unnecessary L5/S decompression without compromising outcomes in patients with combined L4/5 central and L5/S foraminal-extraforaminal lumbar spinal stenosis (LSS) and to identify predictors of poor outcomes and reoperation.
Summary Of Background Data:
In multilevel LSS, radiographic evidence of stenosis at L4/5 and L5/S is common, yet anatomic narrowing does not always reflect functional neural compromise. Although DML testing has been introduced to detect L5/S foraminal-extraforaminal involvement, its value in guiding selective decompression and outcomes in cases of structural-functional discordance remains unclear.
Methods:
We retrospectively analyzed 290 consecutive patients with radiographic evidence of L4/5 central stenosis and concomitant L5/S foraminal-extraforaminal stenosis who underwent decompression surgery with preoperative DML testing (2010-2019). All patients received L4/5 microendoscopic decompression; additional L5/S decompression was performed only when DML indicated electrophysiological L5 impairment. Patients were stratified into DML-negative (n=110) and DML-positive (n=180) groups. Postoperative Japanese Orthopaedic Association (JOA), Oswestry Disability Index (ODI), Visual Analog Scale (VAS) scores, and reoperation rates were compared. Multivariate logistic regression identified predictors of poor outcomes.
Results:
Adjusted JOA, ODI, and VAS scores did not differ between groups at 1 year or final follow-up. Reoperation rates were comparable. Lower preoperative JOA scores and higher leg pain VAS scores independently predicted poor outcomes, whereas DML status did not. In the DML-negative group, younger age and higher body mass index were associated with reoperation.
Conclusions:
A DML-guided selective decompression strategy was not associated with inferior outcomes compared with combined decompression. These findings support a structure-function framework for surgical decision-making in multilevel LSS.
Level Of Evidence:
Level III.
