Related Experiment Video
Updated: Jun 25, 2026


A Mouse Model for Chronic Pancreatitis via Bile Duct TNBS Infusion
Published on: February 28, 2021
A pediatric case of citrin deficiency presenting with recurrent hypertriglyceridemic pancreatitis-a case report
Ruyi Ye1, Puhong Zhang2, Yong Gu1
1Department of Pediatrics, The First Affiliated Hospital of Wannan Medical University (Yijishan Hospital of Wannan Medical University), Wuhu, China.

Insights
Citrin deficiency (CD) can cause severe hypertriglyceridemia and recurrent pancreatitis in children. Early diagnosis and dietary management are crucial, even without hyperammonemia.
Area of Science:
- Biochemistry
- Genetics
- Pediatrics
Background:
- Citrin deficiency (CD) is a rare metabolic disorder caused by pathogenic variants in the SLC25A13 gene.
- It affects the aspartate-glutamate carrier, impacting metabolic pathways.
- CD can manifest in different stages, including failure to thrive and dyslipidemia (FTTDCD) in the post-neonatal cholestasis (NICCD) phase.
Abstract:
Citrin deficiency (CD) is a rare autosomal recessive metabolic disorder caused by pathogenic variants in the SLC25A13 gene, which encodes the mitochondrial aspartate-glutamate carrier 2, also known as citrin. We describe an 11-year-old Chinese boy presenting with recurrent acute pancreatitis secondary to severe hypertriglyceridemia during the FTTDCD/post-NICCD stage of citrin deficiency. The patient was relatively thin (his height and weight were at the 10th percentile on the growth curve for Chinese children), had a strong preference for soy products and an aversion to carbohydrates. Laboratory tests at presentation revealed severe hypertriglyceridemia (28.96 mmol/L), with a previously documented peak of 30.35 mmol/L. Abdominal computed tomography showed diffuse pancreatic enlargement and peripancreatic inflammatory changes, which, together with compatible abdominal pain, supported the diagnosis of acute pancreatitis. Genetic sequencing identified compound heterozygous pathogenic mutations in the SLC25A13 gene (exon 9: c.852_855delTATG; intron 6: c.615+5G > A). Plasma ammonia and citrulline levels were within normal limits. All of these findings supported a diagnosis of failure to thrive and dyslipidemia caused by citrin deficiency (FTTDCD) in the post-NICCD phase. Management involved plasma exchange, a high-protein/high-fat/low-carbohydrate diet, and medium-chain triglyceride (MCT) supplementation, leading to clinical improvement. However, poor dietary adherence during follow-up resulted in two readmissions for recurrent pancreatitis. This case highlights that citrin deficiency should be considered in children with recurrent acute pancreatitis associated with severe hypertriglyceridemia, especially when accompanied by carbohydrate aversion and unusual dietary preferences, even in the absence of hyperammonemia or hypercitrullinemia.

Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
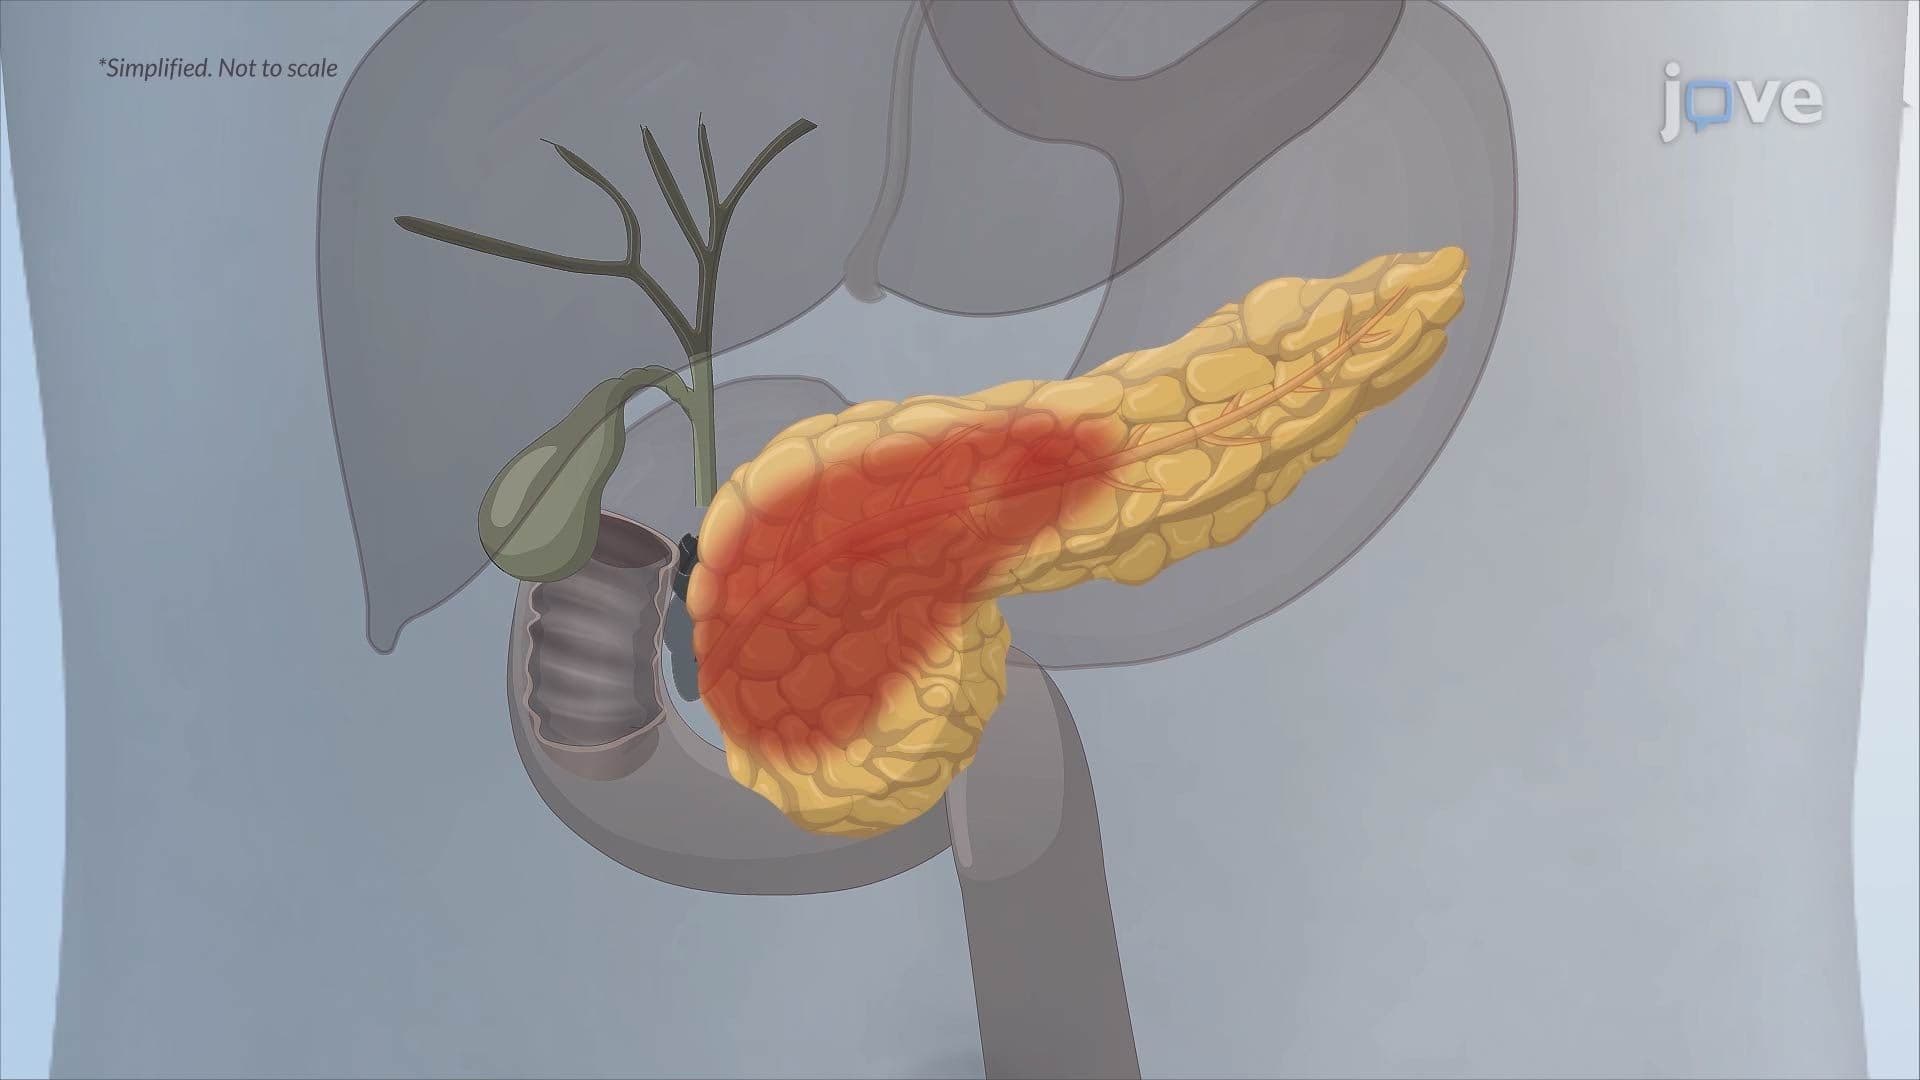
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:21
Chronic Pancreatitis II: Pathophysiology