Related Experiment Video
Updated: Jun 26, 2026


Use of In vivo Imaging to Monitor the Progression of Experimental Mouse Cytomegalovirus Infection in Neonates
Published on: July 6, 2013
Human cytomegalovirus at the maternal-fetal interface: an overview of pathogenesis, defence, and interventions
Mahlaqua Noor1,2, Catherine E Aiken2,3, Emma Poole1
1Department of Pathology, University of Cambridge, Cambridge, UK.

Human cytomegalovirus (HCMV) is the leading infectious cause of congenital disease worldwide and a major contributor to birth defects and neurodevelopmental disorders. Vertical transmission occurs when the virus breaches the maternal-fetal interface, a complex immunological environment where the placenta is in direct contact with either the uterine lining (decidua) or maternal blood covering the syncytium. The present review synthesises current understanding of HCMV pathogenesis at this critical interface, examining viral invasion mechanisms, host immune responses, and immune evasion strategies. We outline the structural and cellular features of the placenta and decidua, highlighting key immune populations such as uterine natural killer cells and their roles in antiviral defence. The present review examines the mechanisms of HCMV dissemination across the placenta alongside placental-specific defences to infection and details on how HCMV subverts both innate and adaptive immunity to establish and maintain infection. Critical gaps in diagnostics, the limited efficacy of current antiviral therapies, and obstacles in vaccine development are reviewed, underscoring the urgent need for prevention strategies. Finally, we assess experimental models, placental explants, primary trophoblast and decidual organoids, and microfluidic placenta-on-chip systems that are advancing insights into cell-type-specific tropism, immune interactions, and mechanisms of transplacental HCMV transmission. Continued research into host-virus interactions at the maternal-fetal interface and improved model systems are critical for developing targeted prevention and treatment strategies to reduce the burden of congenital HCMV infection.
Human cytomegalovirus (HCMV) is the leading infectious cause of congenital disease worldwide and a major contributor to birth defects and neurodevelopmental disorders. Vertical transmission occurs when the virus breaches the maternal-fetal interface, a complex immunological environment where the placenta is in direct contact with either the uterine lining (decidua) or maternal blood covering the syncytium. The present review synthesises current understanding of HCMV pathogenesis at this critical interface, examining viral invasion mechanisms, host immune responses, and immune evasion strategies. We outline the structural and cellular features of the placenta and decidua, highlighting key immune populations such as uterine natural killer cells and their roles in antiviral defence. The present review examines the mechanisms of HCMV dissemination across the placenta alongside placental-specific defences to infection and details on how HCMV subverts both innate and adaptive immunity to establish and maintain infection. Critical gaps in diagnostics, the limited efficacy of current antiviral therapies, and obstacles in vaccine development are reviewed, underscoring the urgent need for prevention strategies. Finally, we assess experimental models, placental explants, primary trophoblast and decidual organoids, and microfluidic placenta-on-chip systems that are advancing insights into cell-type-specific tropism, immune interactions, and mechanisms of transplacental HCMV transmission. Continued research into host-virus interactions at the maternal-fetal interface and improved model systems are critical for developing targeted prevention and treatment strategies to reduce the burden of congenital HCMV infection.
More Related Videos
 05:22
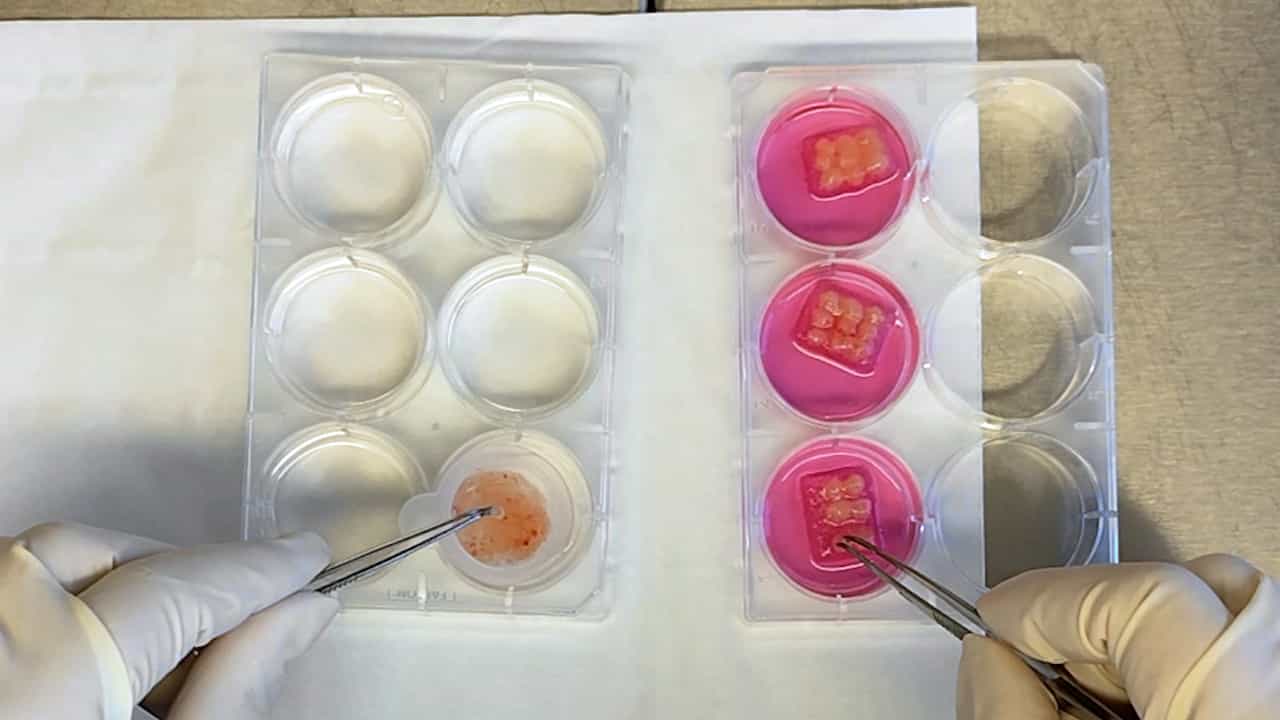
Ex vivo Culture of Human Placental Explants for the Study of Viral Transmission Across the Maternal-Fetal Interface
Published on: December 30, 2025
 05:51
Intracerebroventricular and Intravascular Injection of Viral Particles and Fluorescent Microbeads into the Neonatal Brain
Published on: July 24, 2016
Related Concept Videos
 01:27
Cytomegalovirus Disease
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:29
Respiratory Syncytial Virus Disease
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...
 01:29
Malaria
 01:28
Development of the Oral Microbiota