Related Experiment Video
Updated: Jun 26, 2026
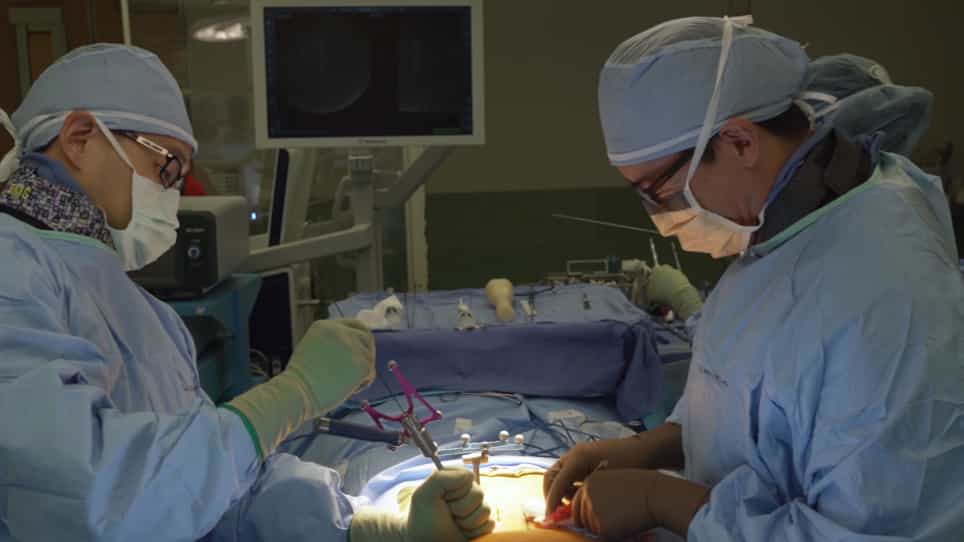

Cone Beam Intraoperative Computed Tomography-based Image Guidance for Minimally Invasive Transforaminal Interbody Fusion
Published on: August 6, 2019
Optimising Patient Safety During the Use of Intraoperative Imaging for the Surgical Management of Facial Fractures: A
Nicole Garcia1, Mohamed Badawy2,3, Jake DiPasquale4
1Department of Plastic and Reconstructive Surgery, Eastern Health, Melbourne, VIC 3128, Australia.

Abstract:
The use of intraoperative computerised tomography (CT) to aid surgical management of facial fractures obviates the need for postoperative surgical scans, decreases return to theatre rates, and subsequently decreases overall hospital stay. This allows for better appreciation of a complex operative landscape in almost real time, and may become the gold standard of treatment. As with radiological investigations, decreasing radiation exposure of patients is a key goal. The aim of this study was to examine the effective radiation doses in patients undergoing surgical management of their facial fractures with the aid of a fixed-arm CT. This retrospective study was conducted on patients who underwent surgical fixation of their facial fractures within a hybrid surgical suite equipped with a fixed-arm cone beam CT (CBCT) from July 2023 to November 2024. The CBCT was used to assess adequacy of bony fixation. Data from imaging was collected to assess total effective radiation dose. Data from 30 random patients who underwent standard CT facial bones (CTFB) were collected as control. Data from 24 patients was collected. The majority were male (17/24, 70.8%) with an age range of 20-94 years. The average dose of the effective doses calculated in the CTFB cohort was 0.64 mSv (SD 0.05). This is a more-than-twenty-five-fold reduction in the average effective dose in the CBCT cohort, which was 0.025 mSv (SD 0.01). There was a statistically significant difference between the two cohorts with p < 0.0001 (95% CI 0.60-0.64). This study demonstrates that intraoperative CBCT delivers a significantly lower effective dose to patients compared with postoperative CTFB. Where facilities exist, CBCT offers a safer and more efficient alternative, with future work needed to assess staff dose, wait times, and cost impacts.
