Related Experiment Video
Updated: Jun 26, 2026


Isolation and Quantification of Botulinum Neurotoxin From Complex Matrices Using the BoTest Matrix Assays
Published on: March 3, 2014
Intradermal and Subcutaneous Botulinum Toxin Type A Injections Do Not Differ in the Induction of Neutralizing
Stefanie Honndorf1, Jessica Moser1, Klaus Fink1
1Neurotoxin & Biotechnology Development, Merz Therapeutics GmbH, Eckenheimer Landstr. 100, 60318 Frankfurt, Germany.

The neurotoxin botulinum toxin type A (BoNT/A), produced by the bacteria Clostridium botulinum, is commonly injected intramuscularly (IM) for the management of chronic muscle hyperactivity, such as post-stroke spasticity. New indications such as peripheral neuropathic pain require alternative routes of BoNT/A administration, such as subcutaneous (SC) or intradermal (ID). While IM BoNT/A injections may elicit anti-drug-antibodies (ADAs), their occurrence following SC or ID administration is unknown. Therefore, we investigated whether repeated SC or ID injections of 150 kDa BoNT/A can elicit ADAs in a dose-dependent manner, and whether these differ depending upon the route of administration. Mice were injected 5 times ID or SC with 150 kDa BoNT/A or, for higher doses, inactive mutant BoNT/A (DRBoNT/A) or inactivated toxoid (IA-BoNT/A). Total ADAs were analyzed by an immunoassay and the subgroup of neutralizing ADAs by an in vivo digit abduction score (DAS) assay following a challenge of 0.6 U BoNT/A IM. DRBoNT/A and IA-BoNT/A injections elicit ADAs (22.7 U/mL vs. 460.5 U/mL for ID; 4.7 U/mL vs. 339.4 U/mL for SC), while therapeutic doses of 150 kDa BoNT/A do not. Whereas mice with repeated 150 kDa BoNT/A injections at therapeutic dose show an unrestricted DAS of 3.7 (ID) or 3.4 (SC), mice injected repeatedly with 1.8 µg/kg DRBoNT/A or 500 µg/kg IA-BoNT/A show only a minimal DAS of ≤0.7, indicating a high titer of neutralizing ADAs. No differences were observed between administration routes. Accordingly, repeated ID or SC injections of pure 150 kDa BoNT/A at therapeutic doses fail to induce ADA formation in mice. On the other hand, DRBoNT/A ID injections induce higher ADA concentrations than SC, but generate similar amounts of neutralizing ADAs. IA-BoNT/A injections induce ADAs and neutralizing ADAs similarly after ID and SC injections. ADA development at intermediate BoNT/A doses can be higher after ID injection, but does not lead to differences in neutralizing ADAs. Our data demonstrate that the antibody response to botulinum toxin depends predominantly on the protein load, and less on the administration route.
The neurotoxin botulinum toxin type A (BoNT/A), produced by the bacteria Clostridium botulinum, is commonly injected intramuscularly (IM) for the management of chronic muscle hyperactivity, such as post-stroke spasticity. New indications such as peripheral neuropathic pain require alternative routes of BoNT/A administration, such as subcutaneous (SC) or intradermal (ID). While IM BoNT/A injections may elicit anti-drug-antibodies (ADAs), their occurrence following SC or ID administration is unknown. Therefore, we investigated whether repeated SC or ID injections of 150 kDa BoNT/A can elicit ADAs in a dose-dependent manner, and whether these differ depending upon the route of administration. Mice were injected 5 times ID or SC with 150 kDa BoNT/A or, for higher doses, inactive mutant BoNT/A (DRBoNT/A) or inactivated toxoid (IA-BoNT/A). Total ADAs were analyzed by an immunoassay and the subgroup of neutralizing ADAs by an in vivo digit abduction score (DAS) assay following a challenge of 0.6 U BoNT/A IM. DRBoNT/A and IA-BoNT/A injections elicit ADAs (22.7 U/mL vs. 460.5 U/mL for ID; 4.7 U/mL vs. 339.4 U/mL for SC), while therapeutic doses of 150 kDa BoNT/A do not. Whereas mice with repeated 150 kDa BoNT/A injections at therapeutic dose show an unrestricted DAS of 3.7 (ID) or 3.4 (SC), mice injected repeatedly with 1.8 µg/kg DRBoNT/A or 500 µg/kg IA-BoNT/A show only a minimal DAS of ≤0.7, indicating a high titer of neutralizing ADAs. No differences were observed between administration routes. Accordingly, repeated ID or SC injections of pure 150 kDa BoNT/A at therapeutic doses fail to induce ADA formation in mice. On the other hand, DRBoNT/A ID injections induce higher ADA concentrations than SC, but generate similar amounts of neutralizing ADAs. IA-BoNT/A injections induce ADAs and neutralizing ADAs similarly after ID and SC injections. ADA development at intermediate BoNT/A doses can be higher after ID injection, but does not lead to differences in neutralizing ADAs. Our data demonstrate that the antibody response to botulinum toxin depends predominantly on the protein load, and less on the administration route.
More Related Videos
Related Concept Videos
 01:22
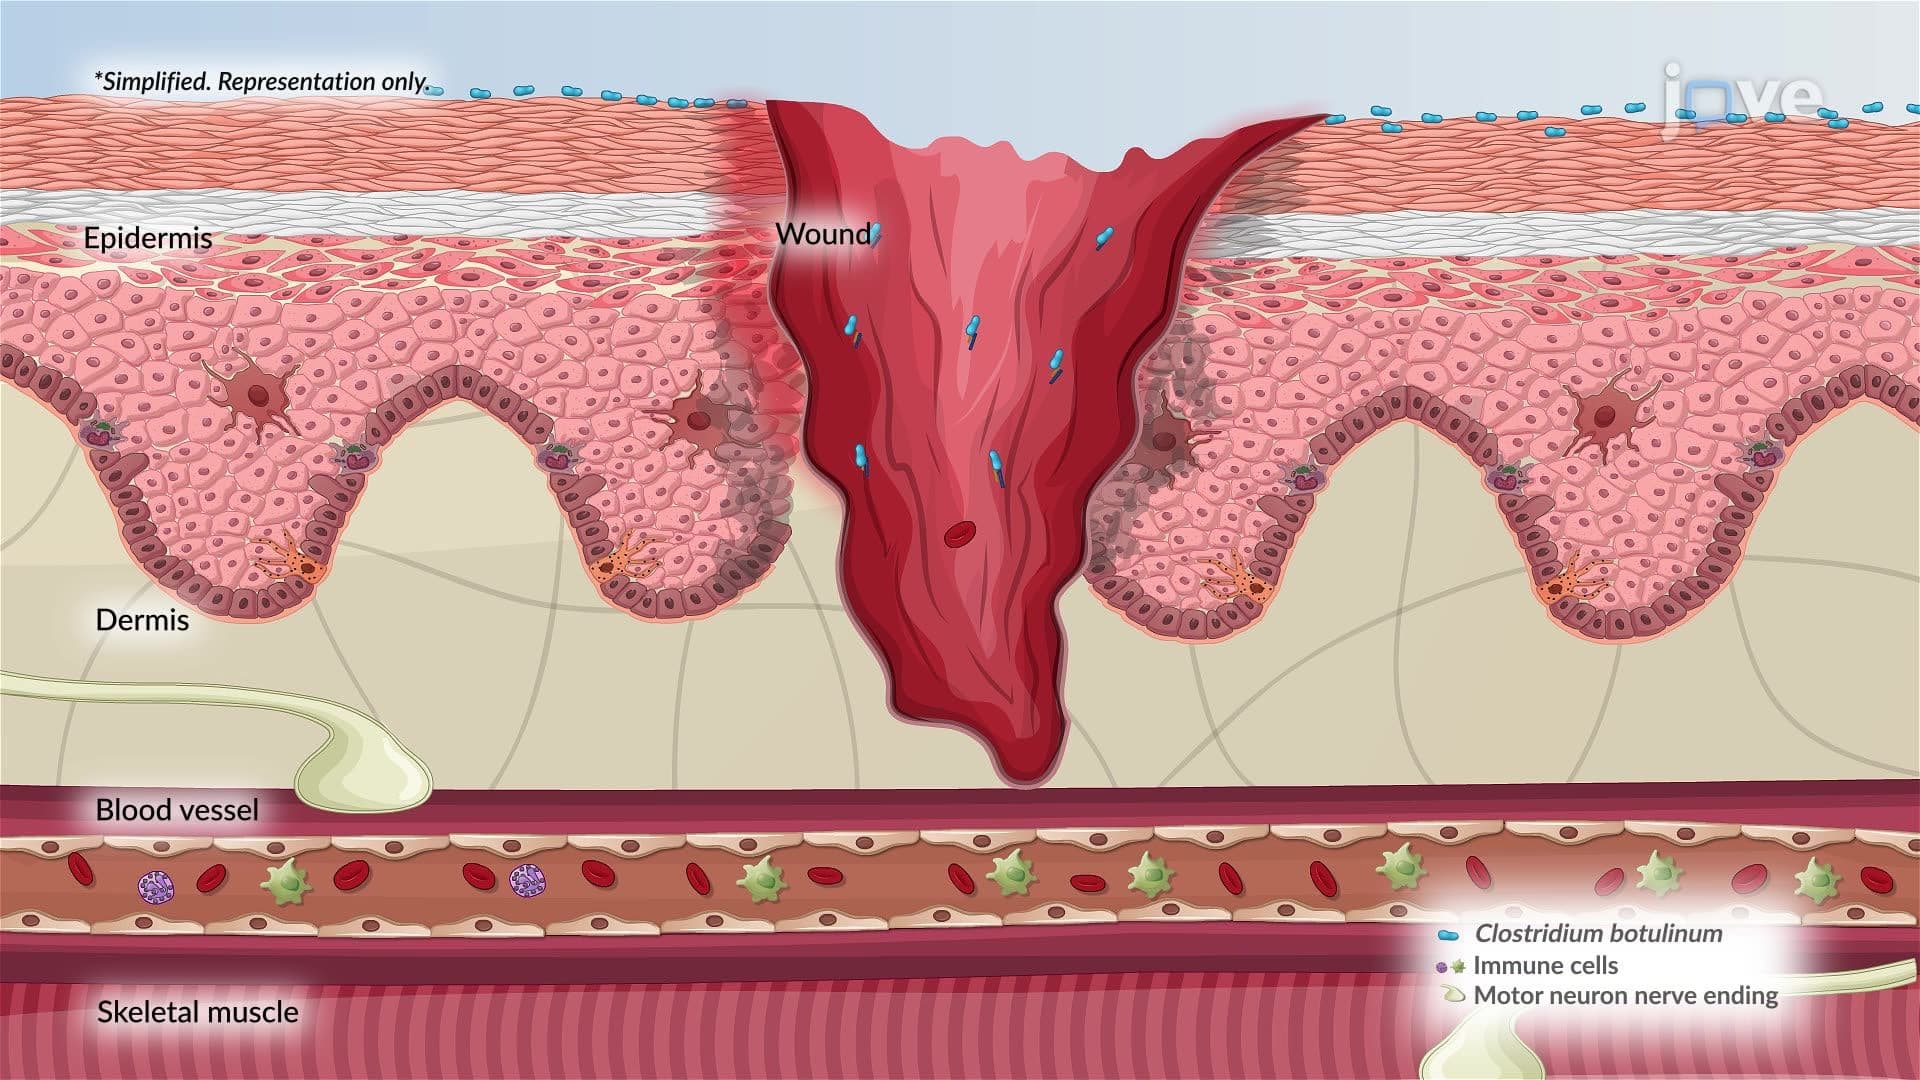
Botulism
 01:26
Directly Acting Muscle Relaxants: Dantrolene and Botulinum Toxin
The binding of dantrolene to the RYR1...
 01:11
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:17
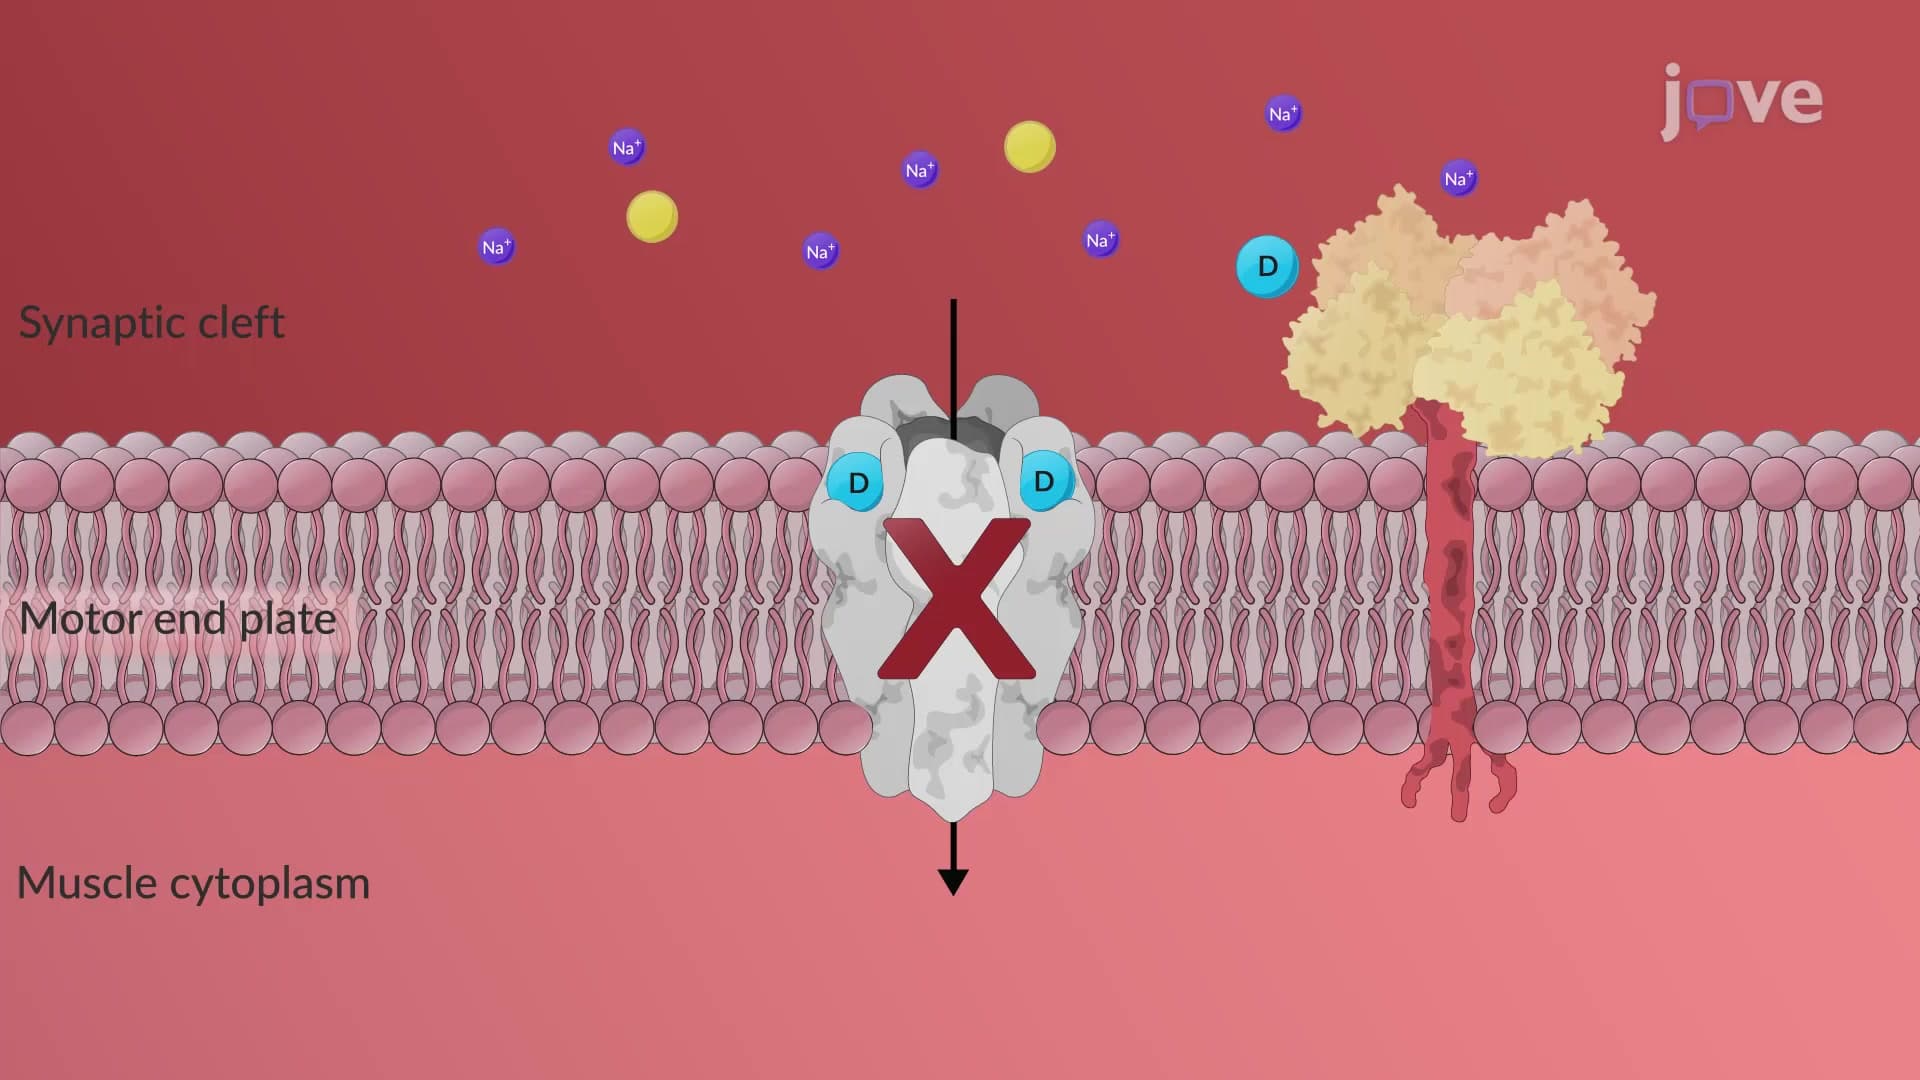
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:19
Depolarizing Blockers: Pharmocokinetics