Related Experiment Video
Updated: Jun 30, 2026


Separation of Immune Cell Subpopulations in Peripheral Blood Samples from Children with Infectious Mononucleosis
Published on: September 7, 2022
Heterogeneous immune cell composition in patients with combined immunodeficiency
Jareb J Pérez-Caraballo1,2, Colleen M Roark1,2, Megan M Dobrose1,2
1Division of Genetic Medicine and Clinical Pharmacology, Department of Medicine, Vanderbilt University Medical Center, Nashville, TN, United States.

Introduction:
Combined immunodeficiencies (CIDs) are a severe class of inborn errors of immunity characterized by defective T cell development and function, often accompanied by impaired humoral and natural killer (NK) cell responses. Despite their shared clinical classification, the immunological heterogeneity within CIDs remains incompletely understood. This study aims to characterize the immune cell landscape in CID patients caused by disease-causing mutations in different genes to identify immunophenotypic patterns.
Methods:
We analyzed peripheral blood immune cells from four CID patients with disease-causing mutations in ARPC1B, EZR, BCL10, and IRF4 using mass cytometry. Unbiased computational approaches were used to profile major immune populations and their subsets, and results were compared with healthy control samples to identify differences in immune cell frequencies and phenotypes.
Results:
All patients retained major immune populations, but their relative frequencies differed significantly from those of healthy controls. Patients with EZR and ARPC1B deficiency had markedly reduced CD4+ and CD8+ T cell frequencies, whereas the BCL10-deficient patient had a near absence of NK cells, highlighting mutation-specific immune distributions. Detailed T cell subset analyses revealed increased naïve and decreased memory T cells in patients with BCL10 and IRF4 deficiencies, indicative of impaired T cell activation and memory formation. In contrast, ARPC1B deficiency was associated with elevated memory T cells and reduced naïve cells, suggesting thymic output defects. The Ezrin-deficient patient maintained a naïve-to-memory T cell ratio similar to controls despite an overall reduction in T cells. B cell abnormalities were consistent across patients, characterized by increased naïve B cells, decreased memory B cells, and severely diminished plasmablast frequencies.
Discussion:
Our findings reveal pronounced immunological heterogeneity among CID patients caused by different genetic defects, challenging the notion that CIDs constitute a uniform entity. Disease-causing gene-specific alterations in immune cell composition and differentiation states underscore the complexity of CID pathophysiology. Comprehensive immunophenotypic profiling offers valuable insights into distinct mechanistic pathways and may guide the development of tailored therapeutic strategies to improve clinical outcomes for CID patients.


Related Concept Videos
 01:25
Immunodeficiency Diseases
There are three main causes of immunodeficiency disorders...
 01:40
Cell-mediated Immune Responses
 01:18
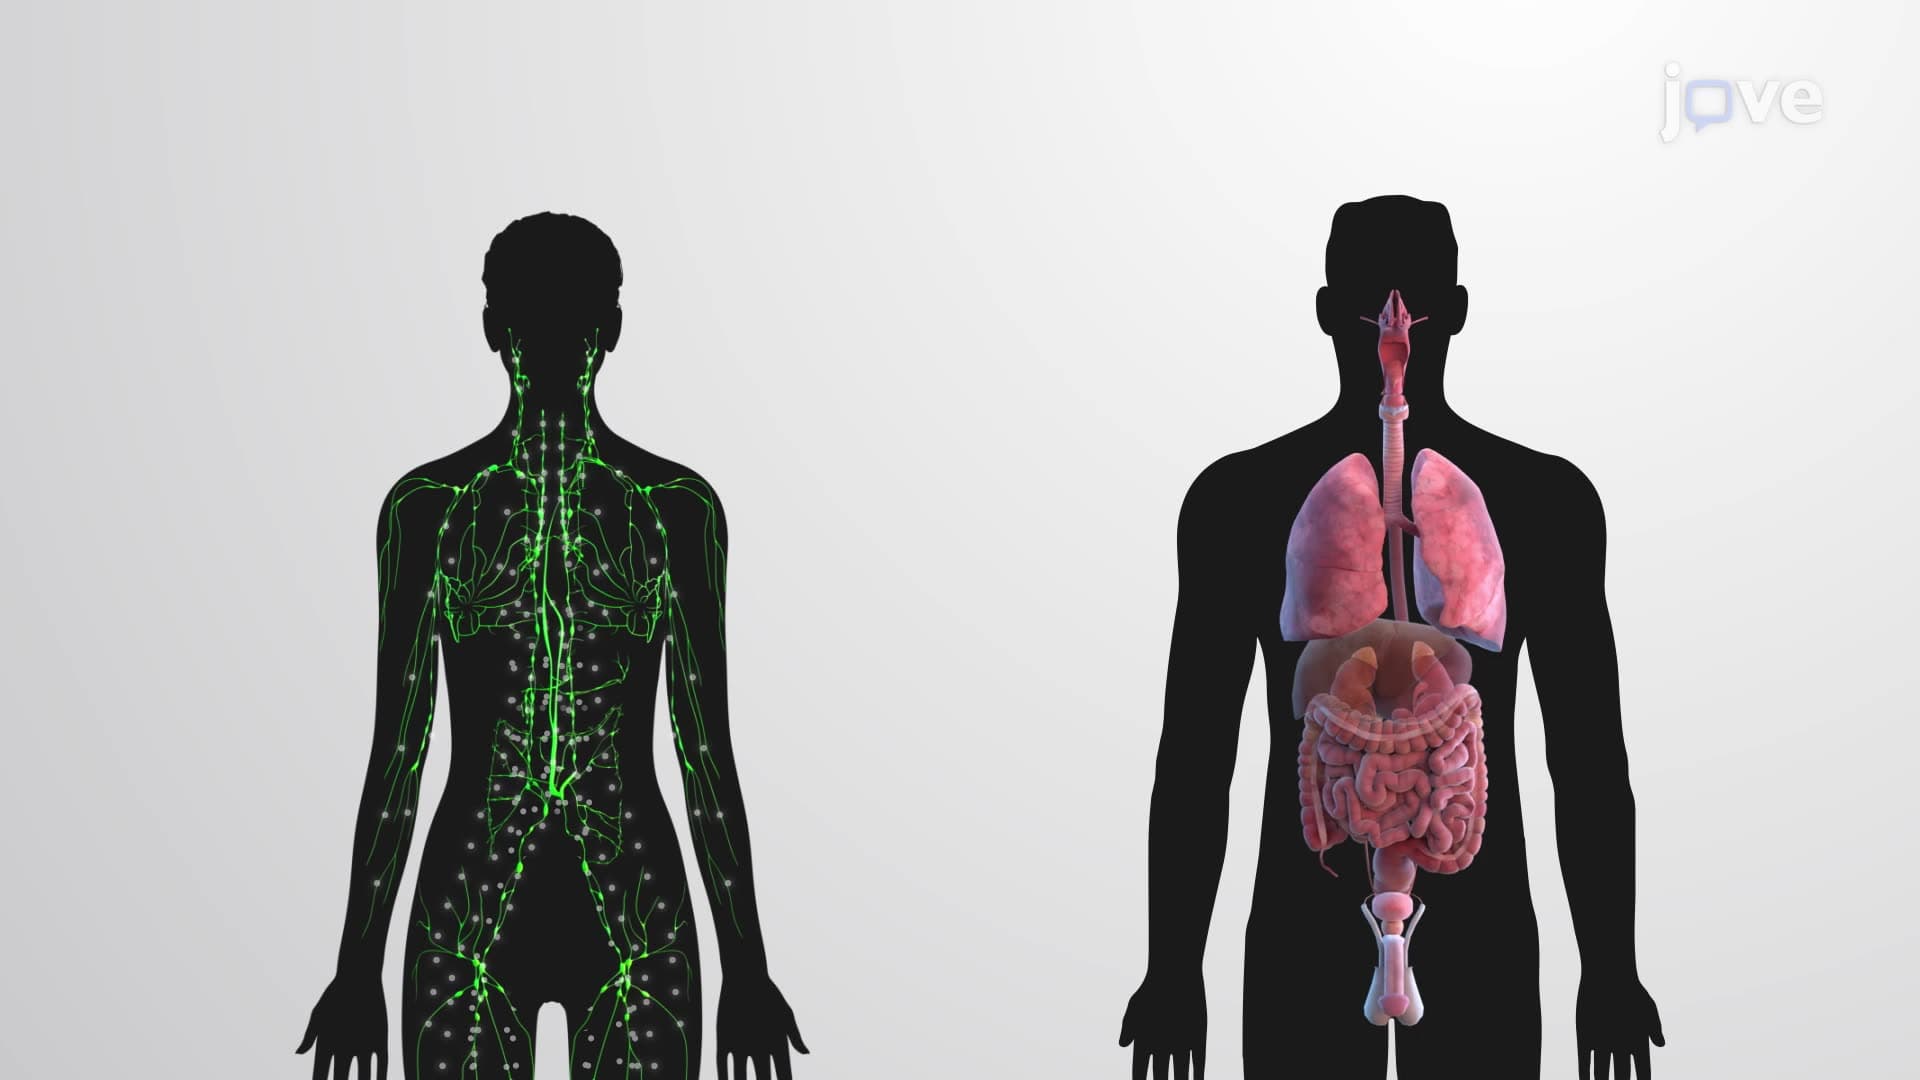
Lymphoid Cells and Tissues
Lymphoid cells consist of various types of immune system cells. These include B and T lymphocytes, which are responsible for producing antibodies and killing infected cells, respectively. Dendritic cells act as messengers between the innate and adaptive...
 01:20
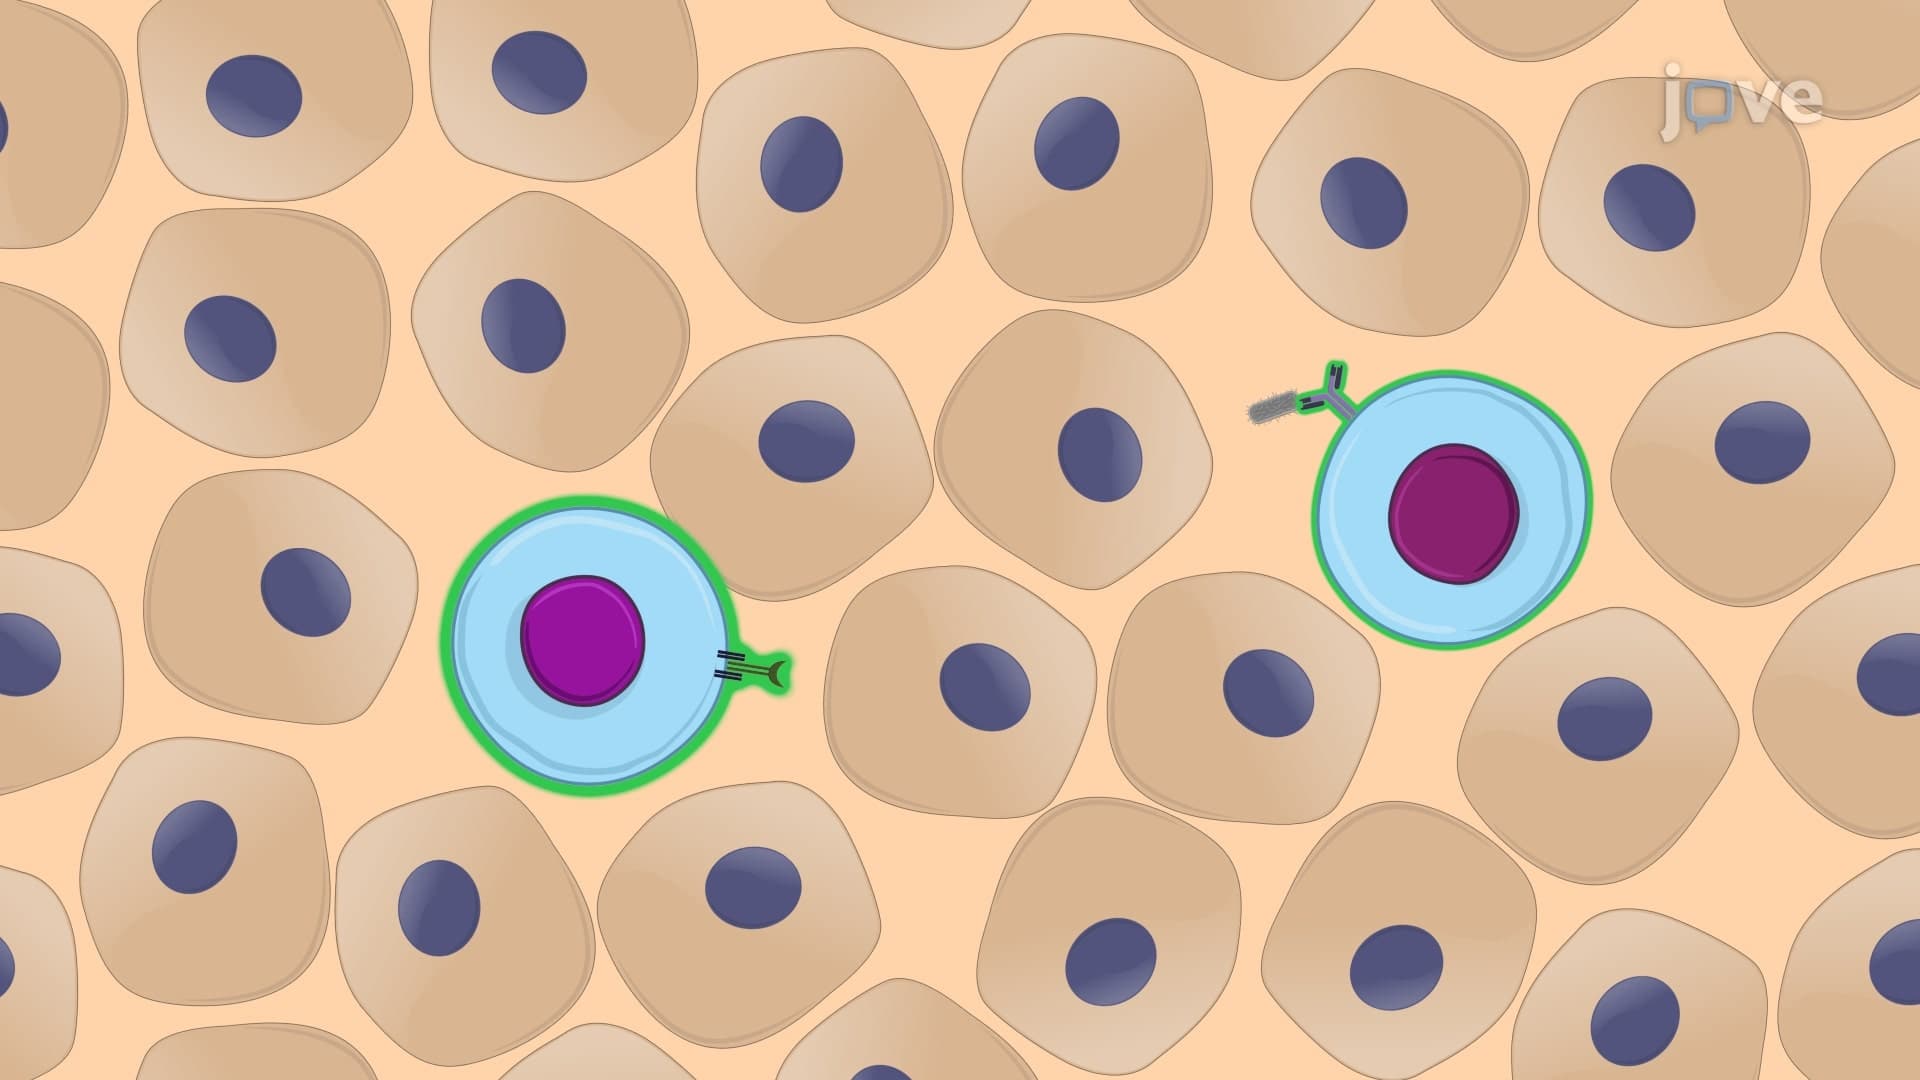
Special Features of Adaptive Immunity
The primary cell types involved in adaptive immunity are T cells and B cells. Each type has a unique role in defending the body against pathogens. T cells are responsible for cell-mediated immunity. They identify and eliminate infected cells directly,...
 01:22
T Cell Activation and Clonal Selection
Naive T cells that have not yet encountered an antigen express two primary CD...
 01:26
Antigens Involved in Adaptive Immunity
Complete Antigens
Complete antigens possess both immunogenicity and reactivity.