Related Experiment Video
Updated: Jul 1, 2026
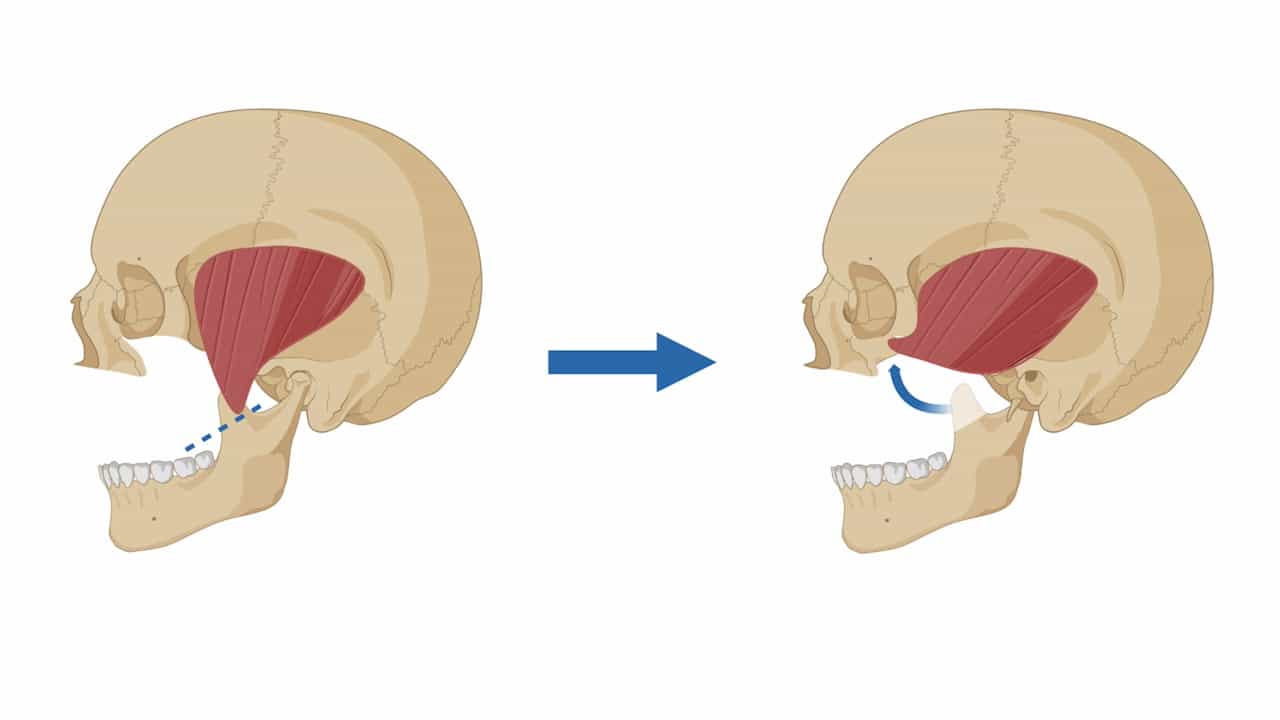

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Clinical Pattern and Surgical Outcome of the Plexiform Neurofibromatosis Induced Ptosis
S M U Kadir1, M R Mitra, M Nuruddin
1Dr Syeed Mehbub Ul Kadir, Associate Professor, National Institute of Ophthalmology & Hospital, Dhaka, Bangladesh;

Abstract:
Collecting data is essential to analyse demographic and clinical trends, measure the effectiveness of ptosis correction caused by lesions and determine the possibility of the progression of the disease. From 2015 to 2020, a prospective observational study was conducted in tertiary eye care in Bangladesh. The study included all patients who received surgical correction for mechanical ptosis caused by neurofibromatosis. The primary treatment approach was to remove the lesion through excision or debulking, followed by ptosis correction, either FBS (Frontalis Brow Suspension) or LPS (Levator Palpebrae superioris) reattachment. The results were assessed based on the extent of lesion reduction, the correction of ptosis and the likelihood of recurrence. The grading system ranged from a low score (poor) to an average score (fair) to a satisfactory score. A thorough examination was conducted on 48 cases, with an average age of 19.21. It was discovered that 29.0% of the cases presented mild ptosis accompanied by s-shaped PN (Palpebral neurofibromatosis). About 31.0% of individuals experience moderate ptosis, defined by OPN (Orbits-palpebral neurofibromatosis). In 40.0% of severe ptosis cases, OPN and TOPN (Temporo-orbital-palpebral neurofibromatosis) are present. The average MRD1 (Margin-reflex distance 1) measurement before surgery was -0.819 mm for patients who had ptosis surgery with LPS resection (75.0% of cases). In comparison, patients who had undergone FBS had an average preoperative MRD1 of -0.929 mm (25.0% of cases). Following a six-month surgical procedure, the average MRD1 measurements were +1.208 mm for LPS resection cases and +0.750 mm for FBS cases. The outcome was better in LPS resection than in FBS. Progression of the disease is common in severe cases of plexiform neurofibromatosis among young individuals. An optimal surgical solution for achieving satisfactory results and enhanced appearance demands a careful evaluation of the affected area, followed by removing the lesion through excision or debulking surgery and correcting any ptosis in a single procedure. This approach can undoubtedly provide exceptional cosmetic results.