Related Experiment Video
Updated: Jul 4, 2026
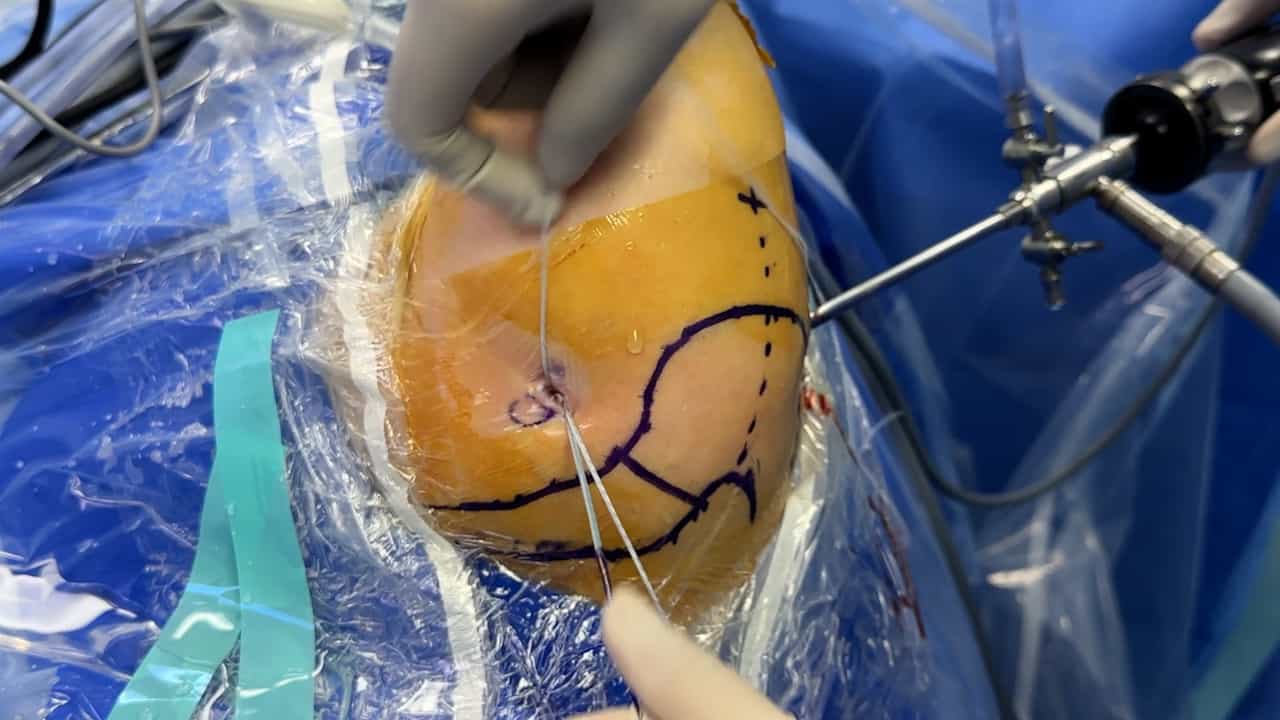

The Modified Single-working Portal Technique Using Lasso-loop Stitch with Needle for Arthroscopic Subscapularis Repair
Published on: August 8, 2025
Comparison of Long-term Supraspinatus Tear Progression After Arthroscopic Isolated Subscapularis Repair With and
Woo-Sung Do1, Yong-Min Chun1, Sung-Jae Kim1
1Department of Orthopaedic Surgery, Arthroscopy and Joint Research Institute, Severance Hospital, Yonsei University College of Medicine, Seoul, Republic of Korea.

Background:
Long-term outcomes after arthroscopic isolated subscapularis repair are limited, and magnetic resonance imaging (MRI)-based assessments extending to 10 years are particularly scarce. Therefore, it remains unclear whether preserving the comma tissue (in-continuity technique) provides long-term advantages over disrupting the upper subscapularis margin (margin disruption technique).
Hypothesis:
The in-continuity and margin disruption techniques would demonstrate comparable 10-year radiological and clinical outcomes in patients undergoing arthroscopic isolated subscapularis repair.
Study Design:
Cohort study; Level of evidence, 3.
Methods:
Among patients who underwent arthroscopic isolated subscapularis repair between 2008 and 2015, those with an intact repair on 6-month postoperative MRI and at least 2 years of clinical follow-up were identified. From this cohort, 24 patients treated with the in-continuity technique and 24 treated with the margin disruption technique were included. Ten-year MRI findings (subscapularis Goutallier grade, tendon integrity, and supraspinatus tear progression) and clinical outcomes (active range of motion [ROM], visual analog scale [VAS] pain score, Subjective Shoulder Value [SSV], American Shoulder and Elbow Surgeons [ASES] score, and University of California, Los Angeles [UCLA] score) were compared. A subgroup analysis was performed to evaluate long-term structural outcomes according to early tendon healing quality assessed on 6-month MRI.
Results:
A total of 48 patients were followed for a mean of 11.9 ± 1.2 years. Radiologically, among patients confirmed to have an intact repair at 6 months, none progressed to a retear during long-term follow-up. However, during the 10-year follow-up period, supraspinatus tears developed in a higher proportion of patients in the margin disruption group (11/24 vs 2/24; P = .003). Clinically, at 2 years, the in-continuity group demonstrated higher UCLA scores (median [IQR], 34.0 [29.5-36.0] vs 28.5 [26.8-31.0]; P = .047). By 10 years, the in-continuity technique showed consistently superior functional outcomes, including VAS pain (median [IQR], 2.0 [1.0-3.0] vs 3.0 [2.0-3.2]), ASES (median [IQR], 78.5 [71.0-88.5] vs 63.0 [60.0-70.0]), and UCLA (median [IQR], 28.5 [21.5-30.5] vs 21.0 [18.0-24.0]) scores (all P < .05). In the subgroup analysis, worse early tendon healing quality on 6-month MRI was associated with greater preoperative tear severity, including higher Lafosse grade (P = .018) and greater tendon retraction (P < .001); however, early healing status did not predict long-term structural failure at follow-up.
Conclusion:
Disruption of the comma tissue was associated with a higher risk of long-term supraspinatus tear progression and worse clinical outcome scores compared with the in-continuity comma tissue technique. Although 6 months is an appropriate time point to assess subscapularis tendon integrity, continued clinical deterioration should prompt evaluation for secondary supraspinatus tear progression.