Related Experiment Video
Updated: Jul 10, 2026
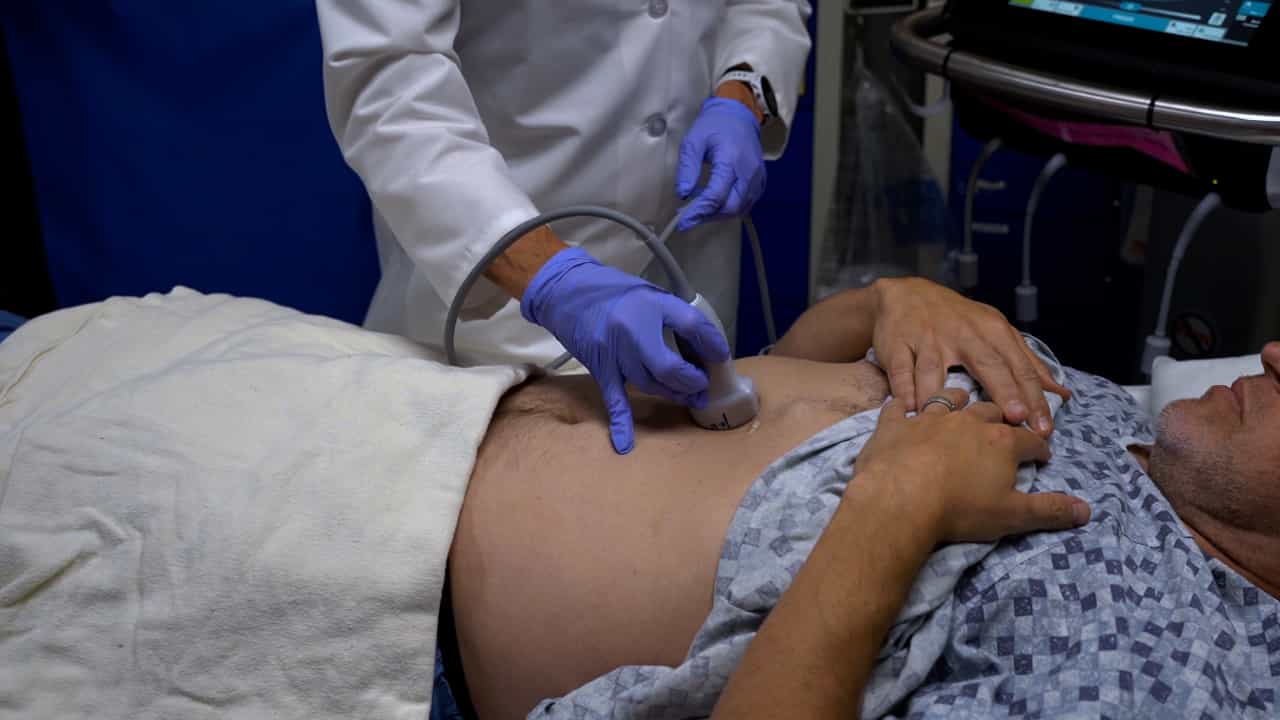
Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
Effect of a liberal fluid fasting policy before surgery on the incidence of aspiration: a single centre retrospective
Marije Marsman1, Maarten Derksen2, Marloes Veltcamp Helbach1
1Department of Anaesthesiology and Intensive Care Medicine, University Medical Centre Utrecht, The Netherlands.

Background:
In adults undergoing anaesthetic procedures, a preoperative fasting duration of 2 h for clear fluids is advised to minimise pulmonary aspiration risk. This fasting duration is under debate, because a shorter duration has been shown to improve patient wellbeing and seems not markedly to increase the aspiration risk. Although some hospitals already have adopted such a policy, large-scale studies addressing safety of this strategy are lacking. Therefore, the primary aim of this study was to assess the incidence of aspiration after implementation of a liberal fluid fasting policy.
Methods:
This observational single-centre cohort study was performed in a Dutch tertiary referral hospital after implementation of a liberal fluid fasting policy and included adults undergoing elective and urgent procedures under anaesthesia. The primary outcome was pulmonary aspiration, defined as documented visualisation of gastric content in the tracheobronchial tree below the vocal cords as seen by laryngoscopy, bronchoscopy, after tracheal suctioning with or without signs of respiratory distress or both. Secondary outcomes were regurgitation (visualisation of gastric content in the oral cavity or pharynx) or aspiration pneumonia. Risk factors for aspiration were identified using logistic regression analysis.
Results:
Between June 2019 and February 2025, 56 995 patients were evaluated with a recognised aspiration incidence of 3.7 (95% confidence interval [CI] 2.4-5.6) per 10 000 patients. The incidence of regurgitation was 25 (95% CI 21-29) per 10 000, and aspiration pneumonia occurred in 2.1 (95% CI 1.2-3.7) per 10 000. Median fasting duration for clear fluids was 63 min (inter-quartile range 24-116 min).
Conclusions:
A liberal fasting policy for clear fluids before elective and urgent surgery in adults had a higher associated incidence of aspiration compared with the previously reported incidence using a standard 2-h fasting policy. Because a liberal fasting policy has been shown to improve patient wellbeing, this study could contribute to the discussion among patients and clinicians to balance the benefits and risks of such a liberal policy.
