Related Experiment Video
Updated: Jul 12, 2026
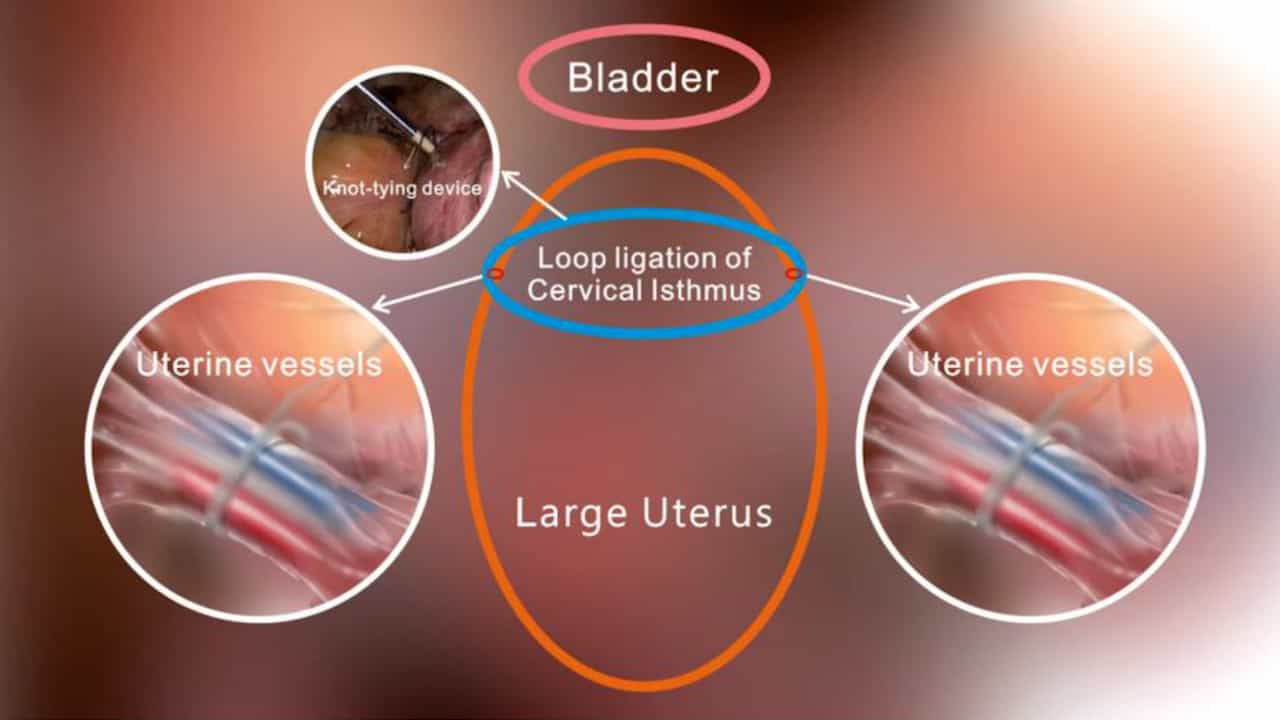

Laparoscopic Extracorporeal Knot-Tying for Uterine Vessel Occlusion during Hysterectomy with Cervical Cerclage in Large Uteri
Published on: September 12, 2025
Preoperative considerations for cervical cerclage (part 1)
Ilaria Paladino1, Moti Gulersen2, Amanda Roman2
1Division of Maternal-Fetal Medicine, Department of Obstetrics and Gynecology, Sidney Kimmel Medical College of Thomas Jefferson University, Philadelphia, PA (Paladino, Gulersen, Roman, Boelig, and Berghella); Department of Woman, Child and Neonate, Prenatal Diagnosis and Fetal Surgery Unit, Fondazione IRCCS Ca' Granda, Ospedale Maggiore Policlinico, Università degli studi di Milano, Milan, Italy (Paladino).

Abstract:
Transvaginal cervical cerclage remains a central strategy for preventing spontaneous preterm birth in appropriately selected pregnancies. Although decades of research have clarified which patients benefit most from cerclage, substantial heterogeneity persists in pre-, intra-, and postoperative management. This article, the first in a series on cerclage technique, synthesizes the evidence guiding preoperative decision-making. Cerclage is classified by indication as history-indicated cerclage, ultrasound-indicated cerclage and physical examination-indicated cerclage. History-indicated cerclage is recommended for patients with ≥3 prior early spontaneous preterm births or second-trimester losses <28 weeks, prior ultrasound-indicated cerclage with delivery at<32 weeks, or prior physical examination-indicated cerclage; twin gestation alone is not considered an indication. Ultrasound-indicated cerclage should be considered in singletons without prior spontaneous preterm birth with transvaginal ultrasound cervical length ≤20 mm and is recommended in singletons with prior spontaneous preterm birth when cervical length is ≤25 mm before 24 weeks' gestation; in twins, it may be considered when cervical length ≤15 mm before 24 weeks' gestation. Physical examination-indicated cerclage is recommended in singleton or twin gestations with asymptomatic cervical dilation ≥1 cm before 24 weeks' gestation. Timing varies by indication: history-indicated cerclage is typically placed at 12 to 14 weeks' gestation and is not urgent, whereas ultrasound-indicated cerclage and physical examination-indicated cerclage are usually performed between 16 and 23 6/7 weeks' gestation in response to cervical changes, ideally within 72 hours and 24 hours of diagnosis of short transvaginal ultrasound cervical length or dilated cervix, respectively. Preoperative evaluation should include a detailed anatomic ultrasound examination and appropriate genetic screening. Routine urogenital cultures are not indicated in the absence of symptoms. Amniocentesis is not recommended for history-indicated cerclage or ultrasound-indicated cerclage but should be considered before physical examination-indicated cerclage to evaluate for intra-amniotic infection. Adjunctive management remains variable. Progesterone is recommended for a short cervical lenght <=25mm before 24 weeks. Outpatient cerclage appears safe, with no clear benefit to routine inpatient management. Perioperative indomethacin and antibiotics are likely unnecessary for history-indicated cerclage but may be considered in ultrasound-indicated cerclage and are suggested for physical examination-indicated cerclage. El resumen está disponible en Español al final del artículo.

Related Concept Videos
 01:22
Aneurysm IV: Nursing Management
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:28
Cardiac Catheterization I: Pre-Procedure Overview
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management