Related Experiment Video
Updated: Jul 12, 2026
Dynamic Lung Tumor Tracking for Stereotactic Ablative Body Radiation Therapy
Published on: June 7, 2015
Cone Beam CT-Guided Online Adaptive Radiation Therapy for Prostate Stereotactic Body Radiation Therapy
D M McClatchy1, J Pursley2, C Esposito3
1Department of Radiation Oncology, Massachusetts General Hospital, Boston, Massachusetts.

Purpose:
Although computed tomography-guided online adaptive radiation therapy (CTgART) is an emerging treatment modality for prostate stereotactic body radiation therapy (SBRT), the feasibility and dosimetric improvements have not yet been quantified in a large multicenter cohort.
Methods And Materials:
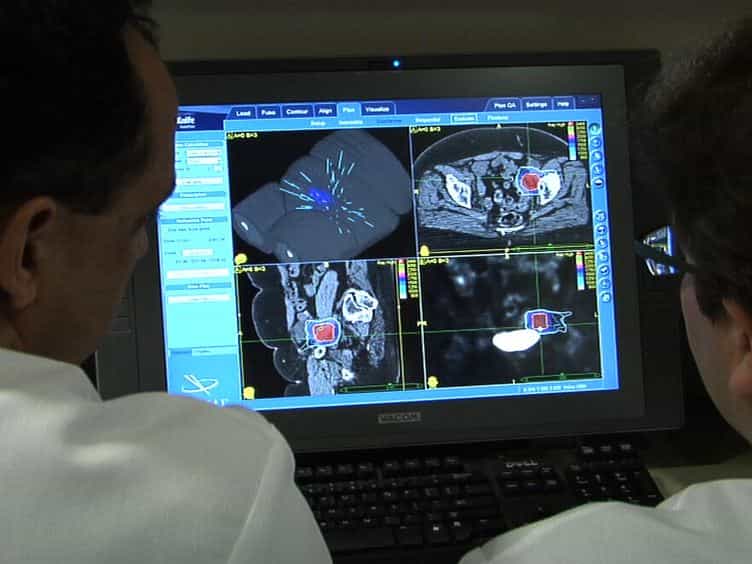
A cohort of 74 patients with prostate cancer treated with a 5-fraction SBRT course of CTgART between January 2023 and June 2024 was collected from 2 centers and analyzed retrospectively. Timestamps of the adaptive process and the daily contoured volumes were collected, along with dose-volume histogram (DVH) data for both the scheduled and adapted plans. The duration of the adaptive process and pretreatment verification imaging shift magnitudes were compared. Differences in DVH metrics between the scheduled and adapted plans were analyzed.
Results:
The adapted plan was chosen in 95% of all fractions, with 81% of patients having all 5 fractions adapted. The mean adaptive planning time was 18.7 ± 4.8 minutes (mean ± standard deviation). The mean shift in each cardinal direction was <2 mm on the pretreatment verification image and was correlated with the adaptive planning time. For 90% and 68% of all fractions, the daily contoured clinical target volume was within 5 cc and 5% of the volume drawn at computed tomography simulation, respectively. The 2 most common DVH improvements on the adapted plan were the planning target volume V100% and the rectum V15 Gy, with 52% and 37% of fractions exhibiting at least a 5% change, respectively. Overall, 85% of all fractions showed at least 1 clinically meaningful improvement in a DVH metric with adaptation. Body mass index, treated seminal vesicle length, and the number of DVH metrics improved on the first fraction were correlated with the number of DVH metric improvements during subsequent fractions.
Conclusions:
CTgART for SBRT treatment of prostate cancer can be performed in a timely and reproducible manner while substantially improving the dosimetry of target coverage and organ-at-risk sparing.