Related Experiment Video
Updated: Oct 29, 2026
A New Technique for Treating Low-risk Prostate Cancer—Super Active Surveillance
Published on: November 7, 2025
Hypofractionated Radiation Therapy for Localized Prostate Cancer: An ASTRO Clinical Practice Guideline
Scott C Morgan1, Aditya Halthore2, Angela Y Jia3
1Department of Radiation Oncology, The Ottawa Hospital and University of Ottawa, Ottawa, Ontario, Canada.

Purpose:
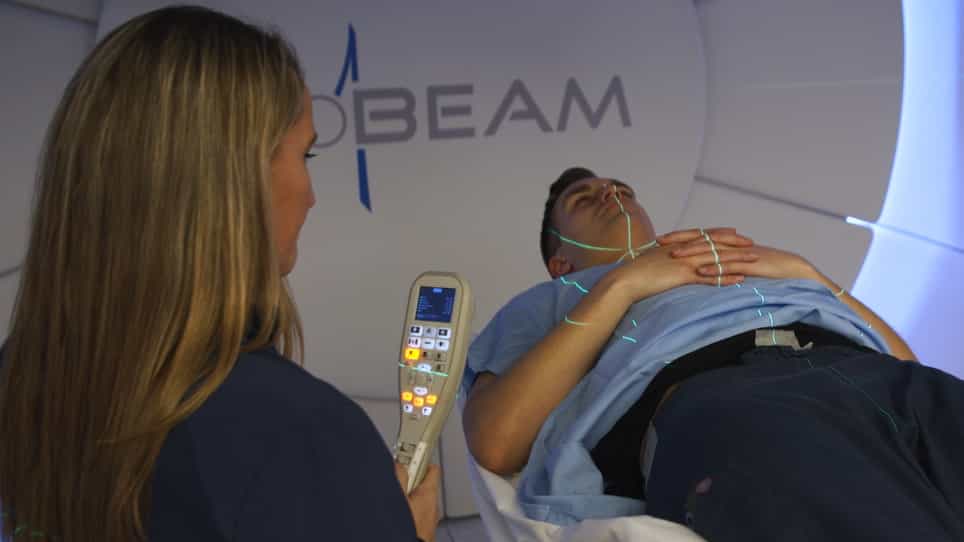
This guideline provides evidence-based recommendations on the use of hypofractionated external beam radiation therapy (EBRT) in patients with localized prostate cancer, including indications for moderate hypofractionation (MHF) and ultrahypofractionation (UHF), appropriate dose-fractionation regimens, target volumes, and treatment planning and delivery techniques.
Methods:
The American Society for Radiation Oncology convened a multidisciplinary task force to address 5 key questions related to hypofractionated EBRT in localized prostate cancer. Recommendations were based on a systematic literature review and developed using a predefined consensus-based methodology with grading of quality of evidence and strength of recommendation.
Results:
MHF is recommended over conventional fractionation for patients receiving EBRT across all risk groups, supported by high-quality randomized data demonstrating equivalent oncologic outcomes, toxicity, and quality of life, with shorter treatment duration that may reduce overall treatment burden. UHF is recommended as a standard treatment option for patients with low- and intermediate-risk disease electing for definitive EBRT and may be considered in selected patients with high-risk disease, preferably in the context of clinical trials. Selection of fractionation should generally be independent of patient age, comorbidity, and use of androgen deprivation therapy, although MHF may be preferred over UHF for patients with significant baseline urinary dysfunction. Evidence supports the use of contemporary image-guided, conformal treatment techniques to optimize target coverage and minimize toxicity. Guidance is also provided regarding appropriate dose-fractionation regimens, including commonly used MHF and UHF schedules, as well as target volumes and integration of pelvic nodal irradiation.
Conclusions:
Hypofractionated EBRT has become the predominant form of definitive radiation therapy for localized prostate cancer, supported by mature randomized evidence demonstrating comparable outcomes to conventional fractionation and reduced treatment burden. Ongoing studies will further refine patient selection, the role of UHF in higher-risk disease, and integration of advanced imaging and adaptive technologies. These evidence-based recommendations inform best clinical practices in the use of hypofractionated EBRT for localized prostate cancer.