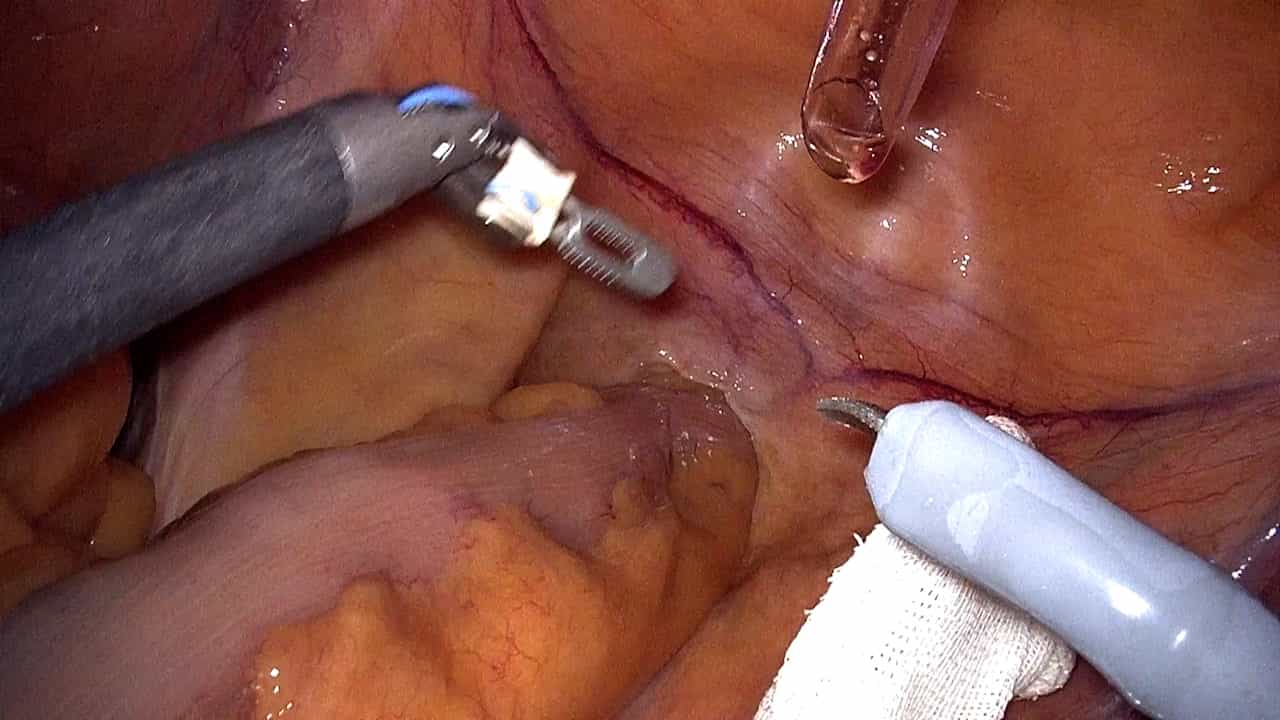
Related Experiment Video
Updated: Jul 15, 2026

Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
Circumferential resection margin status and longterm survival outcomes following robotic-assisted versus laparoscopic
Michael H Froehlich1,2, James E Petrancosta3, Deborah A Nagle4,5
1Department of Surgery, Stony Brook University Hospital, Stony Brook, NY, 11794, USA. Michaelh.froehlich@gmail.com.

Introduction:
Negative circumferential resection margins (CRM) have been demonstrated to confer improved survival in patients with locally-advanced rectal cancer (LARC). Multiple clinical trials have recently demonstrated non-inferior short-term outcomes for robotic-assisted surgical resection (RR) compared to laparoscopic resection (LR) for LARC. We assessed CRM and long-term survival outcomes in LARC patients undergoing RR versus LR using the National Cancer Database (NCDB).
Methods:
NCDB retrospective analysis was performed in clinical stage II or stage III LARC patients who underwent RR or LR following total neoadjuvant therapy (TNT) between 2006 and 2021. We analyzed short- and long-term outcomes, including CRM status and overall survival (OS).
Results:
14,744 patients were included. 6187 patients underwent RR and 8557 underwent LR. There was no difference in mean age, race, or comorbidity index scores between study groups. From 2006-2014 to 2015-2021, there was a significant increase in the proportion of LARC patients undergoing RR (31.8 to 53.0%). There was no significant difference in rate of positive CRM between the two groups (RR 5.7% vs. LR: 5.5%), however, the rate significantly decreased in the RR from Time Period 1 to Time Period 2 (6.3 to 4.8%). LR patients had a slightly higher risk of death compared to RR patients (HR 1.08, 95% CI 1.02-1.14). There was an increased risk of death in those in those with negative CRM who underwent LR compared to those with negative CRM who had undergone RR (HR 1.08, 95% CI 1.02-1.15).
Conclusions:
In those undergoing surgical resection for LARC after TNT, RR had equivalent rates of positive CRM with slightly superior long-term OS compared to those who underwent LR. This large volume, national database study demonstrates that RR for LARC continues to offer a suitable alternative to LR with non-inferior operative, short-term, as well as long-term surgical outcomes, which have not previously been demonstrated.