Related Experiment Video
Updated: Jul 16, 2026
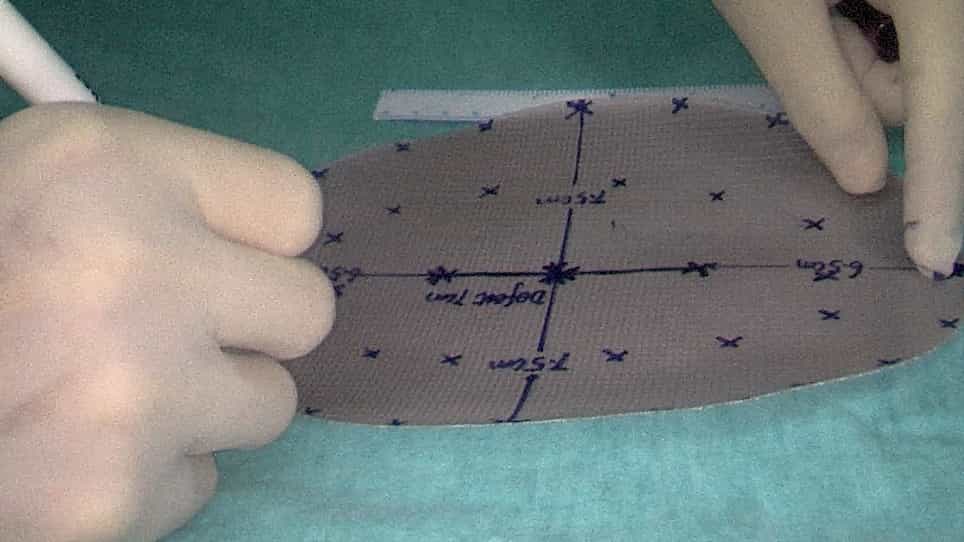

Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Feasibility and outcomes of emergency laparoscopic TAPP repair for strangulated inguinal hernia
Osman Gökhan Gökdere1, Sacit Altuğ Kesikli2
1Department of General Surgery, Faculty of Medicine, Malatya Turgut Özal University, Malatya, Türkiye. osman.gokdere@ozal.edu.tr.

Background:
The use of laparoscopy for strangulated inguinal hernia remains controversial, especially when bowel ischemia is suspected. This study evaluated the feasibility and outcomes of emergency laparoscopic TAPP repair in patients with strangulated inguinal hernia and examined preoperative factors associated with bowel resection.
Methods:
We reviewed all patients who were first treated laparoscopically for a strangulated inguinal hernia from April 2024 to December 2025. If laparoscopic reduction failed and conversion was needed, those cases were described separately. The same TAPP technique was used for all, with either a 12 × 15 cm or 15 × 15 cm polypropylene mesh fixed with nonabsorbable tacks. We used univariable analysis to look at factors linked to bowel resection, and described recurrence during follow-up.
Results:
Of the 62 patients initially approached laparoscopically, 11 (17.7%) required conversion to open repair because reduction was not possible. Two of these 11 needed bowel resection due to bowel ischemia. The main group for analysis included 51 patients who had a completed TAPP repair. Bowel resection was needed in 5 of these patients (9.8%; 95% CI 3.3-21.4%). Longer symptom duration and higher CRP levels were strongly linked to needing bowel resection. During a median follow-up of 16 months (IQR, 10.5-20 months), 6 patients (11.8%; 95% CI 4.4-23.9%) had recurrence. There were no deaths.
Conclusion:
Emergency laparoscopic TAPP repair appears feasible and safe in well-chosen patients with strangulated inguinal hernia, as long as laparoscopic reduction is possible. Longer symptoms and higher CRP levels were linked to a greater need for bowel resection, but these findings should be viewed with caution because of the small number of cases. These findings support a laparoscopic-first approach in appropriately selected patients, but more research from larger, multicenter studies is needed to confirm these findings and improve patient selection.