Related Experiment Video
Updated: Jul 16, 2026


Therapeutic Evaluation of Fecal Microbiota Transplantation in an Interleukin 10-Deficient Mouse Model
Published on: April 6, 2022
Gut Microbiota Dysbiosis and CIPN: State-of-the-Art Evidence and a Microbiota-Ozone Therapeutic Framework
Bernardino Clavo1,2,3,4,5,6,7,8, Elizabeth Córdoba-Lanús6,7,9, Gregorio Martínez-Sánchez4,10
1Research Unit, Hospital Universitario de Gran Canaria Dr. Negrín, 35019 Las Palmas de Gran Canaria, Spain.

Background/Objectives:
Chemotherapy-induced peripheral neuropathy (CIPN) affects up to 85% of patients receiving neurotoxic regimens, often leading to dose reduction and impaired quality of life, yet effective preventive or therapeutic options remain scarce. Emerging evidence implicates chemotherapy-induced gut microbiota dysbiosis in CIPN pathogenesis via a gut-nerve axis. Concurrently, rectal ozone insufflation (ROI) has been shown to modulate the gut microbiota and reduce inflammation in preclinical models. This article critically examines the evidence on the role of gut dysbiosis in CIPN, evaluates the microbiota-modulating capacity of rectal ozone therapy (OT), and assesses the biological plausibility of ozone as a microbiota-targeting intervention for CIPN, while explicitly distinguishing between established evidence and hypothetical mechanisms.
Evidence Synthesis:
Neurotoxic agents induce dysbiosis marked by reduced microbial diversity, loss of short-chain fatty acid-producing bacteria, and expansion of pro-inflammatory taxa. Preclinical models demonstrate a causal role for specific microbial communities in CIPN, with microbiota depletion or fecal transplantation modulating neuropathic phenotypes. In human cohorts, dysbiosis severity correlates with CIPN symptoms. Preclinical studies show that ROI restores microbial balance, enhances short-chain fatty acid levels, and strengthens intestinal barrier function via Nrf2/HO-1 and SIRT1 pathways. Preliminary retrospective data from small case series (n = 7 and n = 15) report sustained symptom improvement in CIPN patients receiving OT. However, no human study has directly linked ozone-induced microbiota changes to clinical outcomes, and the clinical evidence for OT in CIPN remains limited to uncontrolled observations.
Conclusions:
Convergent preclinical evidence supports a biological rationale for investigating ROI as a microbiota-targeting intervention in CIPN. However, this rationale remains largely hypothetical in the clinical setting. High-quality randomized controlled trials with longitudinal microbiome profiling are urgently needed to establish mechanistic causality and to determine whether the promising preclinical findings translate into clinically meaningful benefits. Until such evidence is available, the framework presented here should be regarded as hypothesis-generating rather than as a basis for clinical practice.

Related Concept Videos
 01:18
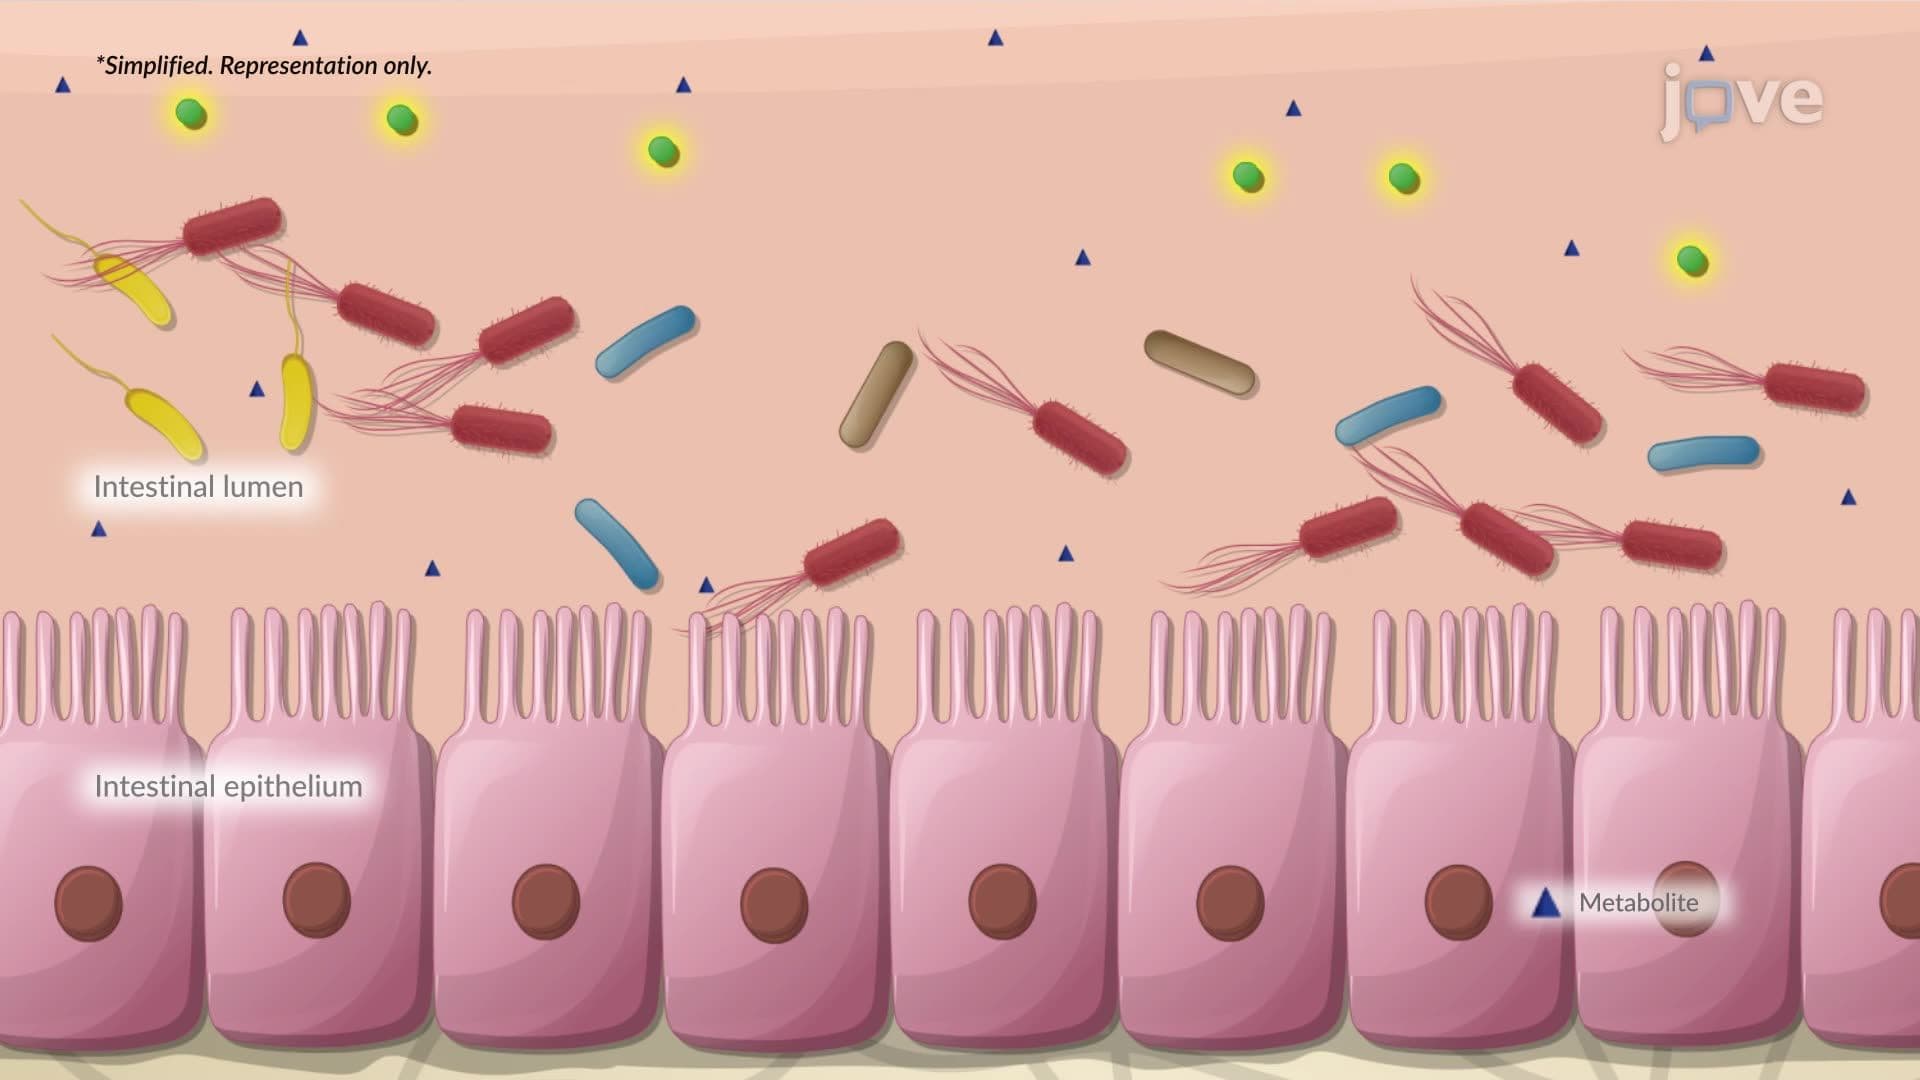
Dysbiosis of the Gut Microbiota
 01:21
Microbiota Modulation by Antibiotics
 01:22
Introduction to the Human Microbiota
 01:27
The Oral Microbiota
 01:18
Functions of the Gut Microbiota
 01:22
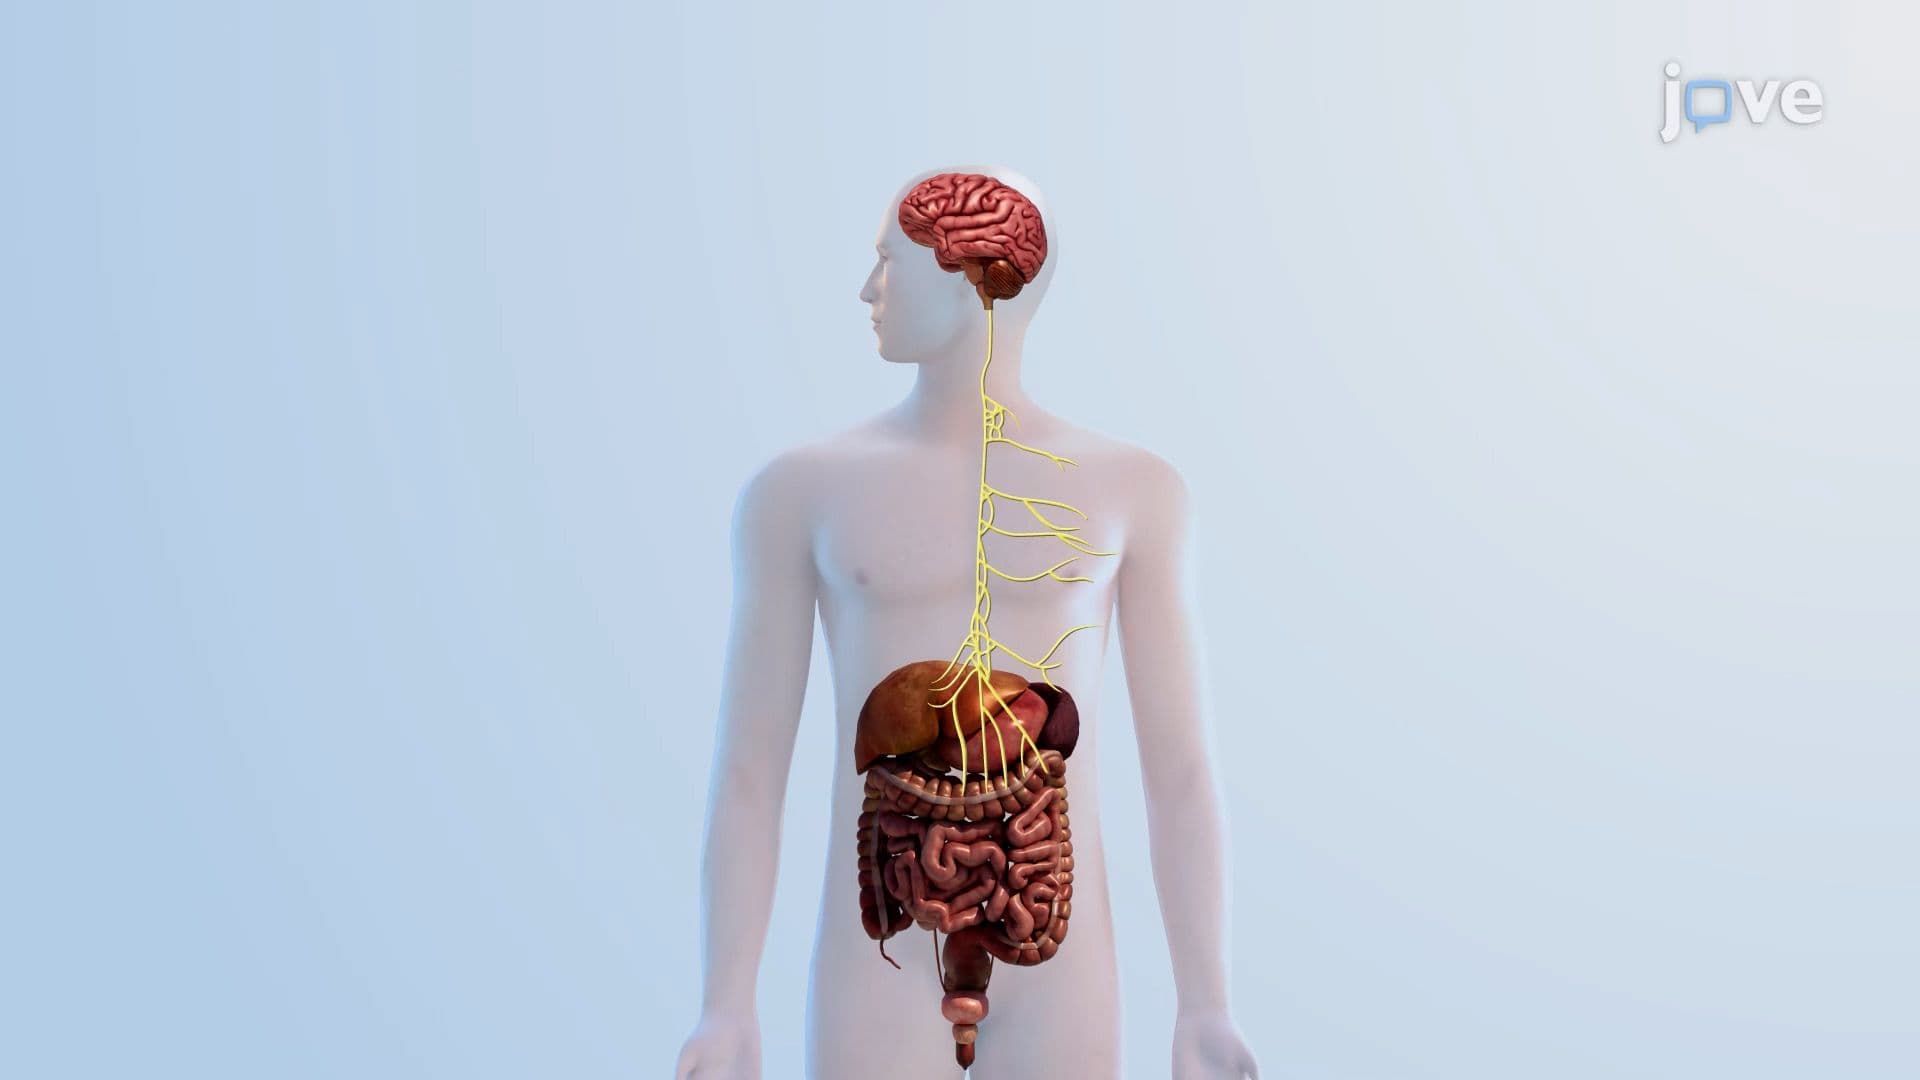
Gut-Brain Axis