Related Experiment Video
Updated: Jul 16, 2026
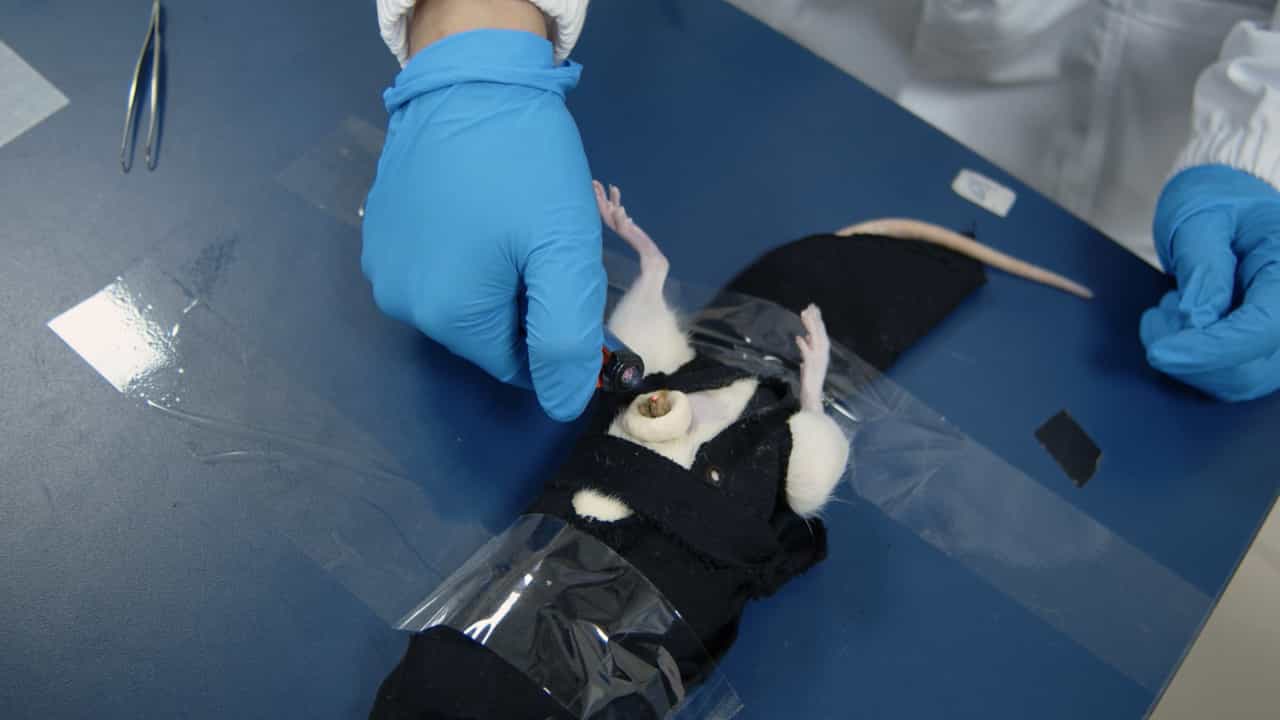

Herbs-Partitioned Moxibustion on the Navel in a Rat Model of Primary Dysmenorrhea with Cold Coagulation and Blood Stasis
Published on: October 4, 2024
Menstrual Health Under Constraint: A Meta-Synthesis of Refugee Women's Experiences
Francesca Marchetti1, Fabiana Staccioli1, Margaret Smith1
1Departmental Faculty of Medicine, Saint Camillus International University of Health and Medical Sciences (UniCamillus), 00131 Rome, Italy.

Background/Objectives: Refugee populations face significant barriers in accessing healthcare services, particularly in sexual and reproductive health (SRH), with important implications for menstrual health. Limited access to adequate menstrual products, safe sanitation facilities, and appropriate information contributes to period poverty among migrant and refugee women, exacerbating conditions of vulnerability and discrimination. The present study aims to explore the lived experiences, barriers, and facilitating factors in the management of menstrual health and menarche among refugee women and girls. Methods: A systematic meta-synthesis was carried out between January and May 2026 using the PubMed, Cochrane Library, Scopus and LILACS databases and grey literature sources. The SPIDER framework was applied to guide the research question and search strategy. Qualitative and mixed-method primary studies and grey literature reports containing qualitative findings describing experiences of menstruation among refugee women and girls were included. Studies published in English, Italian, Spanish, and Portuguese were eligible. Study quality was appraised using the Joanna Briggs Institute (JBI) critical appraisal checklist. Data were analysed using a thematic synthesis approach as described by Thomas and Harden. Results: A total of 24 studies were included. Six analytical themes were identified: (1) structural constraints affecting access to resources and services; (2) context-dependent menstrual management practices; (3) female support networks; (4) menstruation as a socially constructed and learned experience; (5) constrained agency and compromised dignity under conditions of stigma; and (6) physical and psychological impacts. Overall, menstrual health was shaped by the interaction of structural barriers and socio-cultural norms, which limited safe and dignified management. Significant gaps in knowledge and preparedness were observed, particularly prior to menarche. Women and girls relied on coping strategies and informal support networks despite associated trade-offs for health and dignity. Conclusions: Menstrual health among refugee women and girls is shaped by structural inequalities, socio-cultural norms, and conditions of displacement. Addressing these challenges requires integrated, multisectoral approaches that go beyond product provision to tackle underlying determinants. Strengthening menstrual health literacy, engaging communities, and supporting the role of healthcare professionals such as midwives is essential to support more equitable and sustainable menstrual health interventions. Findings should be interpreted in light of the heterogeneity of study contexts and methodological quality.
Background/Objectives: Refugee populations face significant barriers in accessing healthcare services, particularly in sexual and reproductive health (SRH), with important implications for menstrual health. Limited access to adequate menstrual products, safe sanitation facilities, and appropriate information contributes to period poverty among migrant and refugee women, exacerbating conditions of vulnerability and discrimination. The present study aims to explore the lived experiences, barriers, and facilitating factors in the management of menstrual health and menarche among refugee women and girls. Methods: A systematic meta-synthesis was carried out between January and May 2026 using the PubMed, Cochrane Library, Scopus and LILACS databases and grey literature sources. The SPIDER framework was applied to guide the research question and search strategy. Qualitative and mixed-method primary studies and grey literature reports containing qualitative findings describing experiences of menstruation among refugee women and girls were included. Studies published in English, Italian, Spanish, and Portuguese were eligible. Study quality was appraised using the Joanna Briggs Institute (JBI) critical appraisal checklist. Data were analysed using a thematic synthesis approach as described by Thomas and Harden. Results: A total of 24 studies were included. Six analytical themes were identified: (1) structural constraints affecting access to resources and services; (2) context-dependent menstrual management practices; (3) female support networks; (4) menstruation as a socially constructed and learned experience; (5) constrained agency and compromised dignity under conditions of stigma; and (6) physical and psychological impacts. Overall, menstrual health was shaped by the interaction of structural barriers and socio-cultural norms, which limited safe and dignified management. Significant gaps in knowledge and preparedness were observed, particularly prior to menarche. Women and girls relied on coping strategies and informal support networks despite associated trade-offs for health and dignity. Conclusions: Menstrual health among refugee women and girls is shaped by structural inequalities, socio-cultural norms, and conditions of displacement. Addressing these challenges requires integrated, multisectoral approaches that go beyond product provision to tackle underlying determinants. Strengthening menstrual health literacy, engaging communities, and supporting the role of healthcare professionals such as midwives is essential to support more equitable and sustainable menstrual health interventions. Findings should be interpreted in light of the heterogeneity of study contexts and methodological quality.

Related Concept Videos
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:18
Menses Phase
When fertilization does not occur, the corpus luteum deteriorates, causing a significant drop in the levels of estrogen and progesterone in the body. This hormonal decrease triggers the release of prostaglandins, which cause the uterine...
 01:24
Disorders of the Female Reproductive System
 01:19
The Menstrual Cycle
The menstrual phase occurs from days 1 to 5 and involves the shedding of the stratum functionalis, as a uterine...
 02:07
Oogenesis
 01:28
Menopause