Related Experiment Video
Updated: Jul 16, 2026
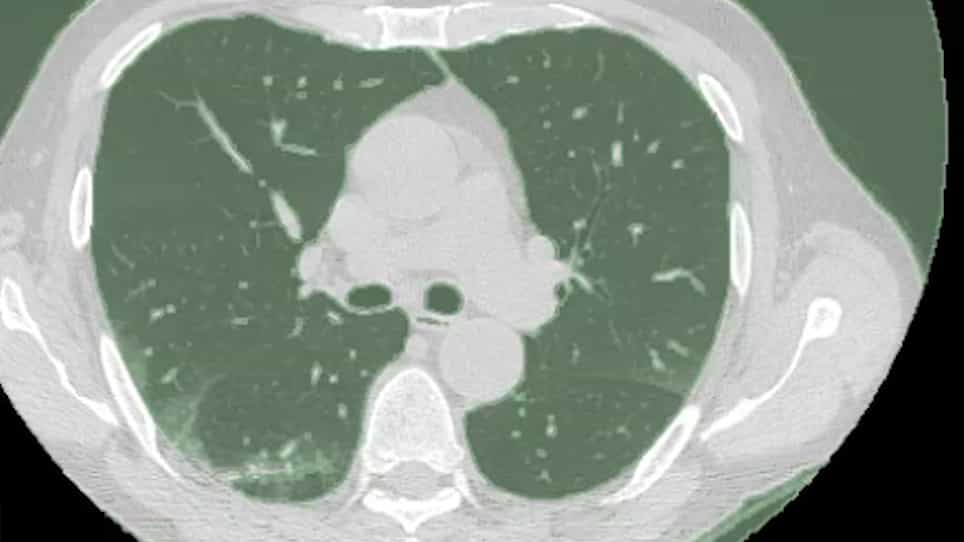

Lung CT Segmentation to Identify Consolidations and Ground Glass Areas for Quantitative Assesment of SARS-CoV Pneumonia
Published on: December 19, 2020
Progressive Pulmonary Alveolar Proteinosis Diagnosis Masking Pneumonic Lung Carcinoma: Anchoring Bias in Critical
Dakota Wheeler1, Rhaya Murray1, Teklu Legesse1
1Department of Cytopathology, University of Maryland School of Medicine, Baltimore, Maryland, USA.

Abstract:
Pulmonary alveolar proteinosis (PAP) is a rare disorder characterized by impaired surfactant clearance and intra-alveolar accumulation of proteinaceous material, resulting in progressive respiratory insufficiency. Its clinical, radiologic and cytologic features are nonspecific and overlap with a variety of diffuse pulmonary diseases. Similarly, poorly cohesive pneumonic-type lung carcinomas can present with diffuse pulmonary infiltrates that mimic infectious, inflammatory or metabolic lung disorders. On bronchoalveolar lavage (BAL), malignant cells may closely resemble atypical reactive pneumocytes. We report a patient with a presumed diagnosis of PAP whose worsening respiratory status and radiologic progression were attributed to progression of the underlying disease after BAL studies failed to identify malignancy. Despite continued clinical deterioration, the initial diagnosis remained the primary focus of management. Post-mortem examination revealed a poorly cohesive pneumonic pleomorphic carcinoma diffusely involving both lungs. This case highlights the limitations of BAL cytology and the potential impact of anchoring bias in complex pulmonary disease.

Related Concept Videos
 01:08
Pneumothorax II: Pathophysiology
 01:10
Atelectasis II: Pathophysiology
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:30
Pneumonia III: Complications and Assessment
 01:29
Pneumonia I: Introduction
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema