Related Experiment Video
Updated: Jul 17, 2026

Granulocyte-dependent Autoantibody-induced Skin Blistering
Published on: October 12, 2012
Case Report: A case report of bullous pemphigoid triggered by sintilimab (PD-1 inhibitor)
Chang Qin1,2, Chuan Yang1, Yuqi Wang1,2
1Department of Dermatology, Affiliated Hospital of North Sichuan Medical College, Nanchong, Sichuan, China.

Abstract:
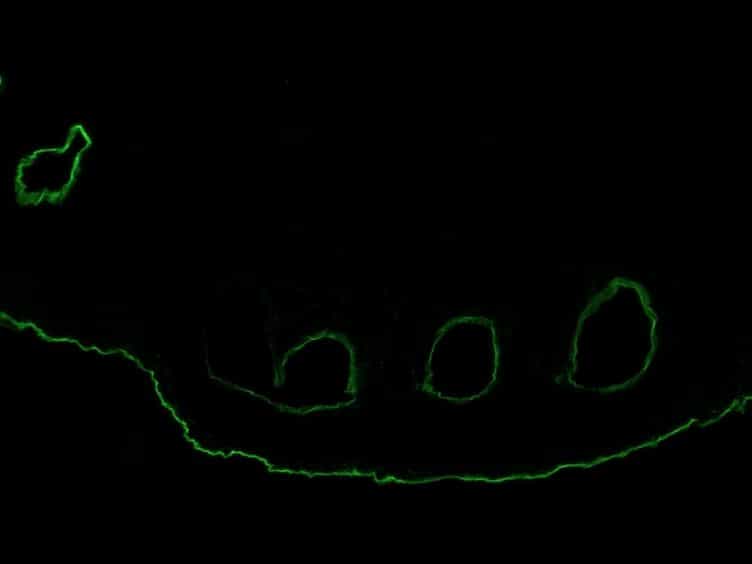
Immune checkpoint inhibitors (ICIs) can precipitate autoimmune bullous diseases, among which bullous pemphigoid (BP) is uncommon but has significant clinical implications. We report a 72-year-old man with poorly differentiated gastric adenocarcinoma and liver metastases who developed generalized pruritic erythema after the 4th cycle of sintilimab, followed by tense blisters after the 8th cycle. Upon admission (January 2025), over 30% of his body surface area (BSA) was affected, accompanied by pruritus that impacted his sleep. Histopathology showed eosinophilic cell infiltration within the epidermis and mild spongiosis. Edema was observed between collagen fibers in the papillary dermis, accompanied by a small number of lymphocytes and histiocytes. Moderate (+++) mixed inflammatory cell infiltration was observed in the superficial dermis, primarily consisting of lymphocytes (approximately 60%) and eosinophils (approximately 30%), with a small number of neutrophils (approximately 10%). Direct immunofluorescence (DIF) revealed IgG and C3 along the basement membrane zone (BMZ). Serum autoantibodies demonstrated significantly elevated BP180 (392.01 RU/mL) and low BP230 (9.29 RU/mL), while desmoglein-1 (8.38 U/mL) and desmoglein-3 (5 U/mL) were negative/low, supporting BP rather than pemphigus. The rash met the CTCAE (Common Terminology Criteria for Adverse Events) v5.0 criteria for Bullous dermatitis, Grade 3, with concomitant Pruritus, Grade 3. Daily intravenous methylprednisolone 60 mg was initiated, leading to cessation of new blister formation within 7 days and improvement in pruritus. Sintilimab was discontinued during treatment and resumed after BP was brought under control (approximately 1 month later); the patient has maintained remission for more than 12 months since resuming Sintilimab treatment, and no recurrence has been observed. The temporal association with PD-1 blockade, objective clinicopathologic confirmation, and lack of strong alternative culprits support a possible causal relationship. Early biopsy, DIF, and targeted serology enable timely CTCAE-guided management and informed decision-making for pausing or rechallenging PD-1 therapy.