Related Experiment Video For Breast cancer
Updated: Aug 6, 2026

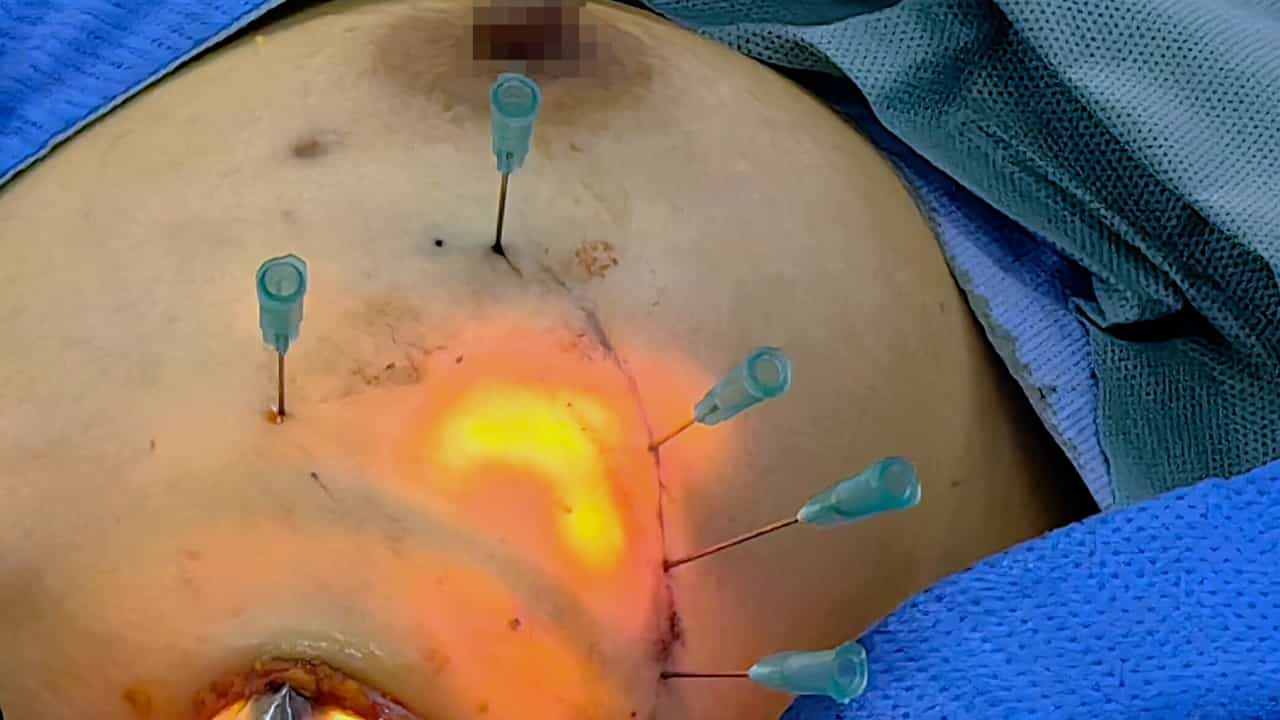
Endoscopic Bilateral Nipple-sparing Mastectomy via a Single Axillary Incision with Immediate Pre-pectoral Implant-based Breast Reconstruction
Published on: May 17, 2024
Preoperative Overestimation of Disease Extent and Discordance-Driven Mastectomy: A Retrospective Review of 245 Cases
Hadas Kadar Sfarad1, Cheng-Bang Chen2, Yujie Wang2
1Division of Surgical Oncology, Dewitt Daughtry Department of Surgery, University of Miami Miller School of Medicine, Miami, FL, USA. hadaskadar@gmail.com.

Background:
Preoperative mammography and magnetic resonance imaging (MRI) guide surgical planning in breast cancer but may misestimate disease extent. We quantified imaging-pathology discordance among patients undergoing mastectomy and estimated the discordance-driven mastectomy rate (DDMR), defined as imaging-extensive disease with localized final pathology, as a measure of discordance.
Patients And Methods:
We retrospectively reviewed 245 consecutive mastectomy cases (2018-2019) at a tertiary academic center; 236 had usable postoperative pathology and were analyzed. Preoperative imaging (mammography and/or MRI) was classified as localized versus extensive using predefined extent-indicating features and/or maximum size > 5 cm. Final pathology was similarly classified using size and multifocality/multicentricity as the reference standard. Concordance categories were concordant-localized, concordant-extensive, imaging overestimation, and imaging underestimation. The primary outcome was any discordance; the key clinical outcome was DDMR. Decision drivers were abstracted from the medical record when available.
Results:
Overall discordance occurred in 119/236 (50.4%) cases and was predominantly imaging due to overestimation (113/236, 47.9%; 95% CI 41.4-54.5); underestimation was uncommon (6/236, 2.5%). DDMR events occurred only when at least one modality had extent-indicating features and were common with mammography-only (44/53, 83.0%), MRI-only (30/43, 69.8%), or both (39/62, 62.9%). DDMR rates were similar across mastectomy subtypes and by neoadjuvant chemotherapy receipt. Among DDMR cases, surgeon-only requests were most frequent (71/113, 62.8%) versus patient-only requests (31/113, 27.4%; p < 0.001). Agreement between imaging and pathology was low (MRI κ = 0.241; mammography κ = 0.123).
Conclusions:
Among a cohort of patients undergoing mastectomy, imaging-pathology discordance was common and predominantly reflected overestimation. These findings highlight the importance of cautious interpretation of imaging-defined extent within clinical decision-making.